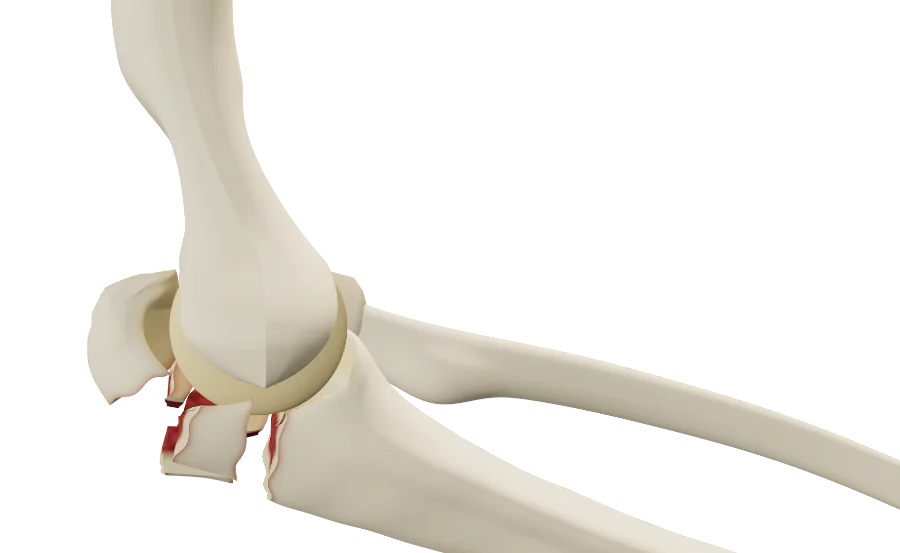
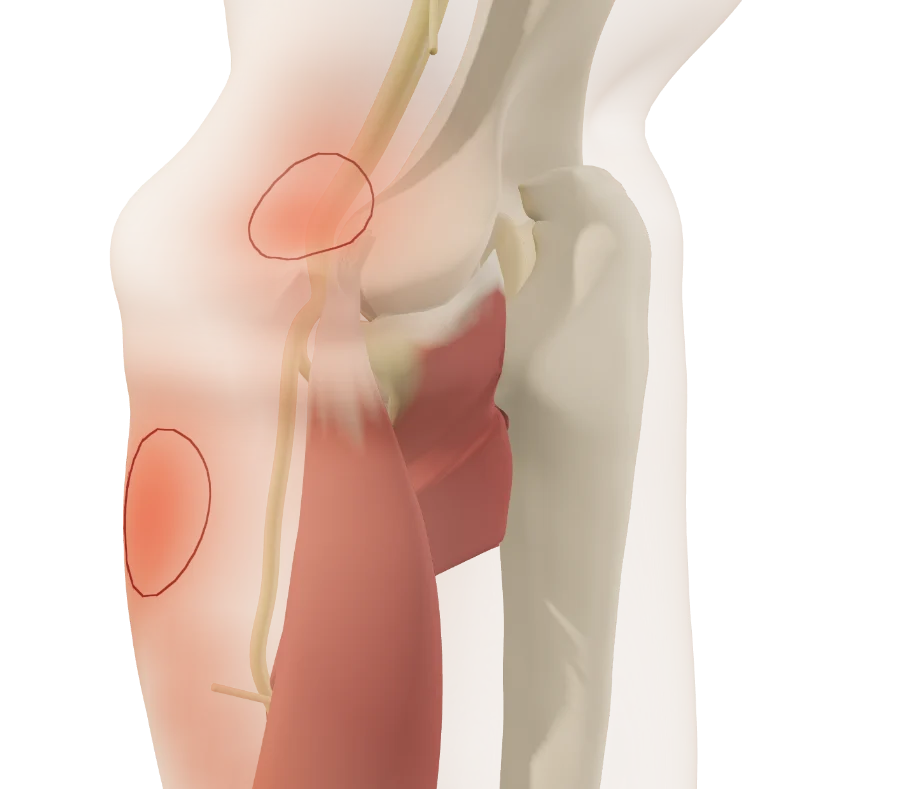
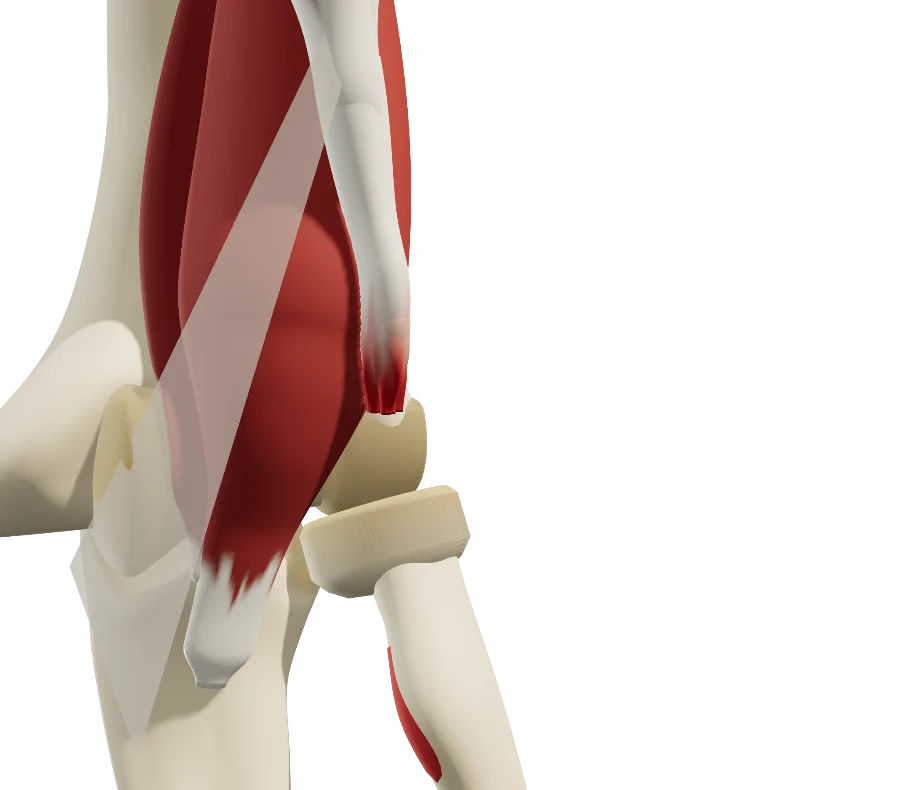
EMET Electronic Medical Twin
  1. EMET Education
  2. Musculoskeletal
  3. Elbow
  4. Cubital tunnel syndrome

3D model · Elbow

Cubital Tunnel Syndrome 3D Model

Show during the visit how elbow flexion compresses your patient's ulnar nerve, then the procedure you recommend. They leave with their model on their phone.

Designed by an orthopedic surgeon

Opens in your browser, no sign-up. For orthopedic and hand surgeons, neurologists, physiatrists, sports medicine physicians, rheumatologists and primary care physicians.

How it works

In the visit, in three steps

Structured information in a few minutes, which the patient can review at home.

  1. 1

    Show

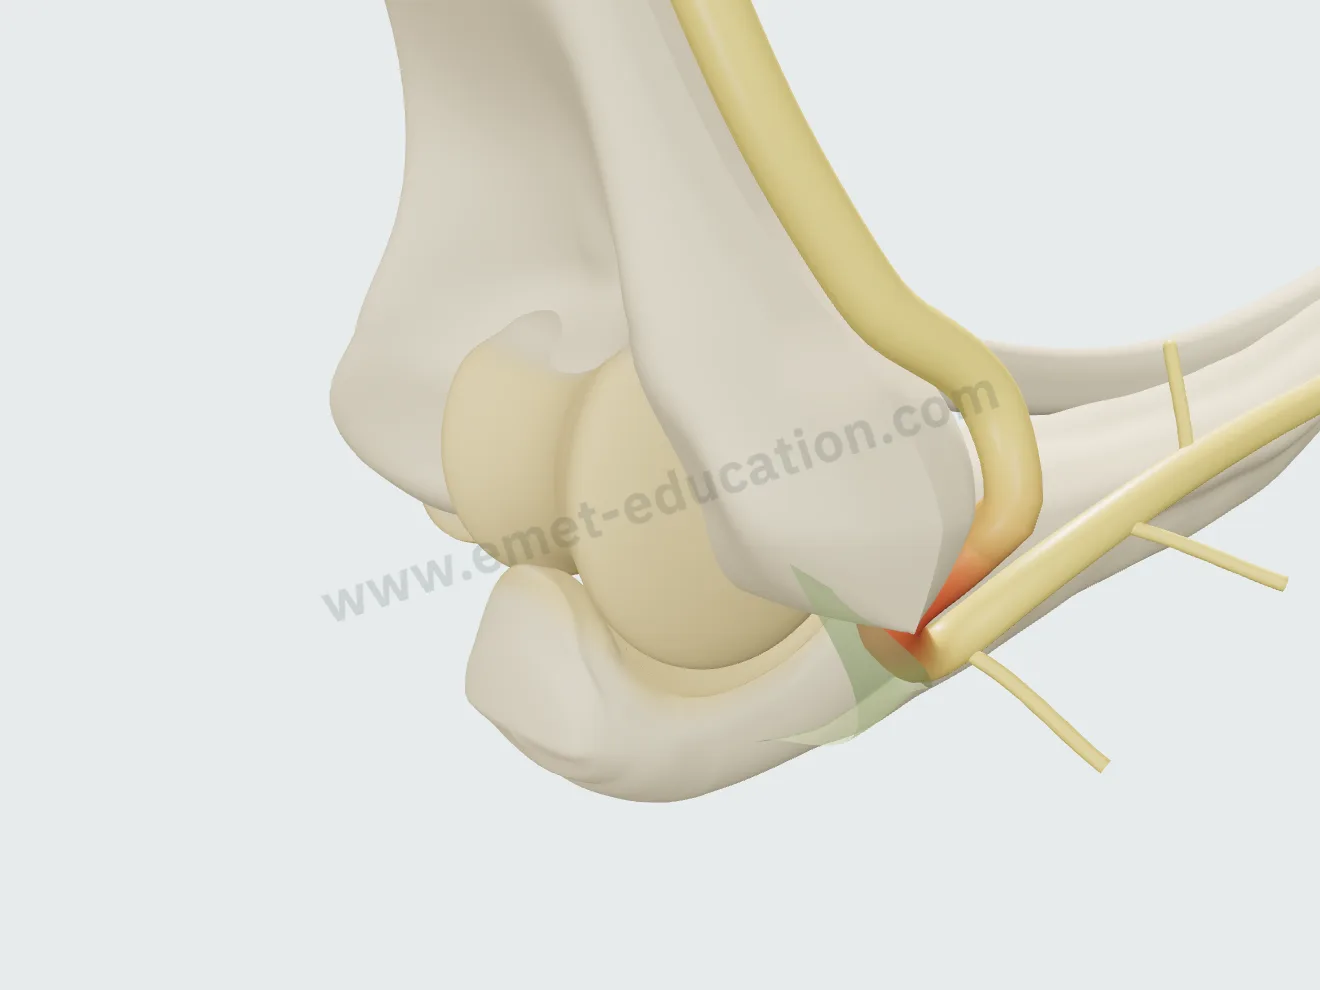
    Open the model and trace the ulnar nerve: arcade of Struthers, retroepicondylar groove, Osborne's ligament, cubital tunnel, branches to the flexor carpi ulnaris.

  2. 2

    Reproduce

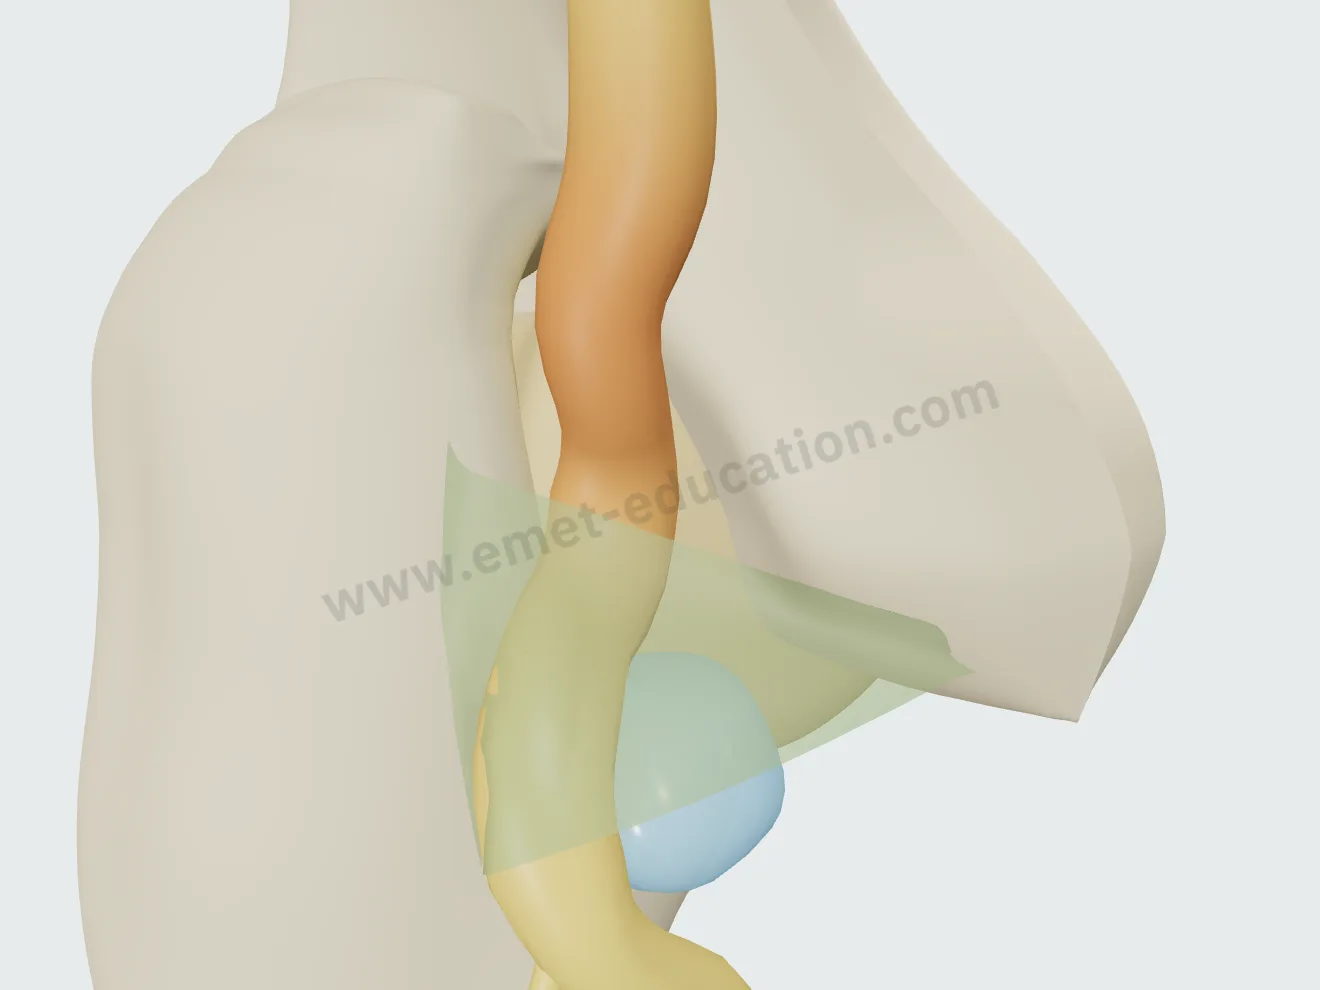
    Bend the elbow to show the mechanism, then set the lesion from the exam, nerve conduction studies or ultrasound: compression severity, nerve instability, space-occupying lesion. Then walk through the proposed treatment, step by step.

  3. 3

    Share

    Give the patient the QR code or an image: they find their own case, in their language.

Features

Explain in detail during the visit

Every setting updates the model live: you reproduce the lesion from your patient's workup in front of them, then walk through the treatment you recommend.

The mechanism and the lesions, in a few clicks

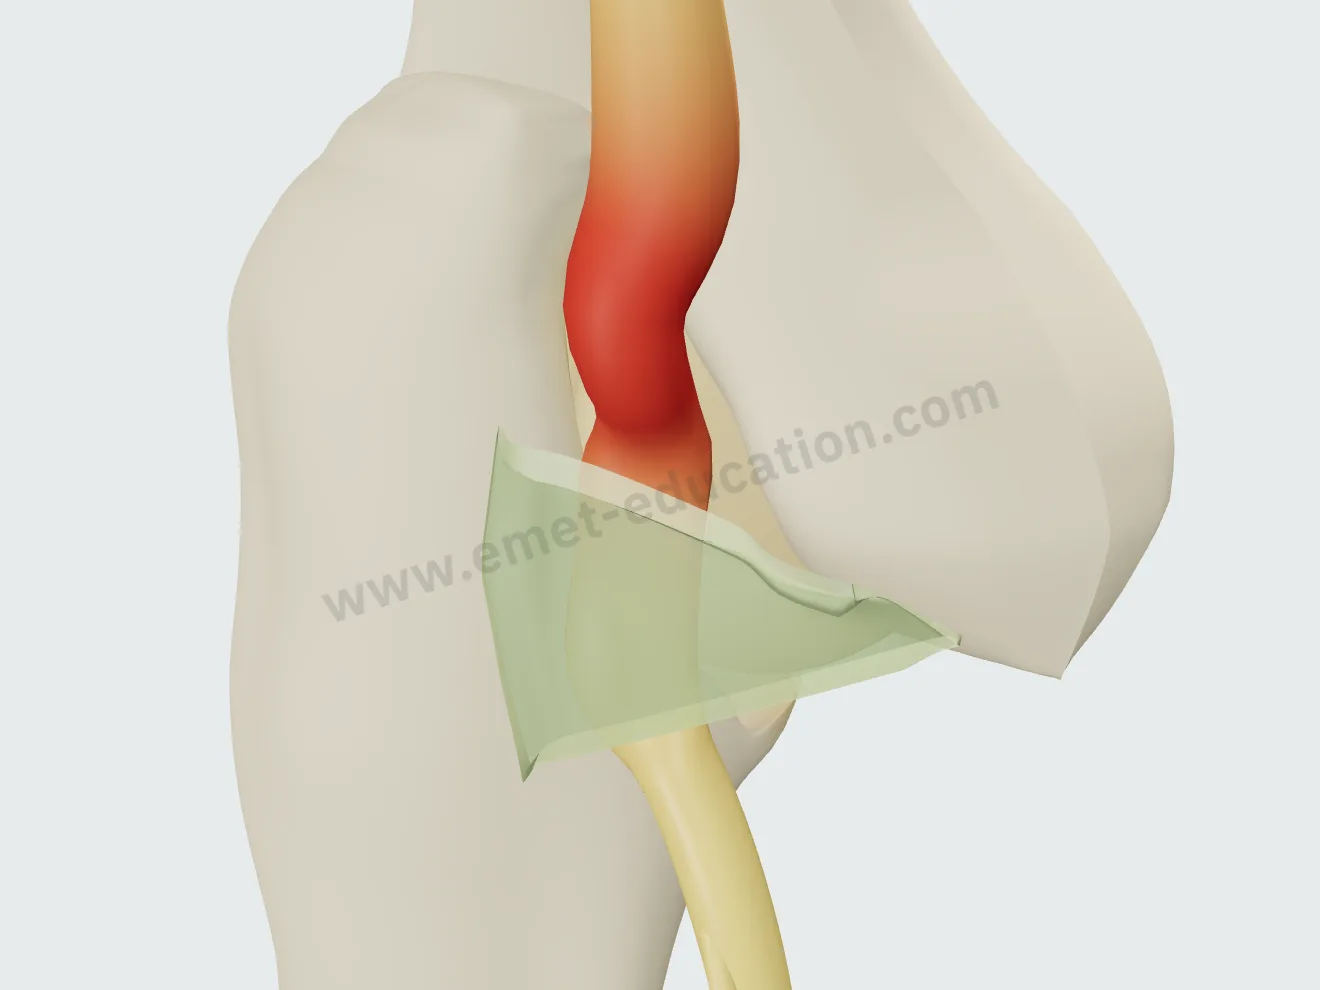
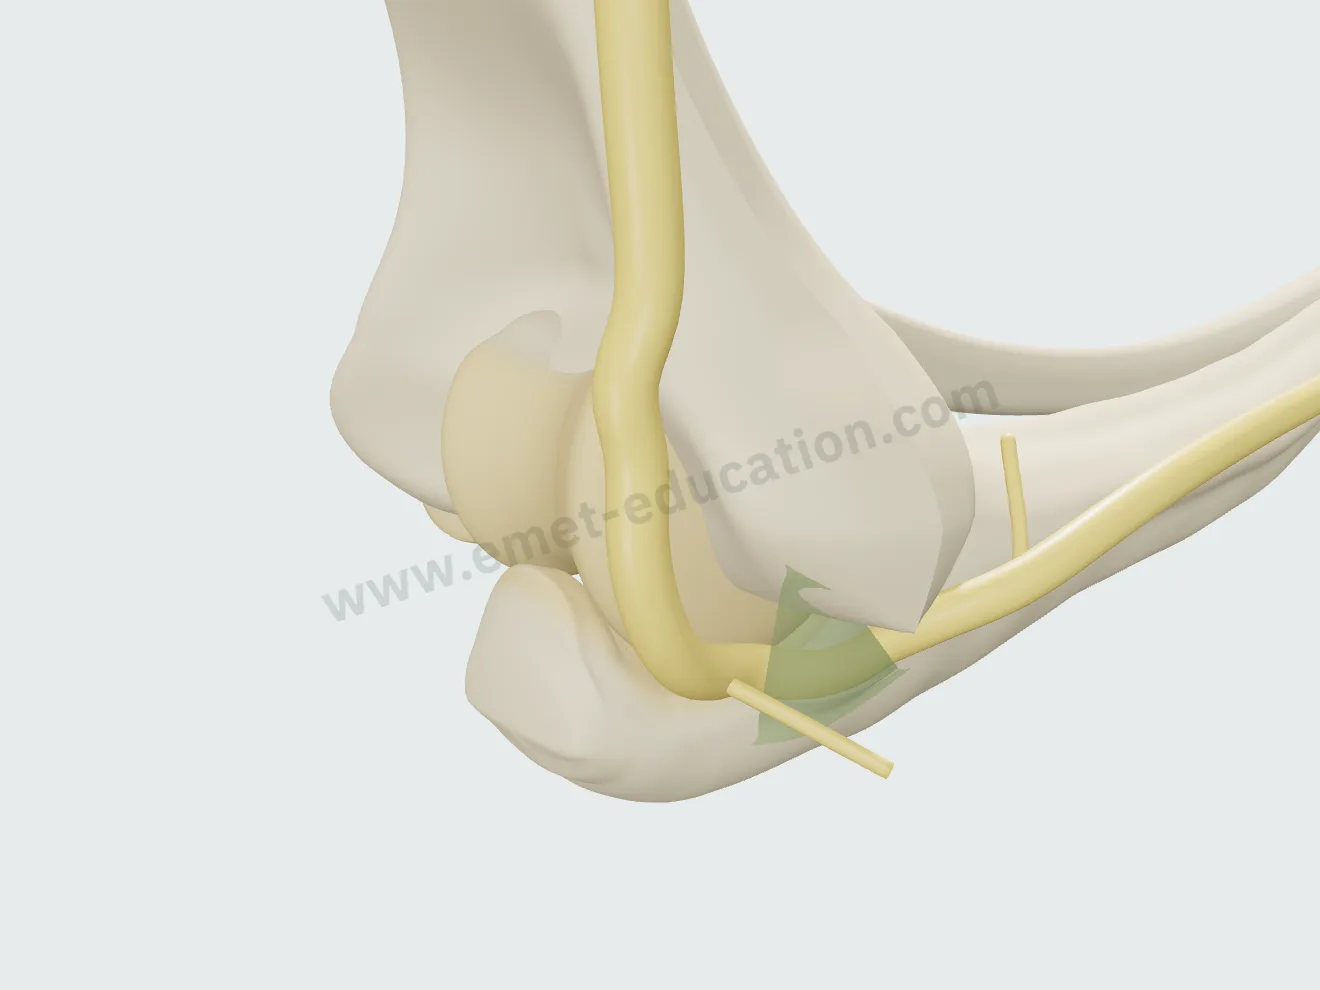
The “Movements” section bends the elbow; the “Pathology & lesions” panel sets the compression, the nerve instability and whatever occupies the tunnel. Lesions add up, and each one changes the model in front of the patient.

Bend the elbow, the tunnel closes

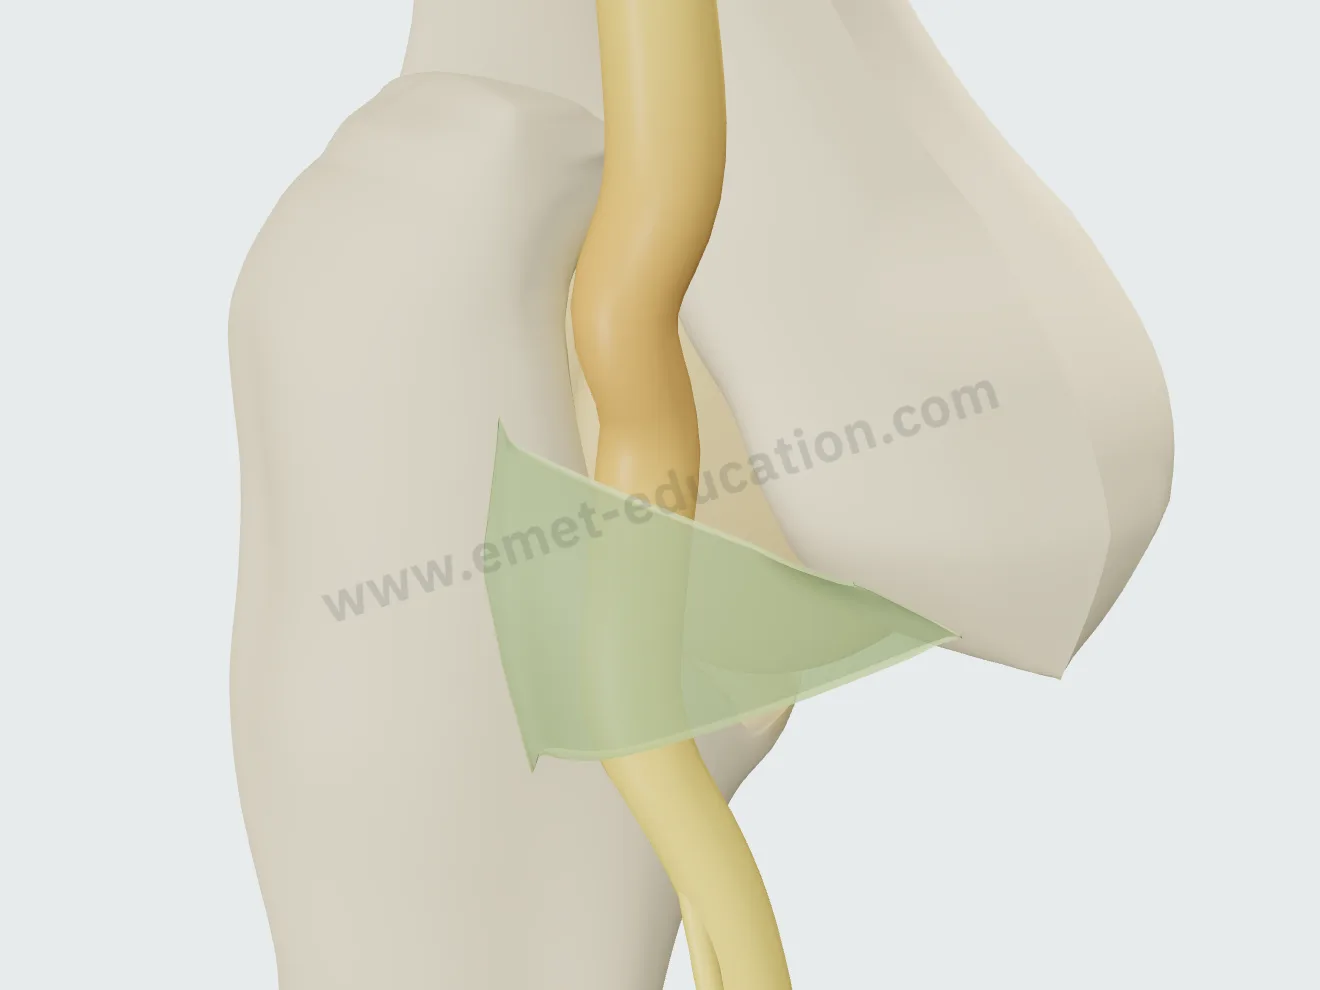
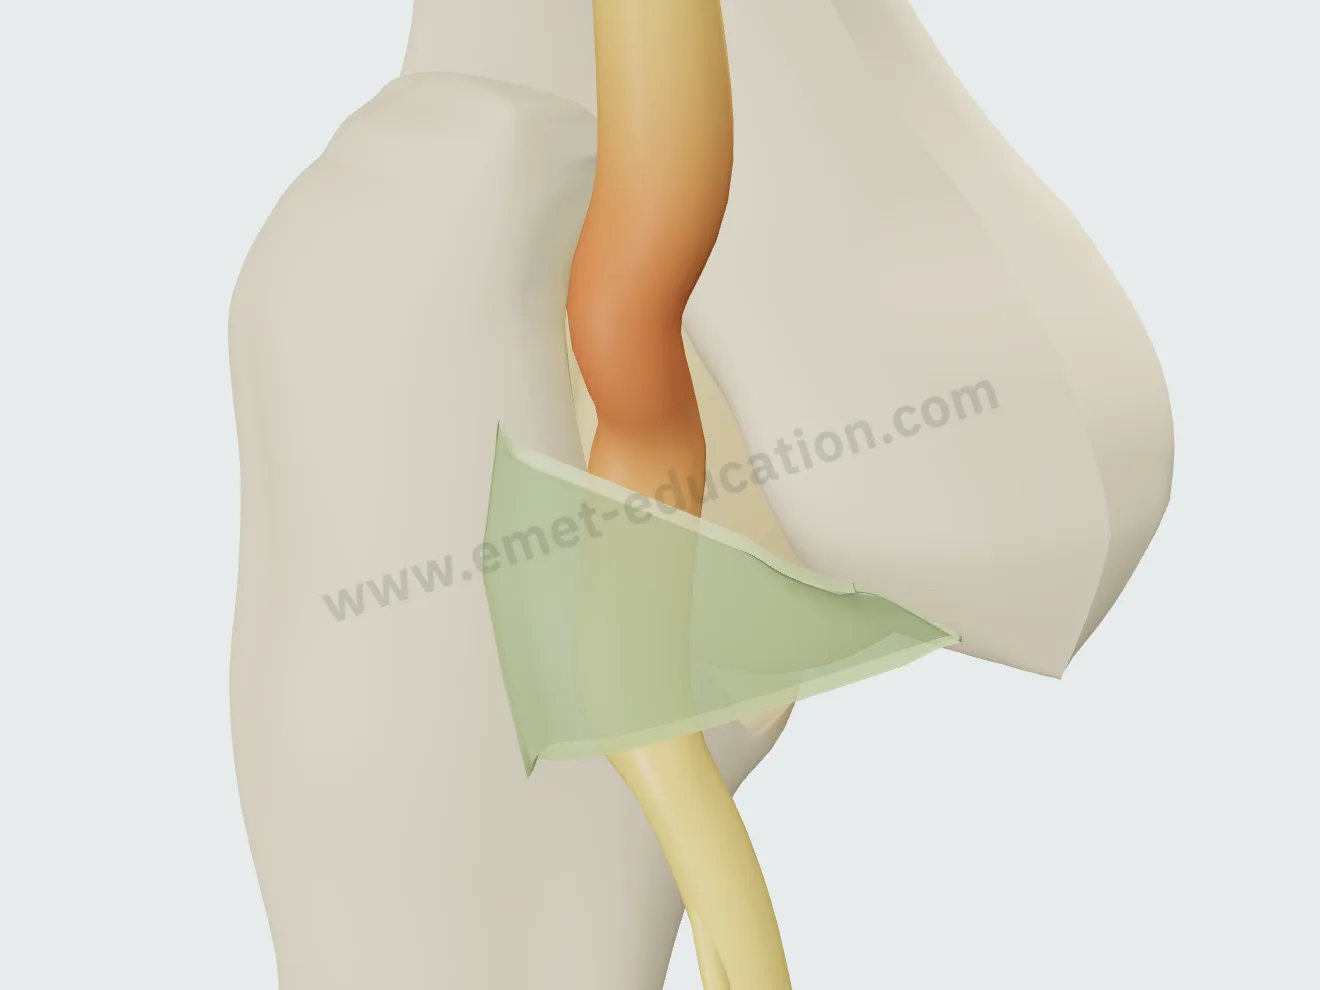
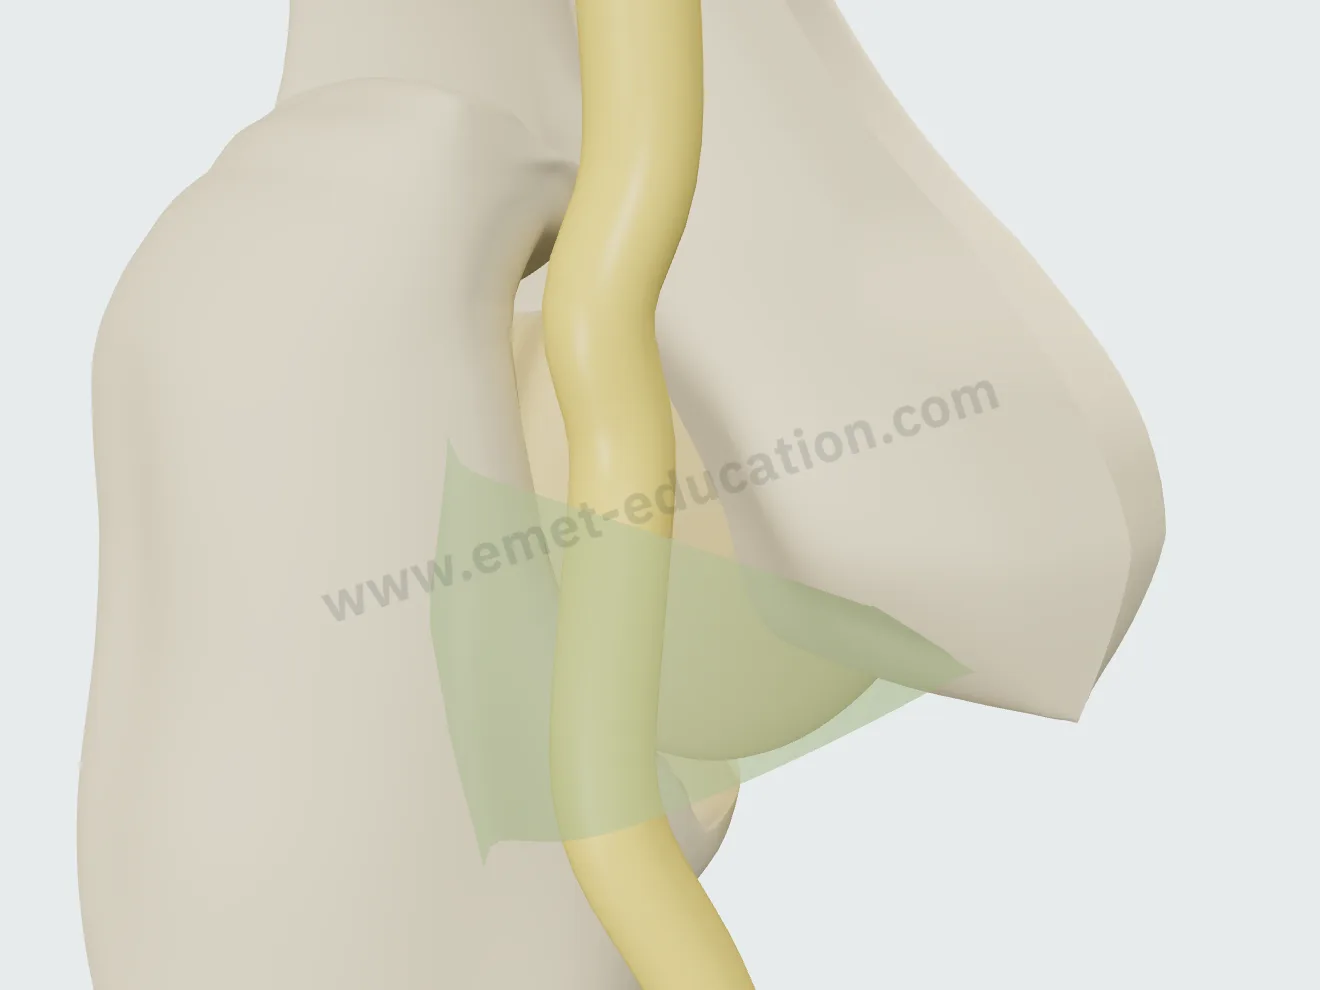
A slider from −5° to 145°, or “Bend the elbow” back and forth. Osborne's ligament, slack with the elbow straight, tightens between 45° and 90° and presses the nerve against the bone; below the slider, the ligament tension and nerve flattening are read on the model.
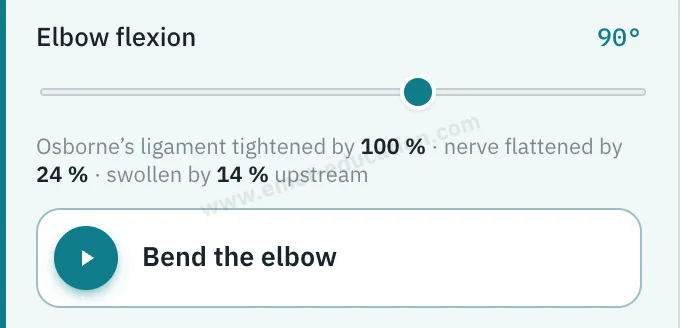
Model panel: elbow flexion at 90°, ligament tension measurement, “Bend the elbow” button.
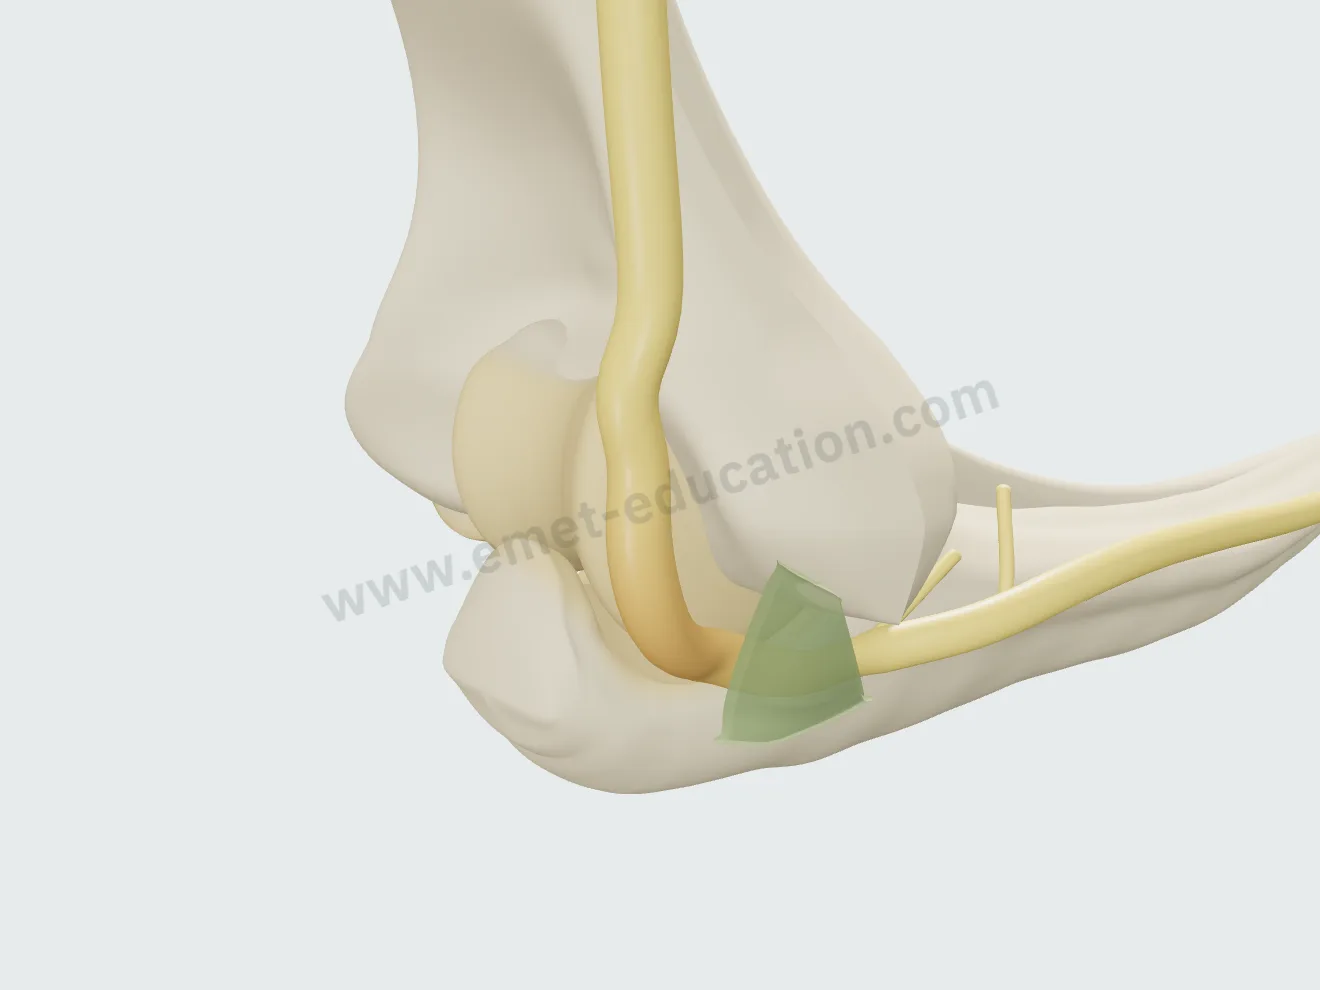
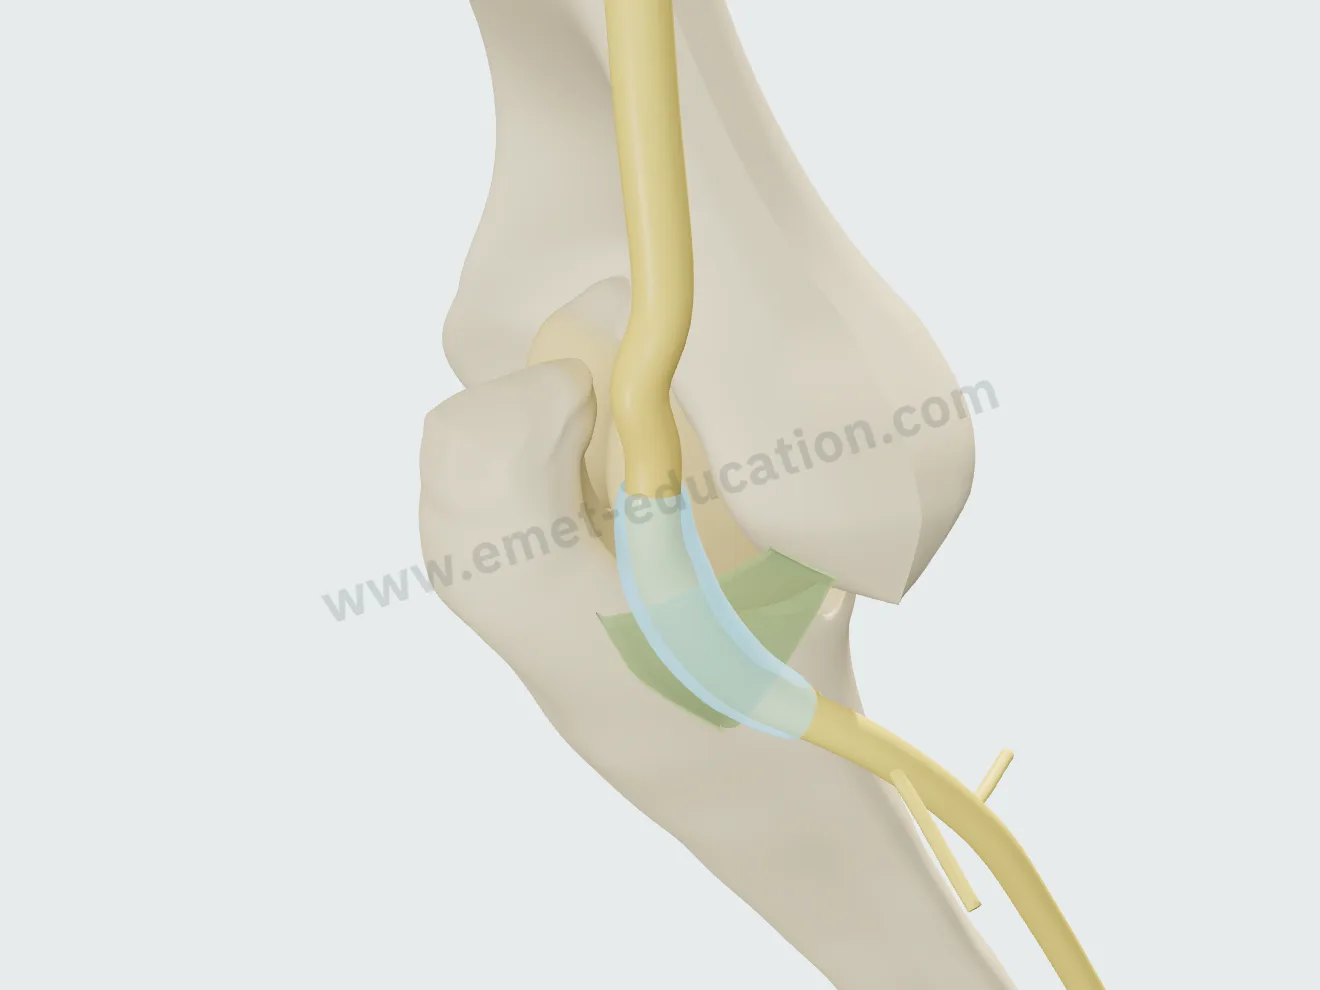
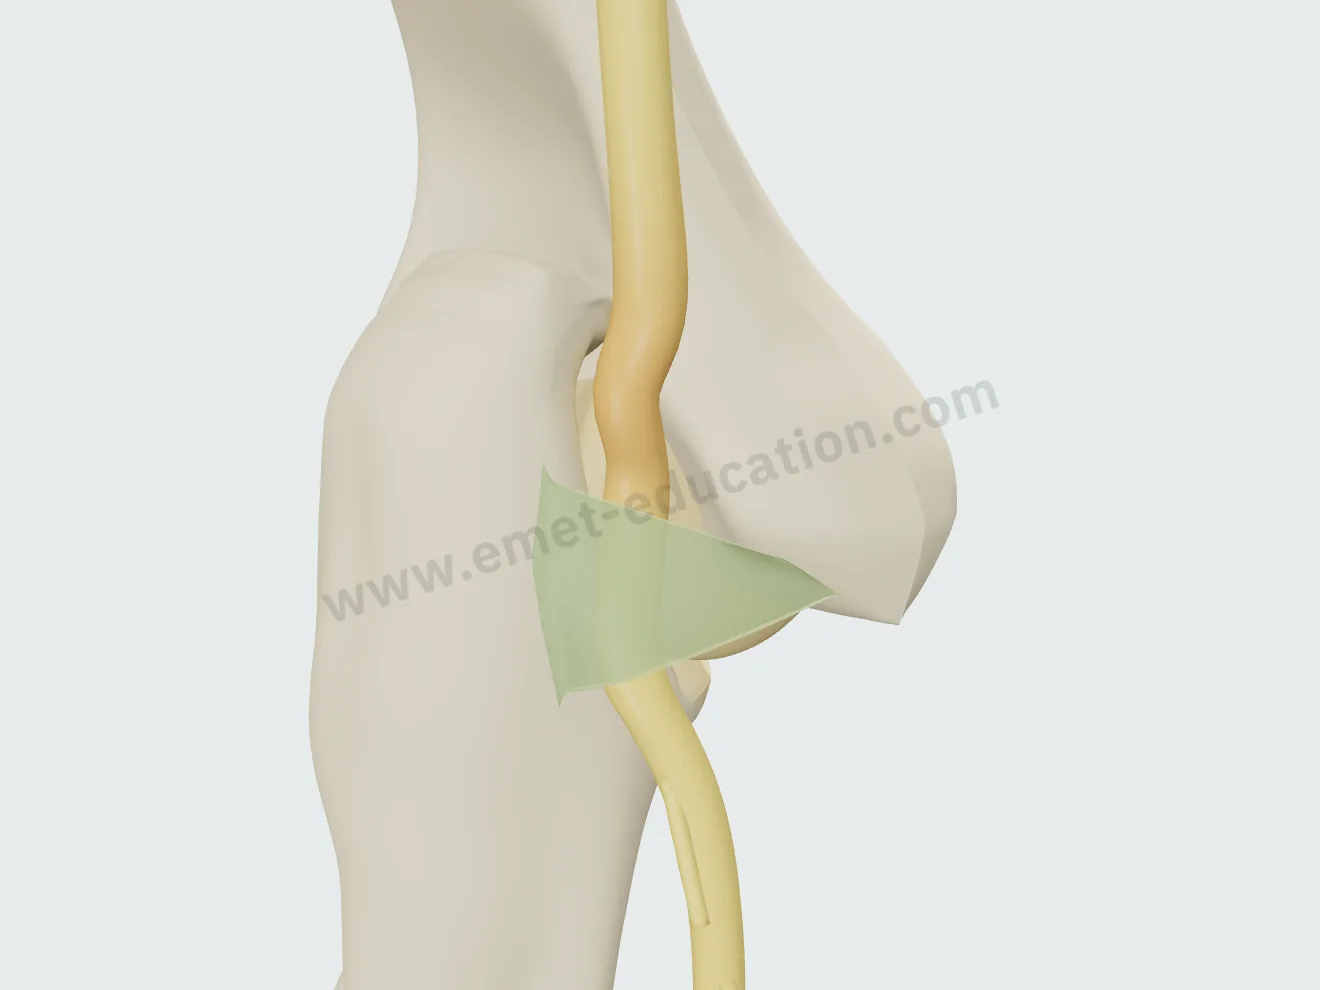
Elbow straight, mild compression: Osborne's ligament slack over the nerve, in its groove.
Elbow · straight
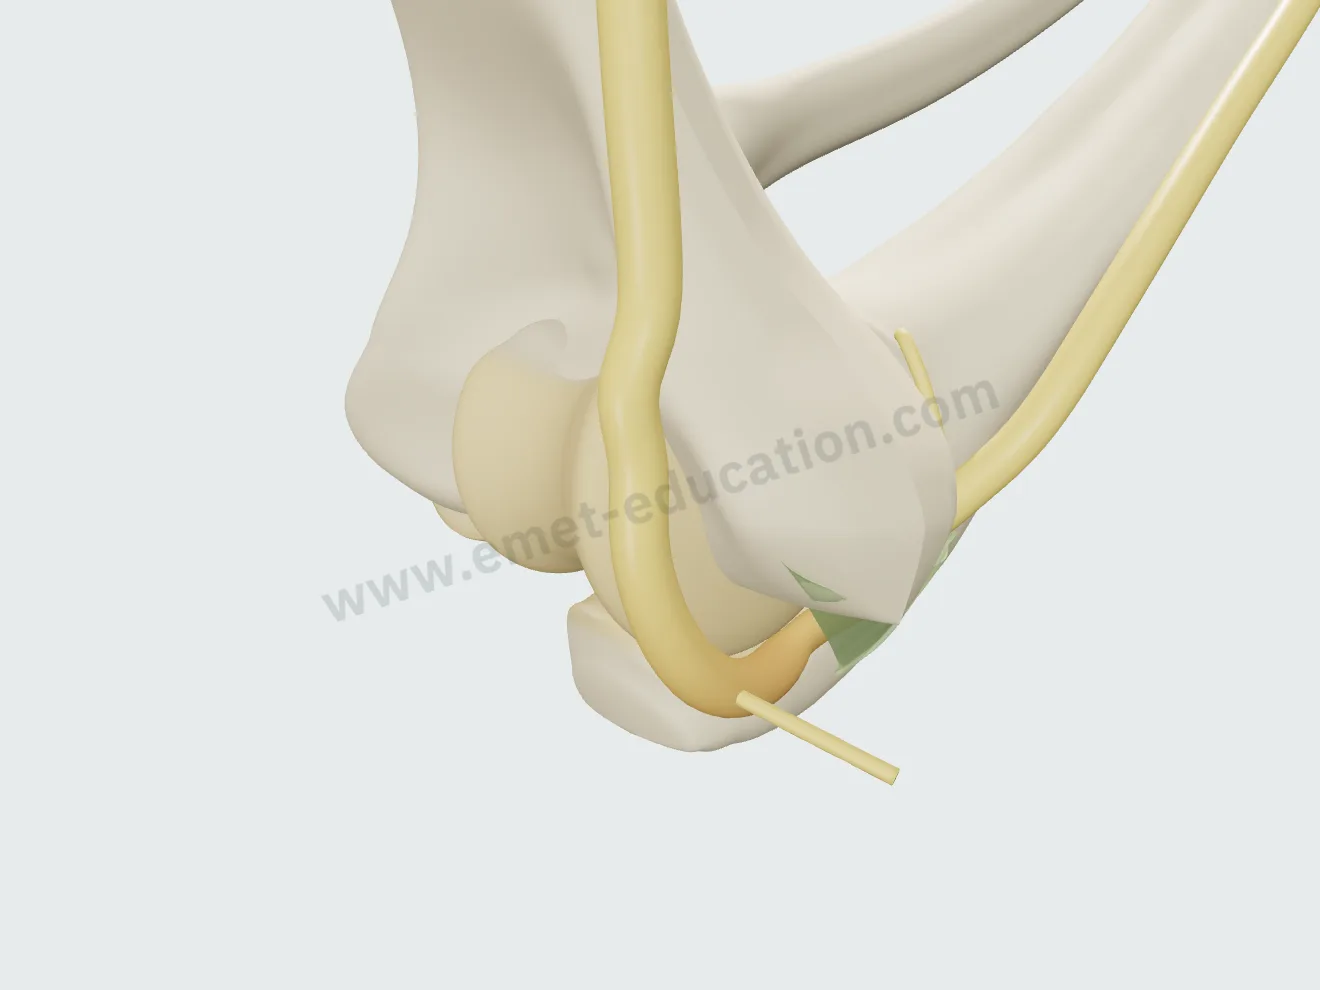
Elbow flexed to 90°: the tight Osborne's ligament presses the nerve against the bone.
Flexion · 90°
Elbow flexed to 130°: the nerve stretched and flattened under the band.
Flexion · 130°

The treatment, step by step

Three procedures, played step by step, continuously or one step at a time: in situ neurolysis, anterior transposition, injection. Once the procedure is done, bend the elbow: the released or transposed nerve no longer tightens.

Ulnar nerve release

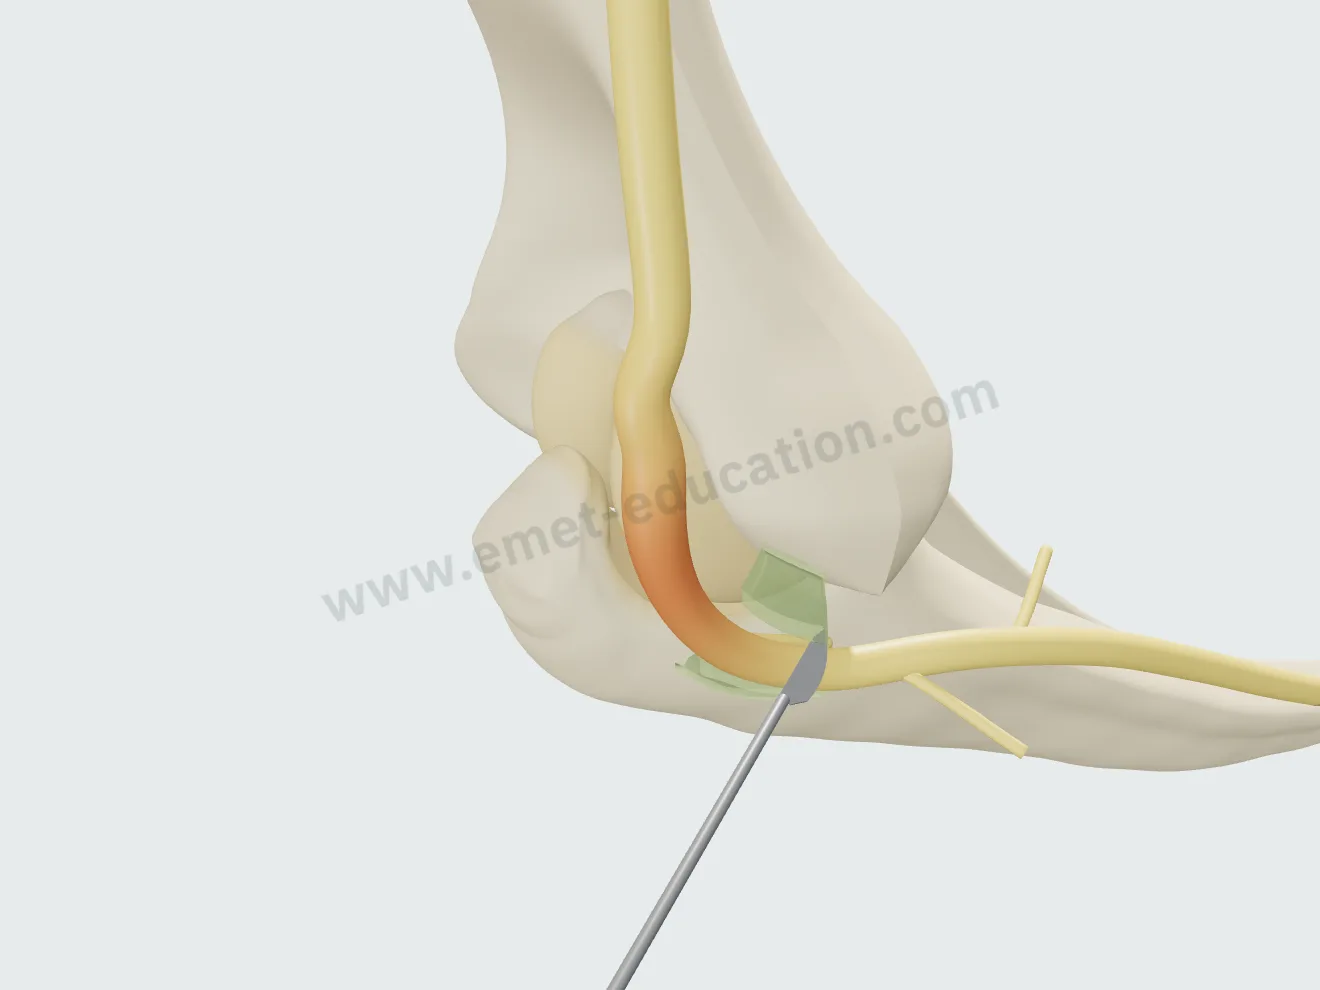
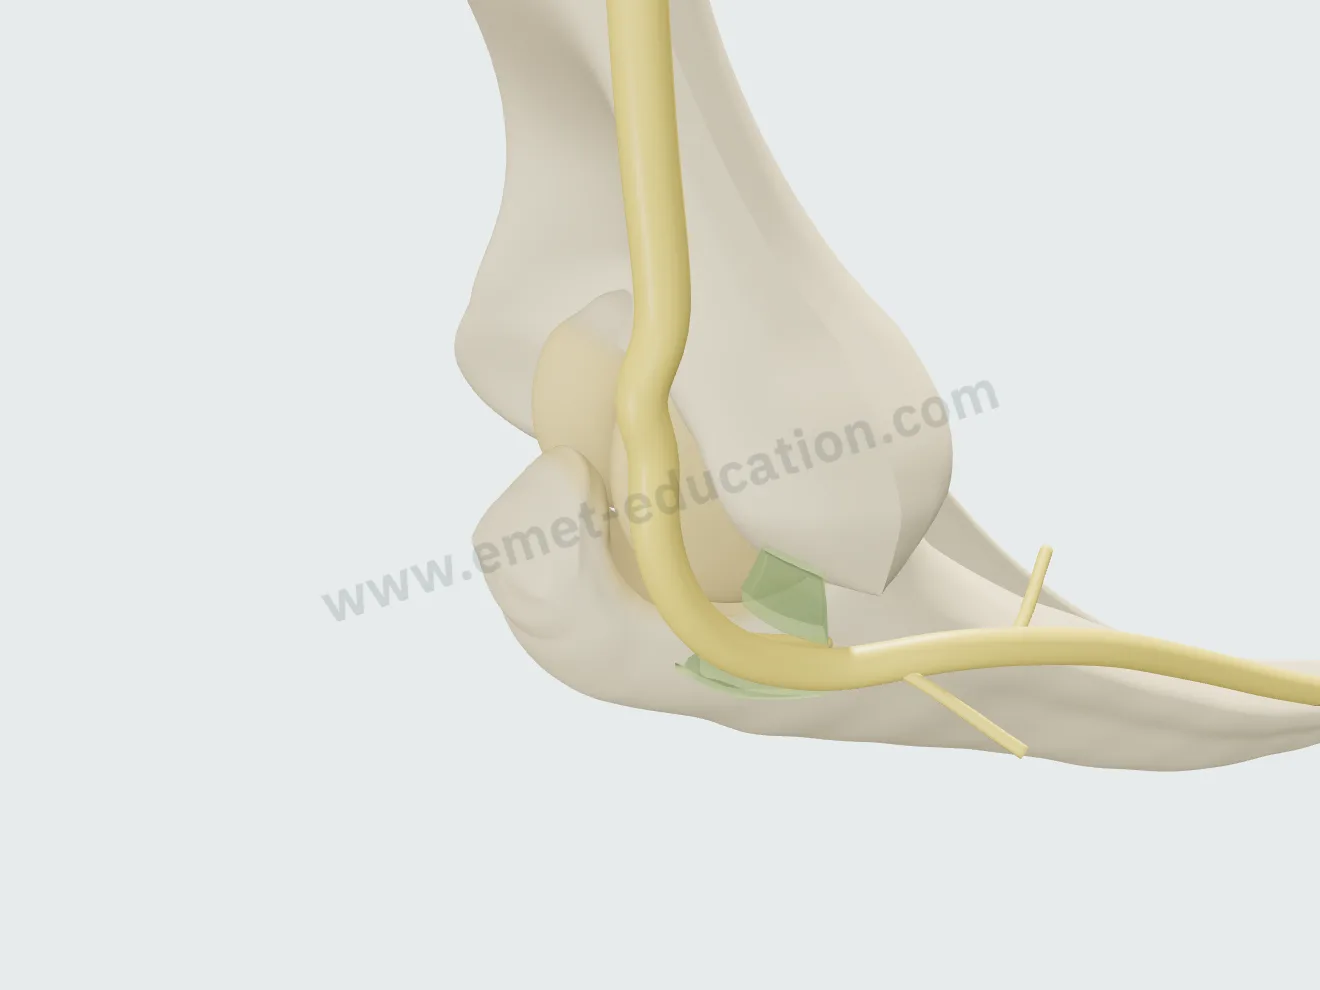
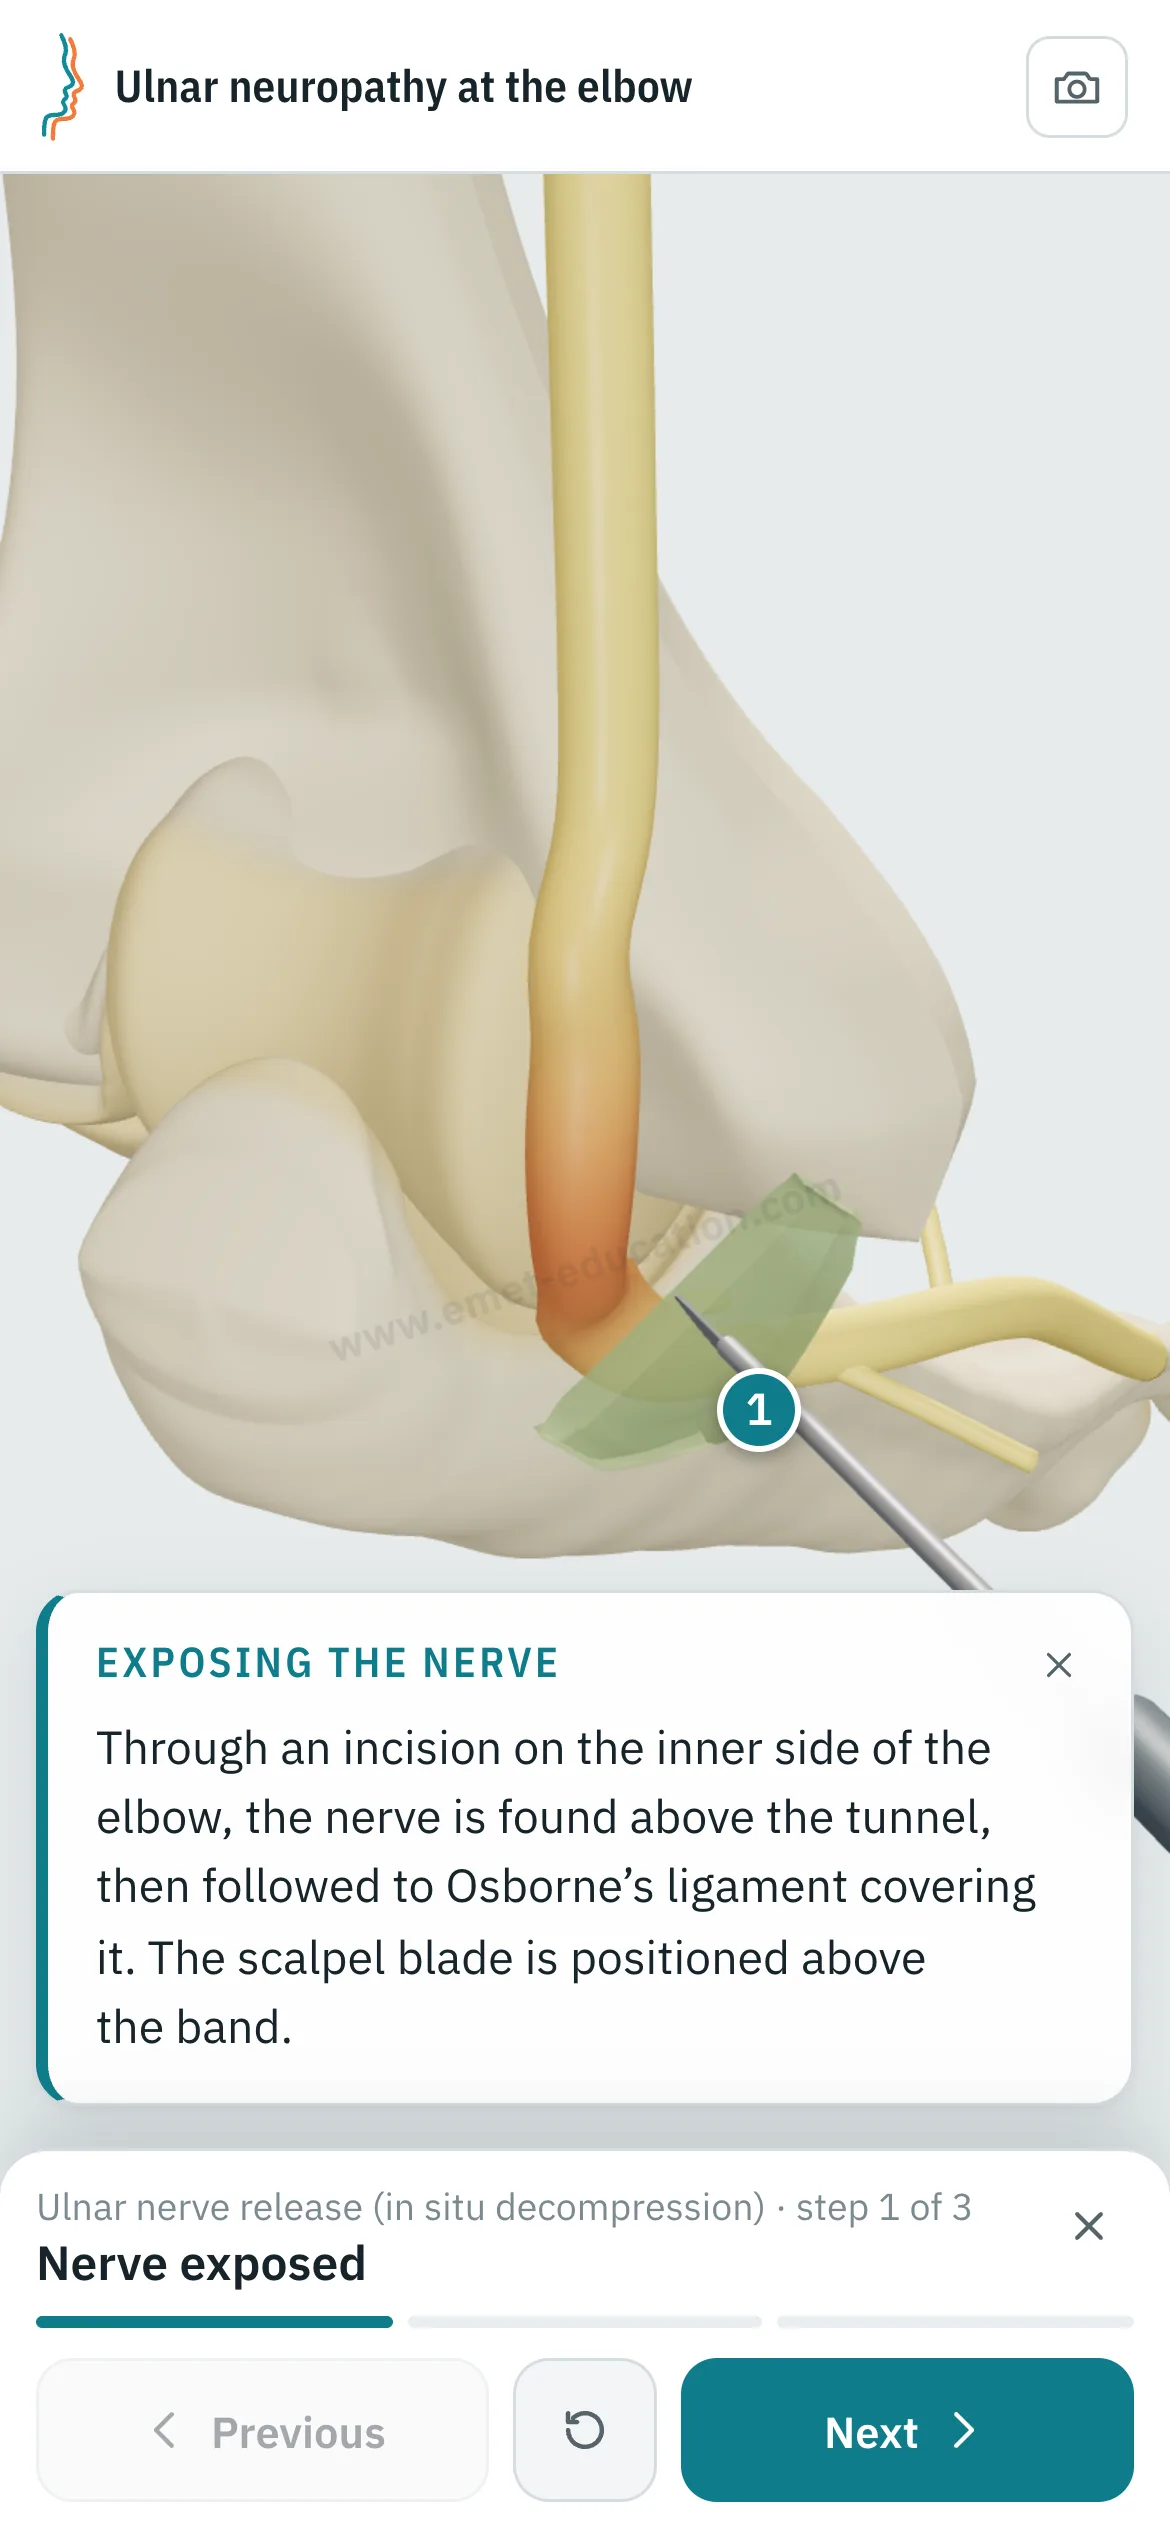
In situ decompression: Osborne's ligament is divided along the nerve, its edges retract, the nerve regains its shape in its groove.

Neurolysis, step 1: the nerve exposed, the scalpel over Osborne's ligament.
1Nerve exposed
Neurolysis, step 2: Osborne's ligament divided along the nerve, its two edges retracted.
2Ligament divided
Neurolysis, step 3: the nerve released in its groove, the edema and redness subsiding.
3Nerve released

Anterior transposition

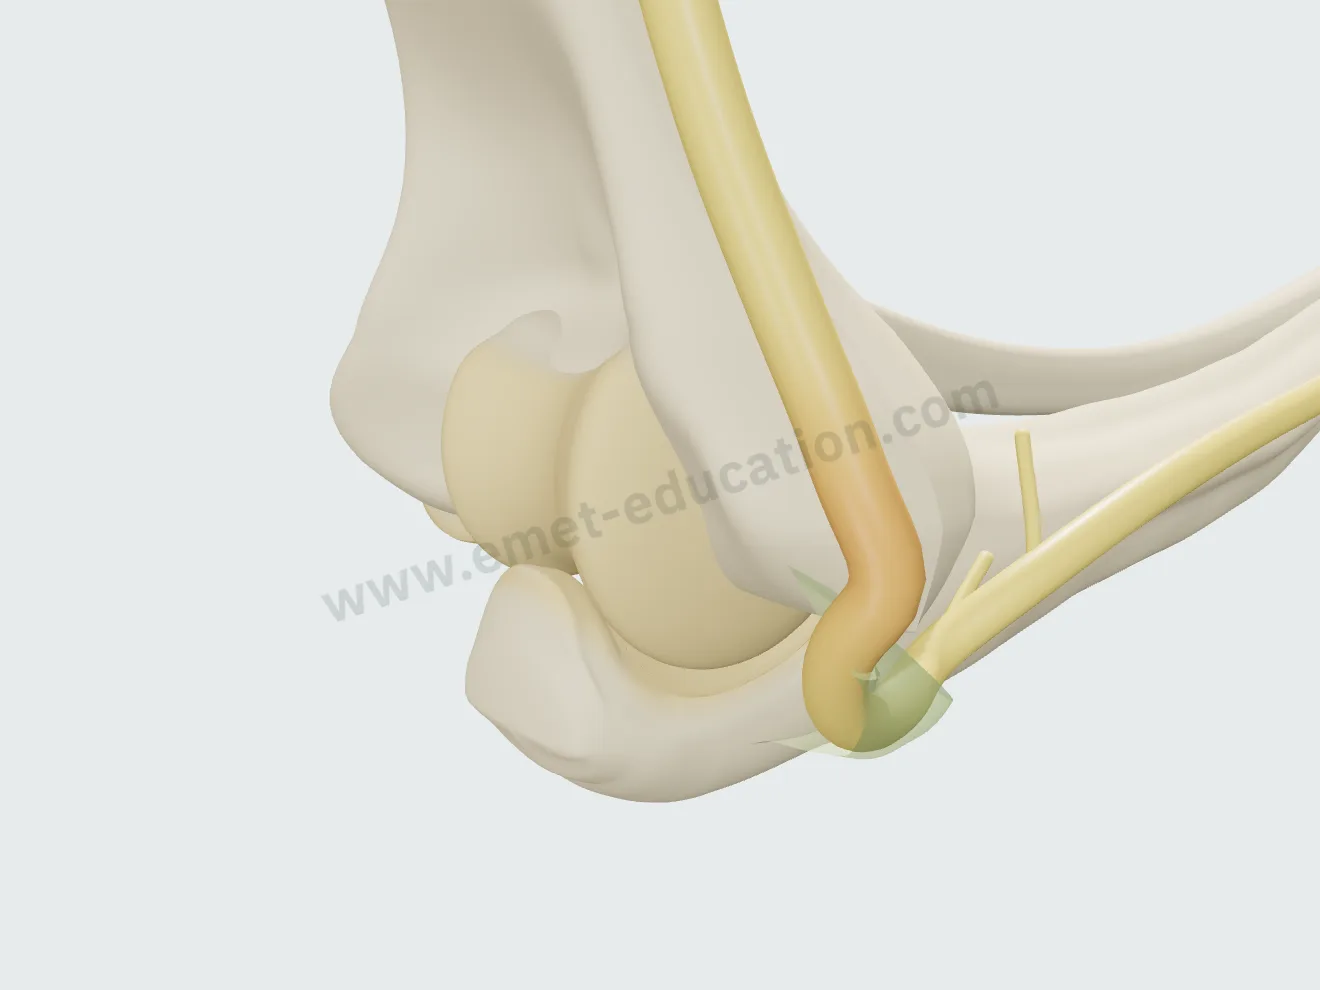
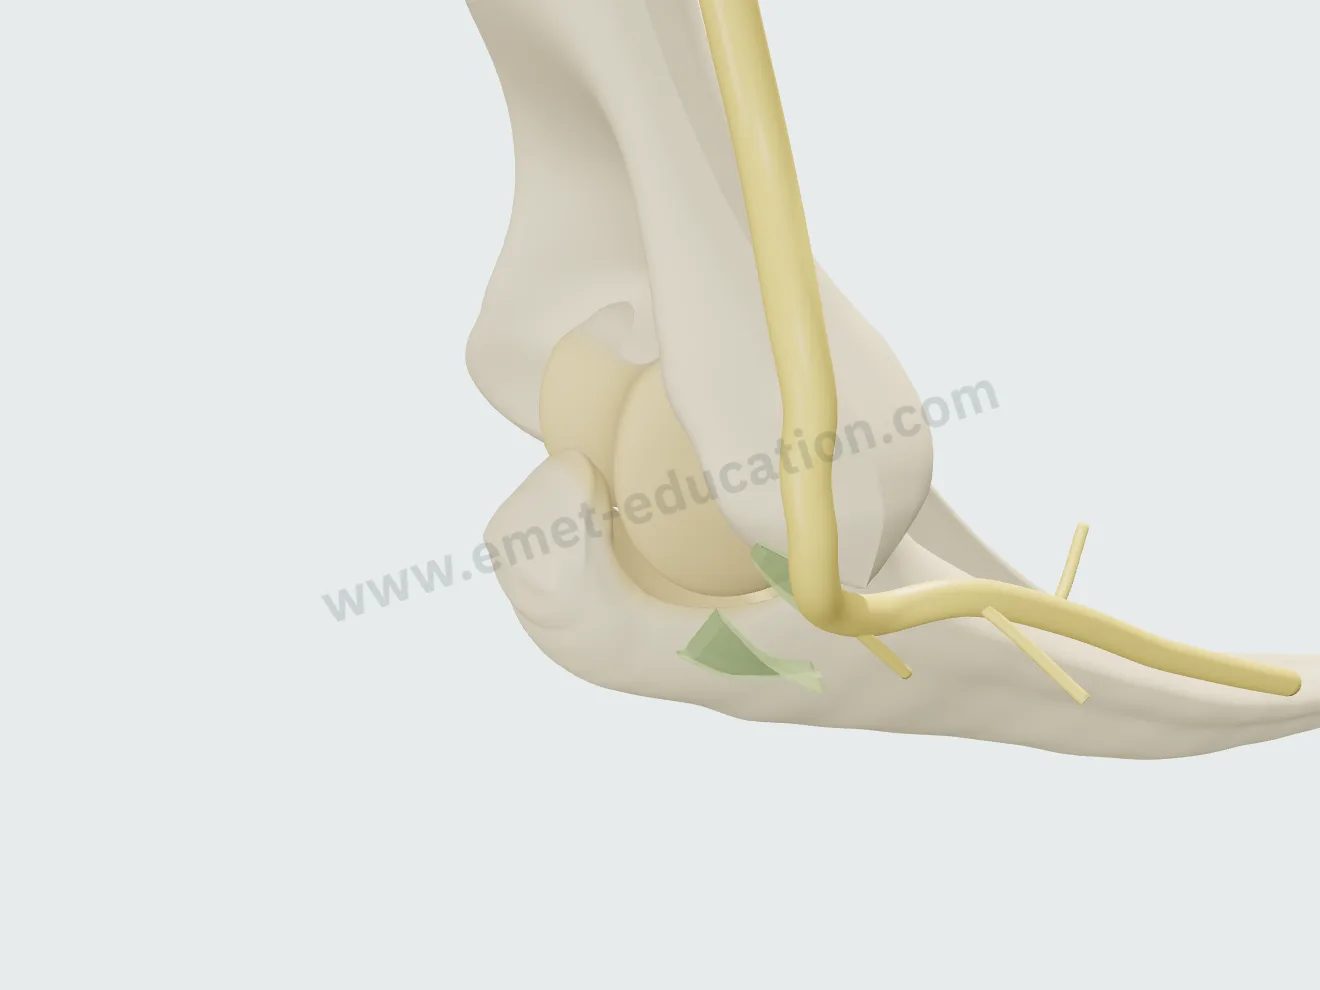
After neurolysis, for an unstable nerve: arcade of Struthers released, nerve moved in front of the medial epicondyle, held by a fascial sling.

Transposition, step 1: the arcade of Struthers released, the nerve lifted out of its groove.
1Nerve mobilized
Transposition, step 2: the nerve moved in front of the medial epicondyle.
2Nerve transposed
Transposition, step 3: a fascial sling passed over the transposed nerve.
3Sling placed

Cubital tunnel injection

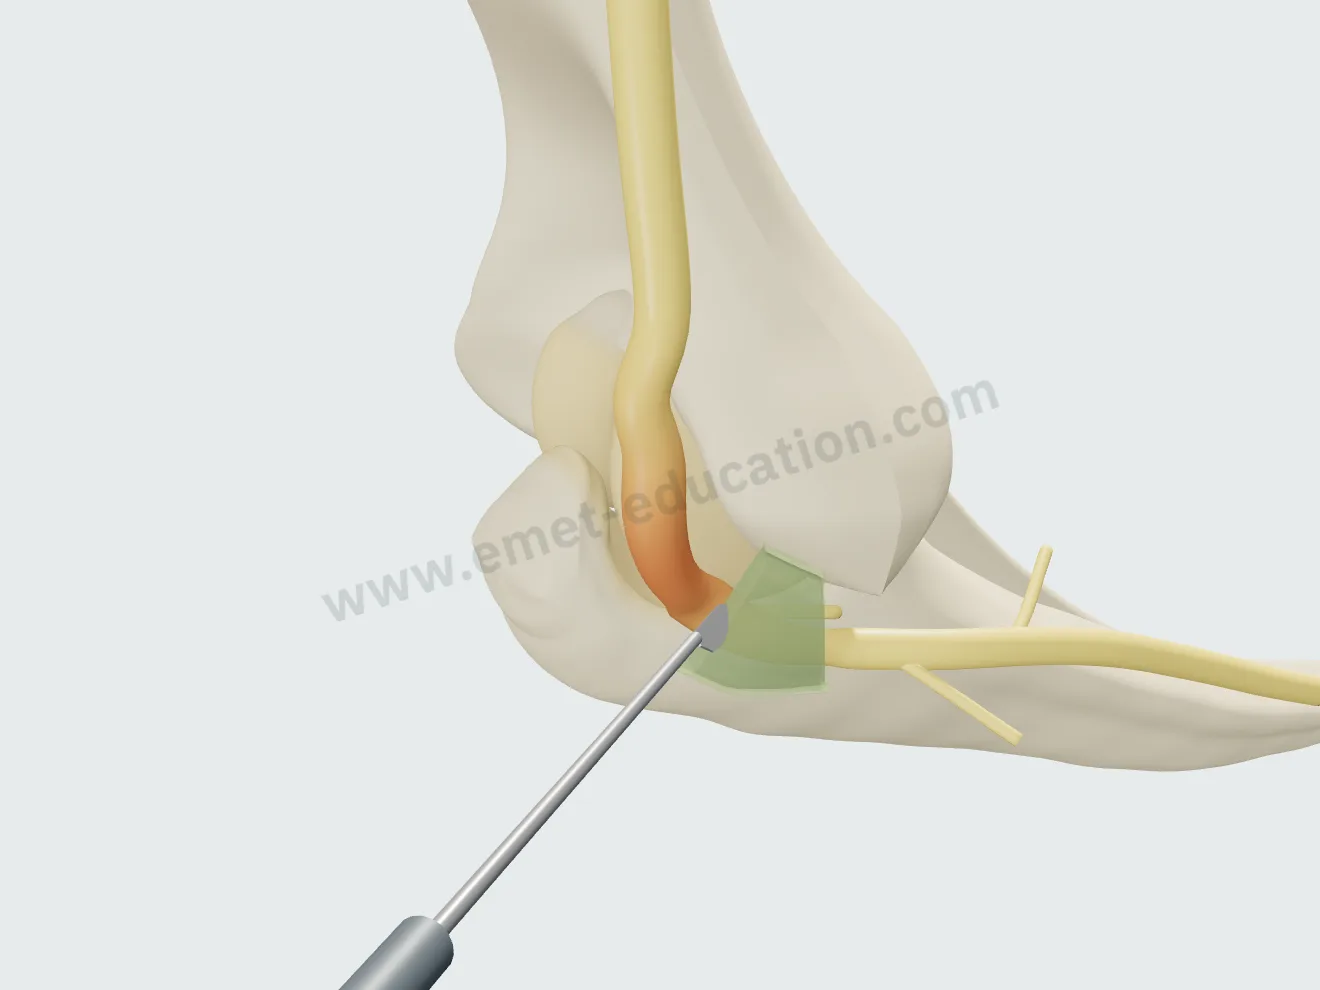
For milder cases: the needle stops against the nerve, the medication spreads as a sleeve under the band, the edema subsides.

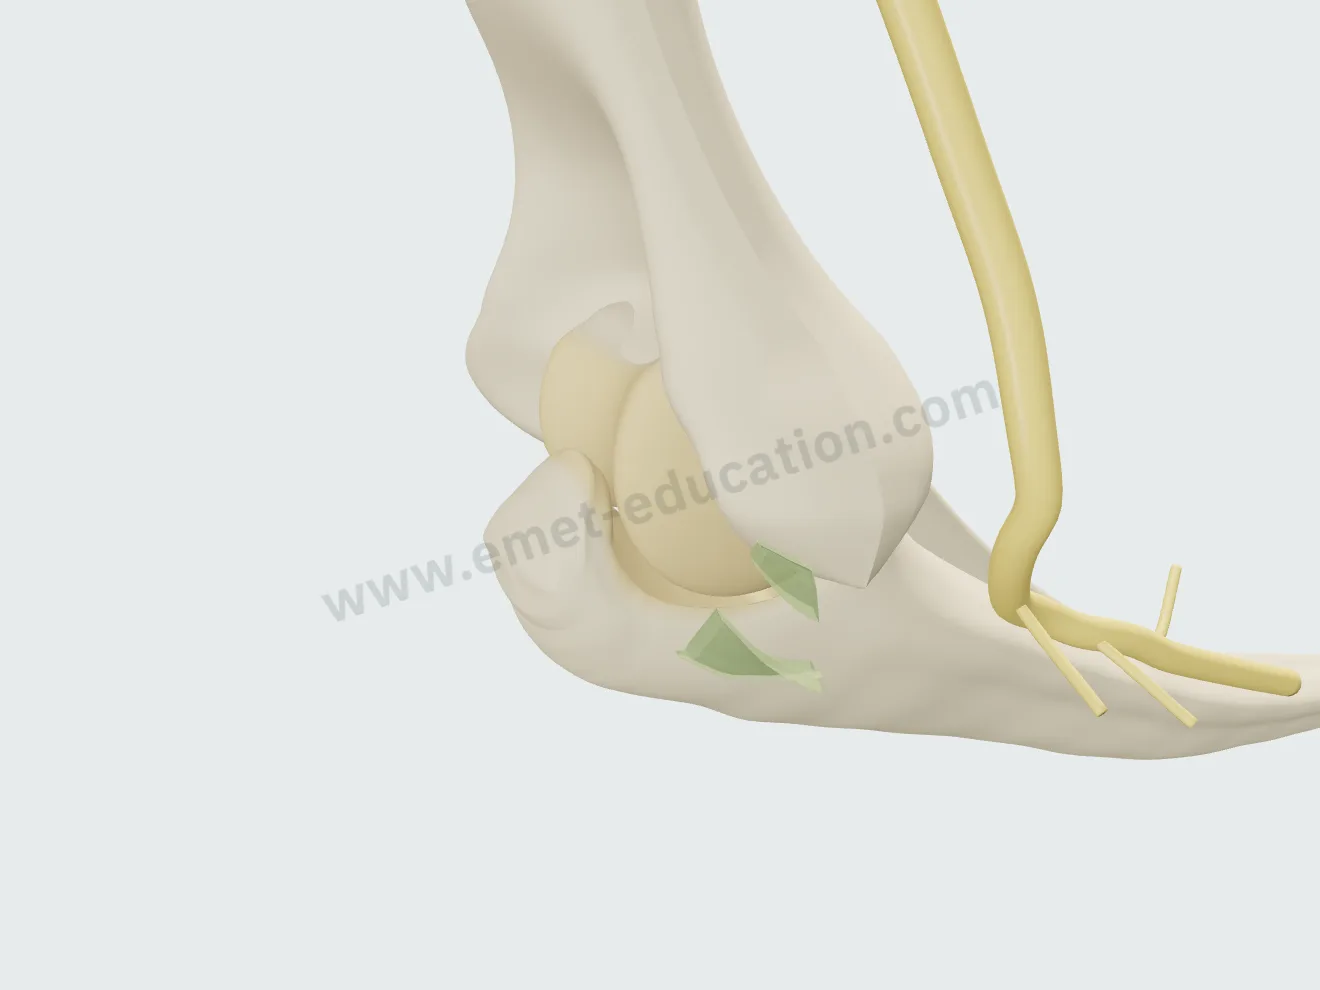
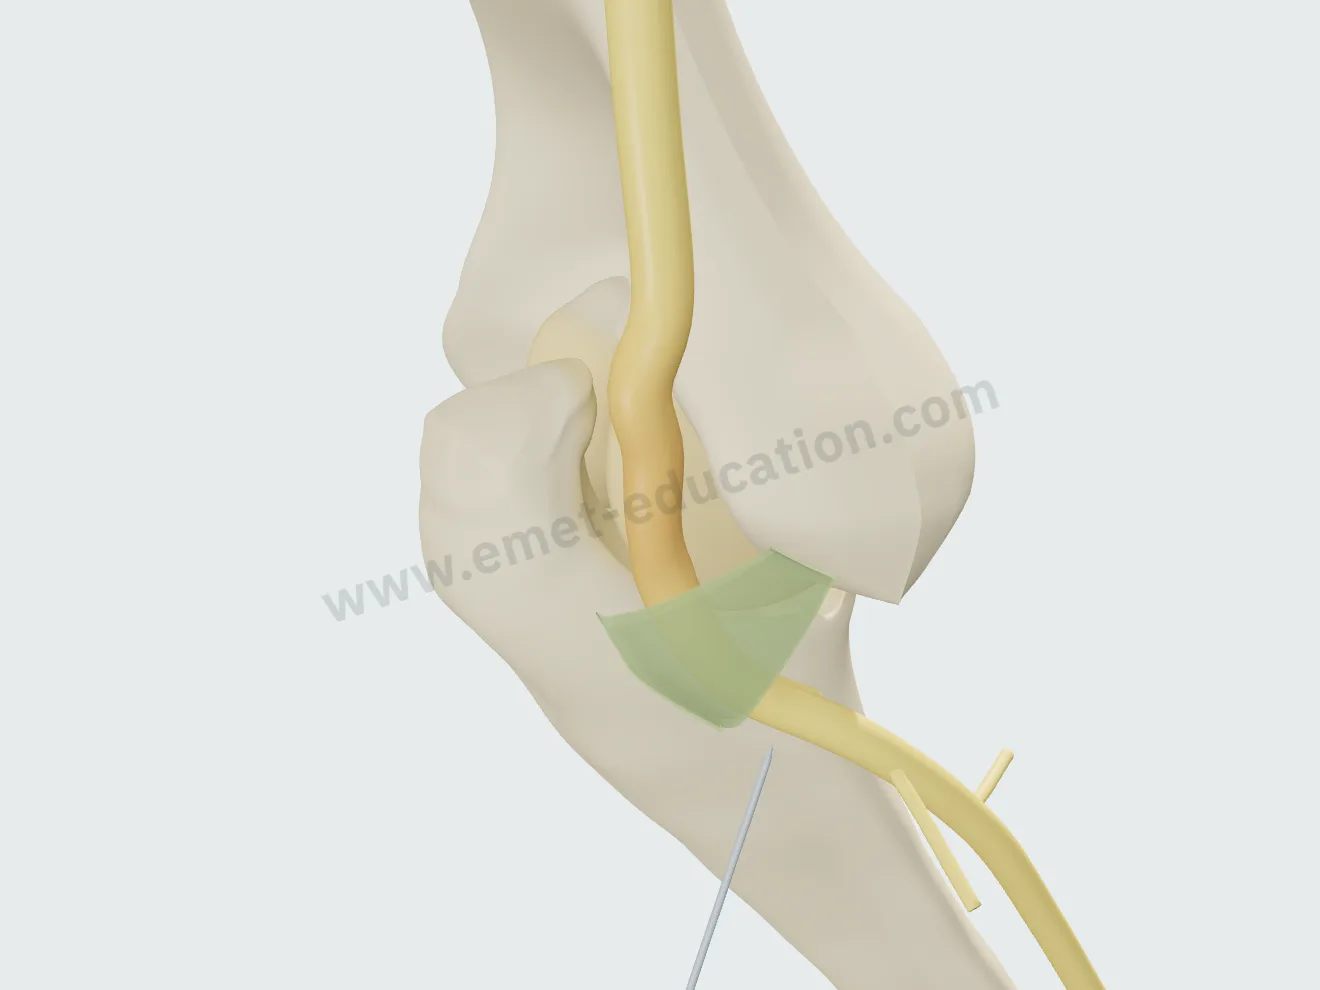
Injection, step 1: the needle stopped against the nerve, just distal to Osborne's ligament.
1Needle in place
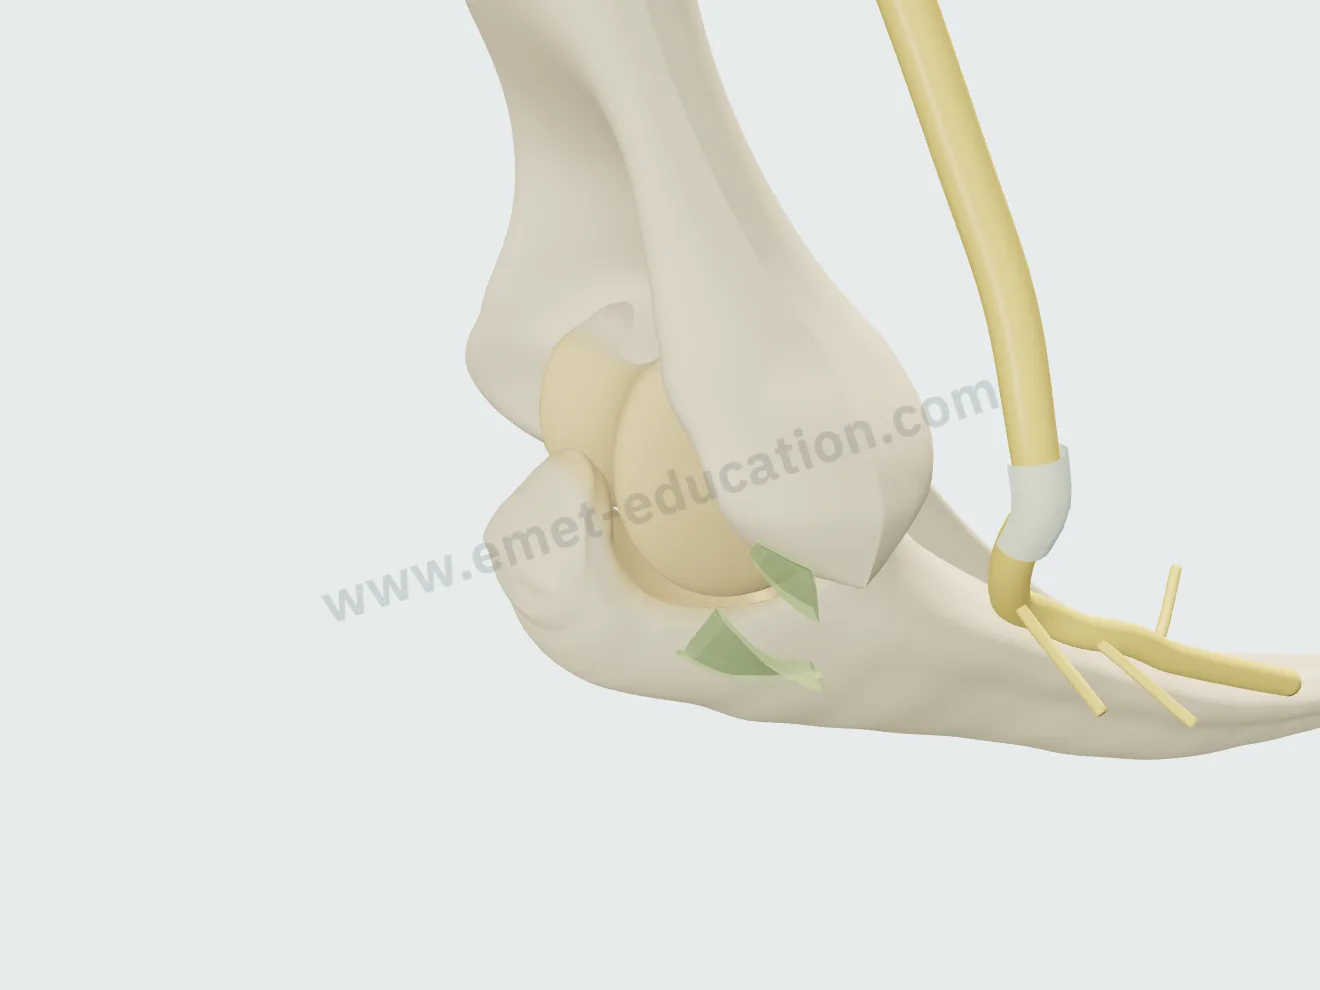
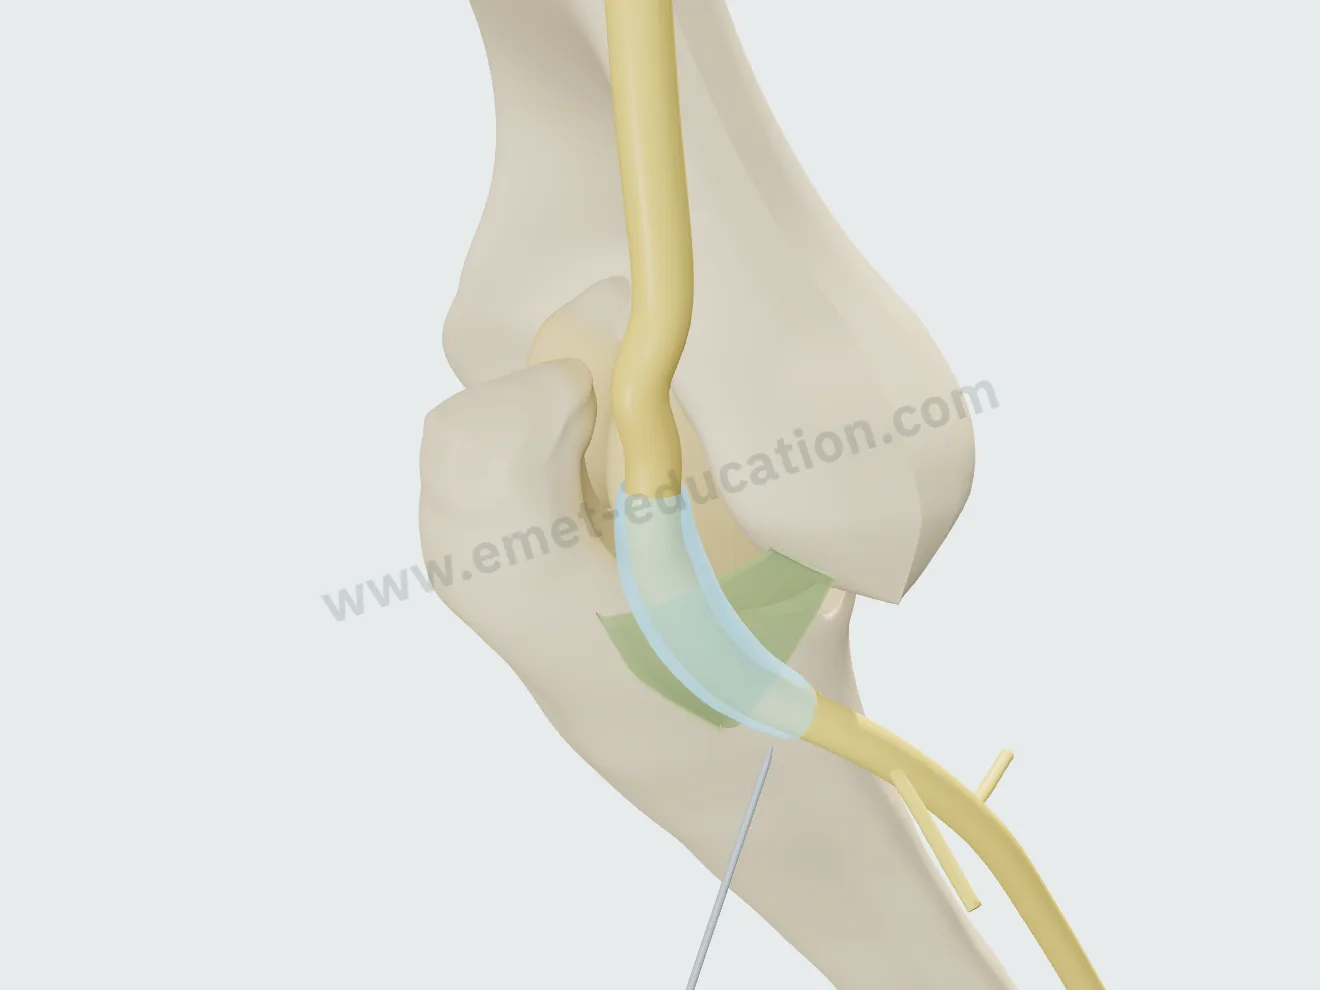
Injection, step 2: the medication spread as a sleeve around the nerve, under the band.
2Injection
Injection, step 3: the needle removed, the medication stays around the nerve.
3Needle removed

After the visit

The patient leaves with their 3D model

They scan the QR code: the model, their findings and the proposed treatment follow them on their phone, in their language.

The model, exactly as you set it

At the end of the visit, the Consultation panel shows the anatomical findings, the proposed treatment and a QR code. The patient scans it and finds the model on their phone exactly as you set it, in their language.

  • Their lesions, and the proposed treatment to replay step by step.
  • Their anatomical findings and the explanatory card.
  • No identifying data in the link.
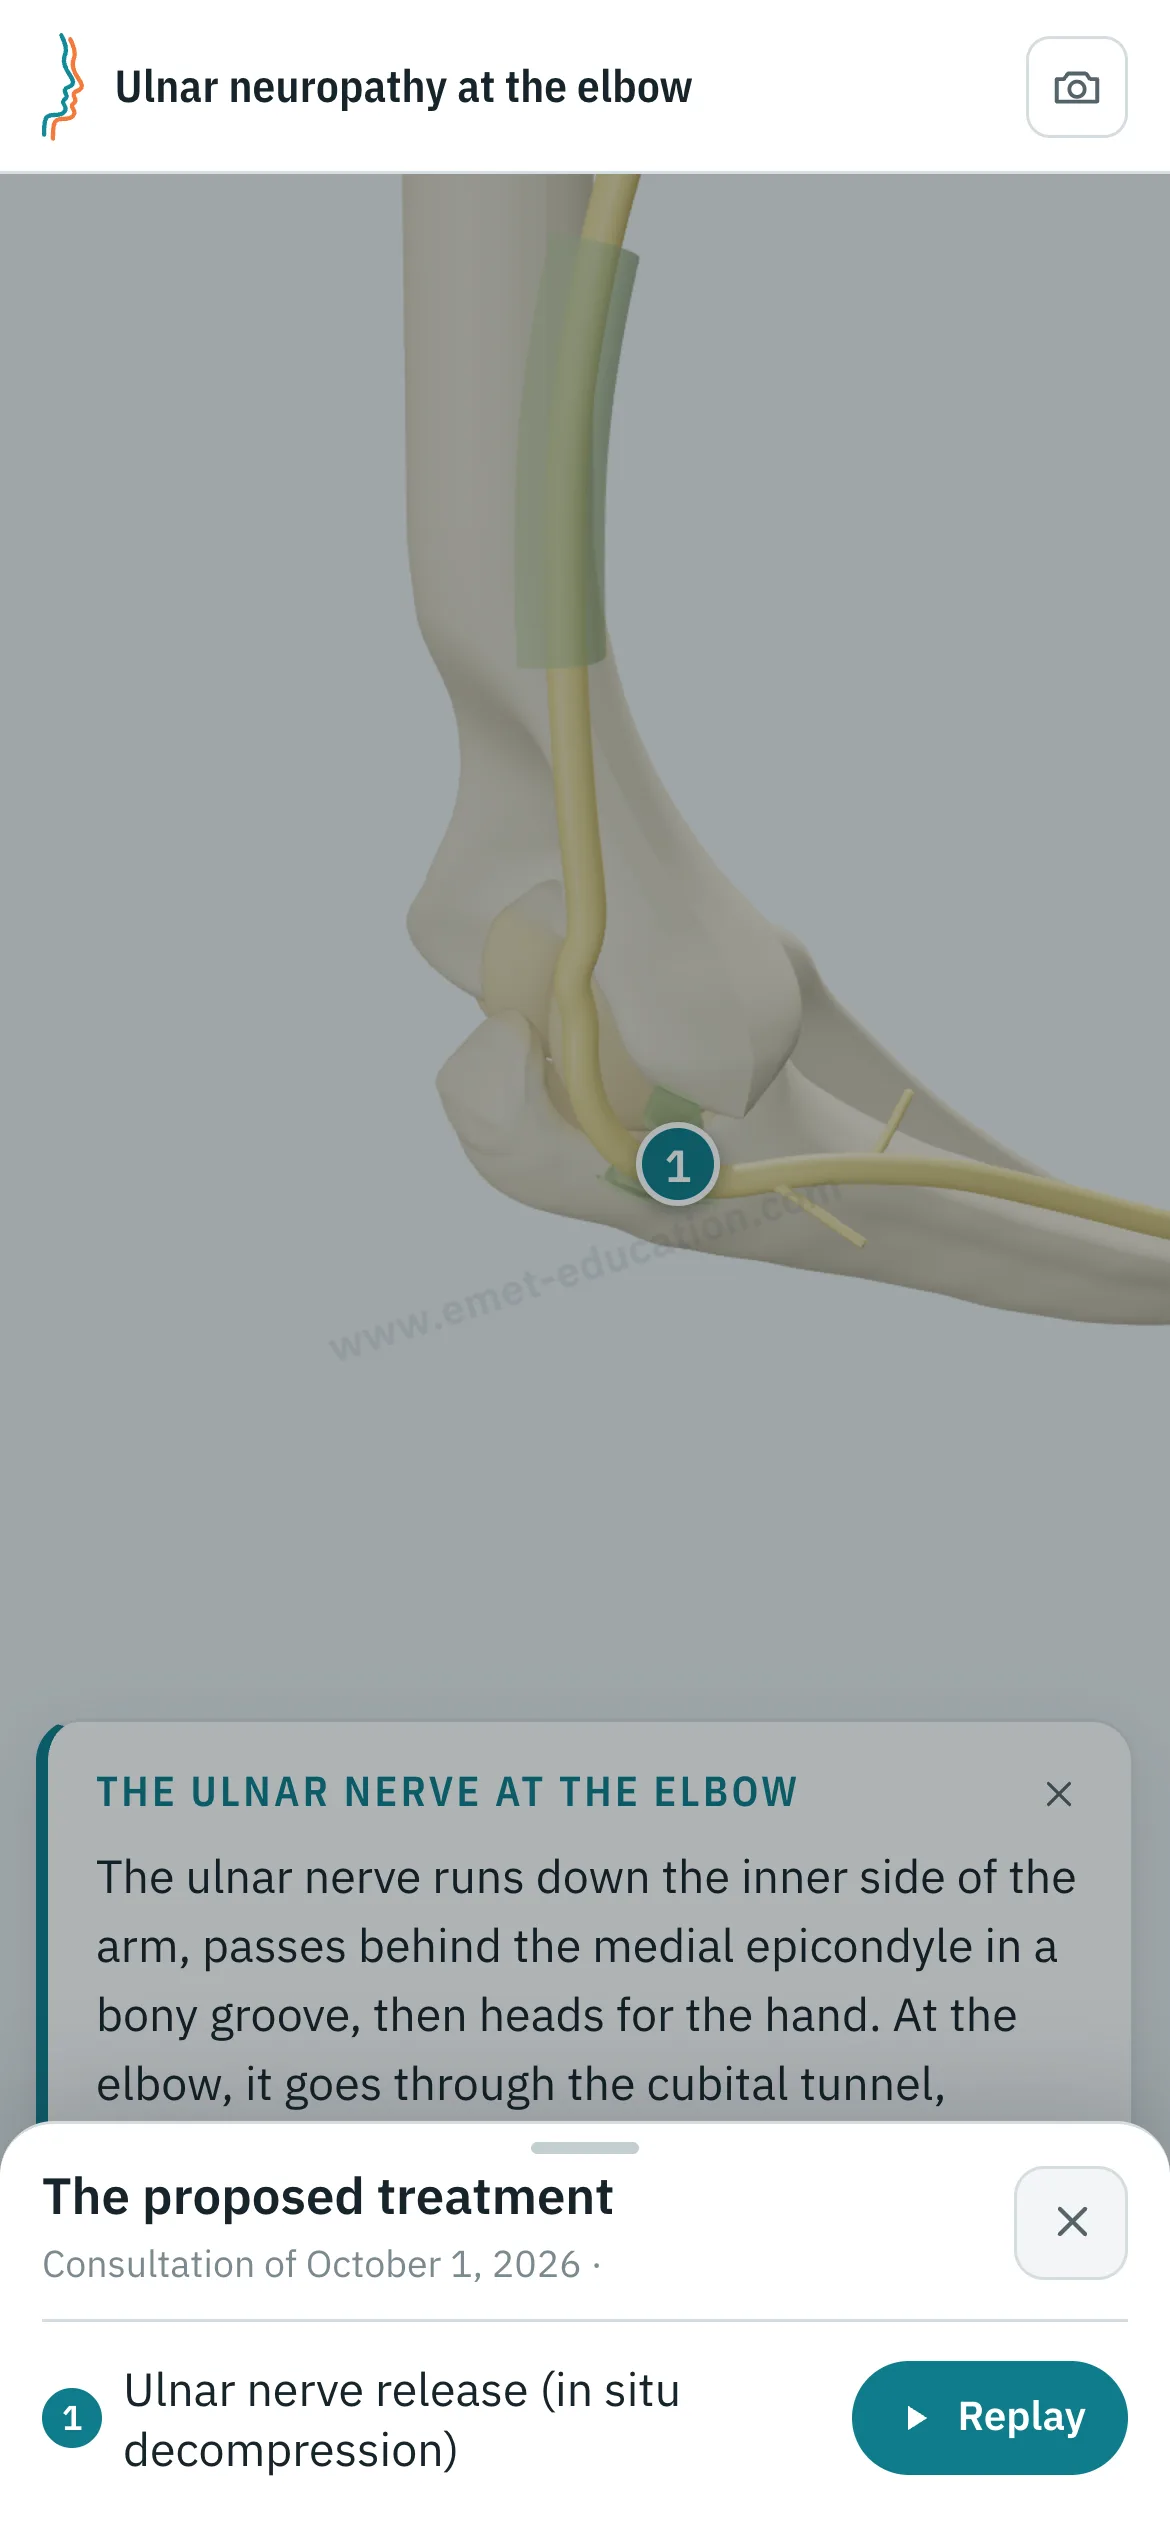
Patient view on a phone: the elbow after ulnar nerve release, and the “The proposed treatment” panel open, with the “Replay” button.
What the patient sees after scanning the QR code

Every structure explains itself on tap

Tap the nerve, the ligament, the arcade or an instrument: its name and an explanation appear.

  • One explanation per structure: bones, nerve, Osborne's ligament, arcade of Struthers, lesions, instruments.
  • Written for the patient, in their language.
  • They can reread it on their own, on the tablet or at home.
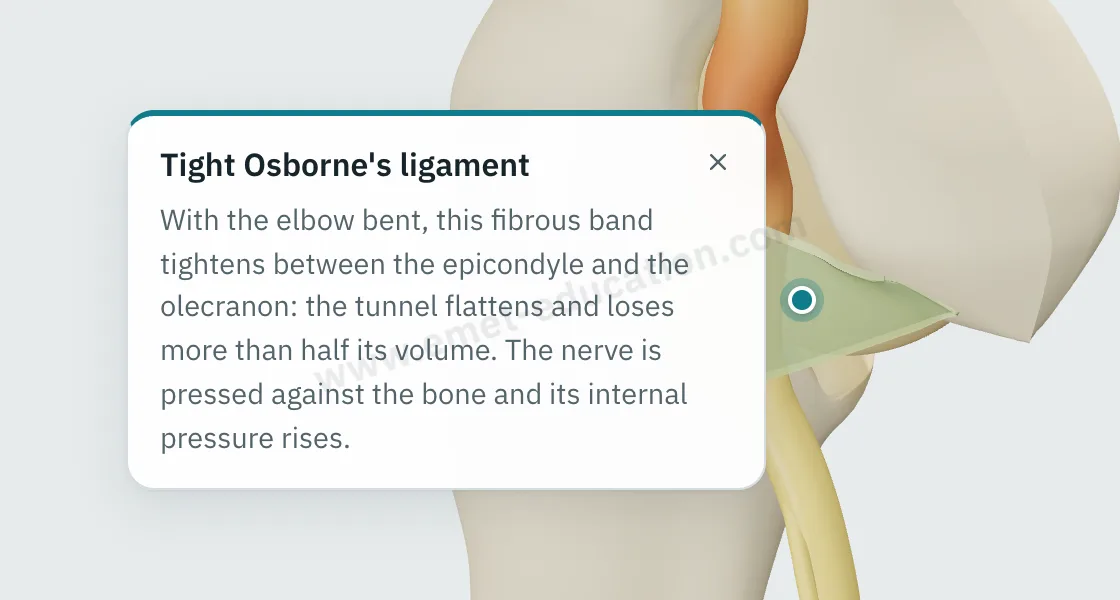
Explanation bubble “Tight Osborne's ligament” shown after tapping the ligament, over the compressed nerve.
“What is this?” on tap

They can replay the treatment step by step

From “The proposed treatment,” the patient replays the procedure: each step plays at their own pace, with its explanation, as often as they like.

Patient view on a phone: the ulnar nerve release replayed step by step.
“Replay”: the procedure, step by step

Try it with your next case: the model opens in your browser, nothing to install.

Customize the lesions

Patient information

Quality information, documented

Only 12% of U.S. adults have proficient health literacy (National Assessment of Adult Literacy). A patient who sees their own lesion and the proposed procedure understands them, gives truly informed consent, and approaches treatment with confidence.

For the patient

They see their own lesions, reproduced from their imaging, and how the proposed treatment unfolds. They leave with the same material and can review it at home, with their family, as often as they like, before giving consent.

For the physician

Each visit created with an account keeps a record of the information provided: what was shown, when, and whether the patient reviewed it. The model image, with the anatomical findings, the proposed treatment and the QR code, downloads for the patient's chart and prints. Informed consent, as the Joint Commission puts it, is more than getting a signature.

  • Saved and datedThe exact state of the model: injuries shown, treatment proposed.
  • Identical, archivableThe patient receives what you showed; the image goes in the chart and prints.
  • TrackedEach time the patient opens the link is recorded.
  • AnonymousThe link given to the patient carries no identifying data.

“Document the informed consent conversation and the patient’s (or surrogate’s) decision in the medical record in some manner.”

AMA Code of Medical Ethics, Opinion 2.1.1, Informed Consent

The model supports the consent conversation and the written consent form; it does not replace them. Data and privacy: legal information (in French).

Questions

Questions from colleagues

Is the model free?

Partly: the model and most of the lesions are free. Treatments (neurolysis, anterior transposition, injection) and other features are paid options.

Do I need an account?

Not to open the model, set the lesions and walk through the treatment. After about fifteen adjustments, you will be asked to create a free account: it saves your visits, picks them up from one time to the next, and records when the patient opens the link.

What equipment do I need?

Just a web browser, nothing to install: computer, tablet or TV screen in the exam room; the patient opens it on their phone. One click saves an image, without the interface, for the chart.

What happens to patient data?

No patient names are stored. The link given to the patient carries only the state of the model: lesions, treatment, language and visit date. A name written on the image you hand out stays on that image.

Is it a medical device?

No: it is an educational tool. It does not diagnose, does not plan surgery, and does not replace the consent conversation or the written consent form. Among software functions that are not medical devices, the FDA lists those intended for general patient education and interactive anatomy diagrams used for training.

How long does it take in clinic?

Three adjustments and one procedure played: a few minutes, during the visit. The patient reviews it at home, as often as they like.

Can the elbow be moved?

Yes: from −5° to 145° of flexion, with the slider or back and forth. The nerve follows the motion, and two measurements read on the model, Osborne's ligament tension and nerve flattening, show what flexion does to it.

What if I don't operate?

The model is first a way to explain the mechanism and the lesion: flexion, compression and instability can be shown without walking through surgery. Injection is included too, alongside the surgical procedures.

Can I embed it on my website?

It is planned for upcoming plans: the model displayed on a practice or hospital website, credited to EMET Education.

Which languages?

English, Spanish, French and Russian. The patient receives the model in the language chosen during the visit, which helps with the roughly 28 million people in the U.S. with limited English proficiency, alongside a qualified interpreter, not instead of one.

Design

Who designed this model

Model designed by Dr. Mikaël Chelli, orthopedic surgeon, based on the reference classifications and measurements. Updated October 1, 2026.

  • McGowan A.J. The results of transposition of the ulnar nerve for traumatic ulnar neuritis. J Bone Joint Surg Br, 1950.
  • Osborne G.V. The surgical treatment of tardy ulnar neuritis. J Bone Joint Surg Br, 1957.
  • Childress H.M. Recurrent ulnar-nerve dislocation at the elbow. J Bone Joint Surg Am, 1956.
  • Apfelberg D.B., Larson S.J. Dynamic anatomy of the ulnar nerve at the elbow. Plast Reconstr Surg, 1973.
  • Pechan J., Julis I. The pressure measurement in the ulnar nerve. J Biomech, 1975.
  • Gelberman R.H. et al. Changes in interstitial pressure and cross-sectional area of the cubital tunnel and of the ulnar nerve with flexion of the elbow. J Bone Joint Surg Am, 1998.

Try it with your next patient

The model opens in your browser, nothing to install, no sign-up.

Know a colleague who could use it? Email this page ·