EMET Electronic Medical Twin
  1. EMET Education
  2. Musculoskeletal
  3. Shoulder
  4. Proximal humerus fracture

3D model · Shoulder

Proximal Humerus Fracture 3D Model

Reproduce your patient's fracture during the visit, part by part, and show in 3D the treatment you recommend. They leave with their model on their phone.

Designed by an orthopedic surgeon

Opens in your browser, no sign-up. For orthopedic surgeons, emergency physicians, sports medicine physicians, physiatrists and primary care physicians.

How it works

In the visit, in three steps

Structured information in a few minutes, which the patient can review at home.

  1. 1

    Show

    Open the model and walk through the anatomy: humeral head, greater and lesser tuberosities, anatomic and surgical necks, glenoid, acromion and coracoid.

  2. 2

    Reproduce

    Set the fracture from the radiographs and CT: Neer type, displacement of each part, dislocation. Then walk through the proposed treatment, nonoperative or surgical, step by step.

  3. 3

    Share

    Give the patient the QR code or an image: they find their own case, in their language.

Features

Explain in detail during the visit

Every setting updates the model live: you reproduce the fracture from your patient's imaging in front of them, then walk through the treatment you recommend.

The fracture, described in a few clicks

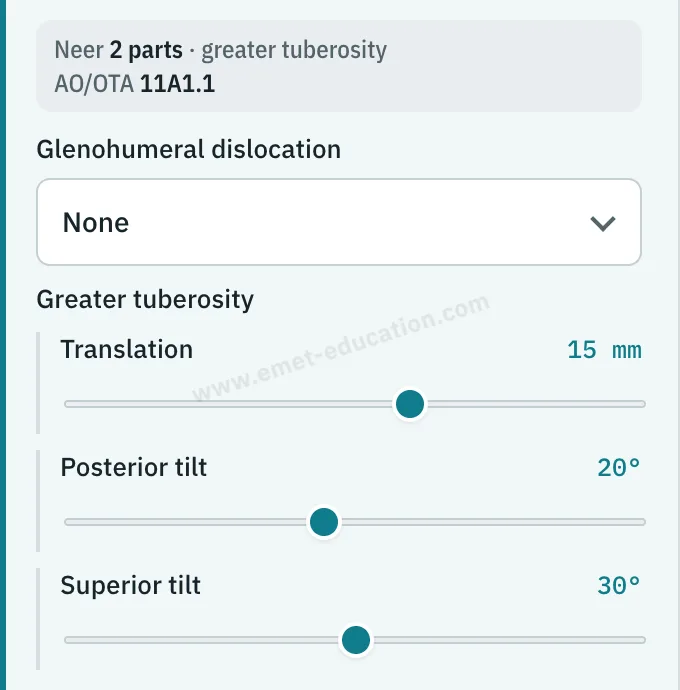
The “Pathology & lesions” panel describes the fracture: the type on a pictogram, the displacement of each part, dislocation. The Neer and AO/OTA classifications are displayed live.

Ten Neer types, with their AO/OTA code

The pictograms are grouped by number of parts: undisplaced; surgical neck, anatomic neck, greater or lesser tuberosity; 3-part; 4-part, displaced or valgus impacted per Jakob; head split. A switch moves to AO/OTA 2018 without losing the fracture.
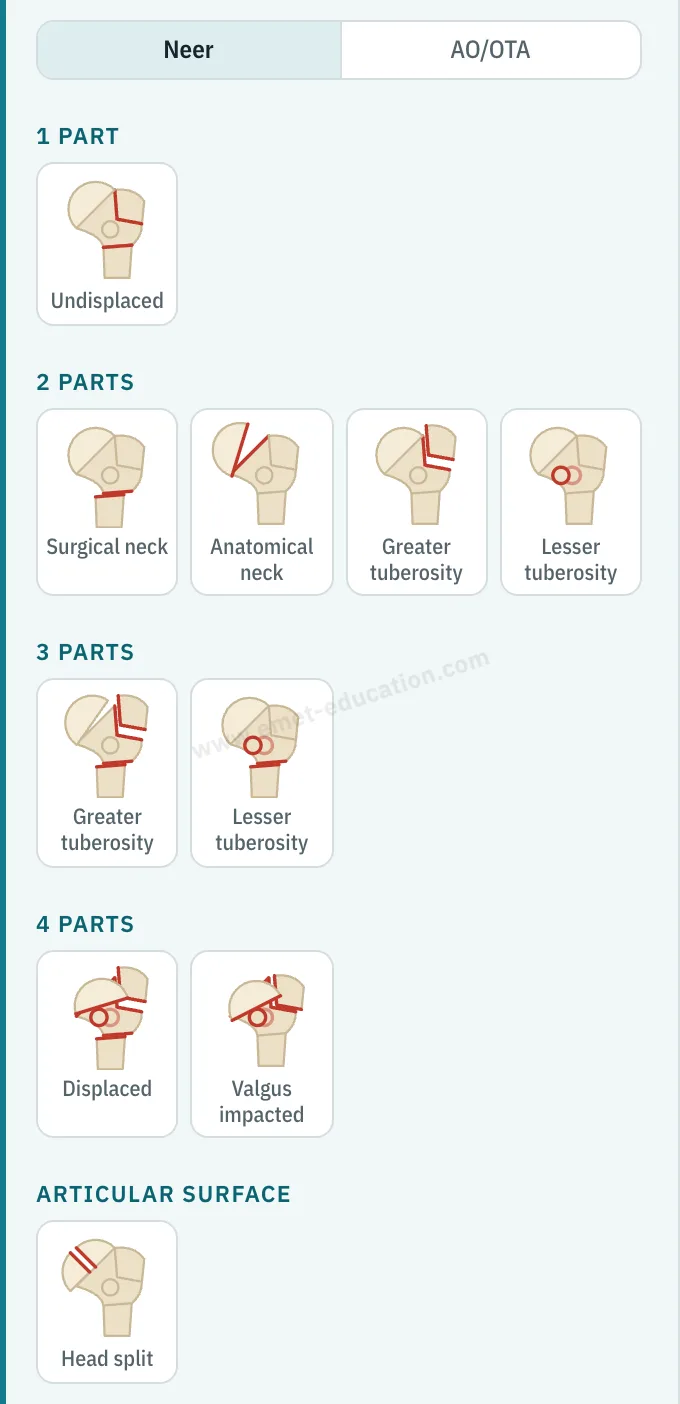
Model panel: Neer · AO/OTA switch, ten Neer pictograms grouped from 1 to 4 parts, and the articular surface.
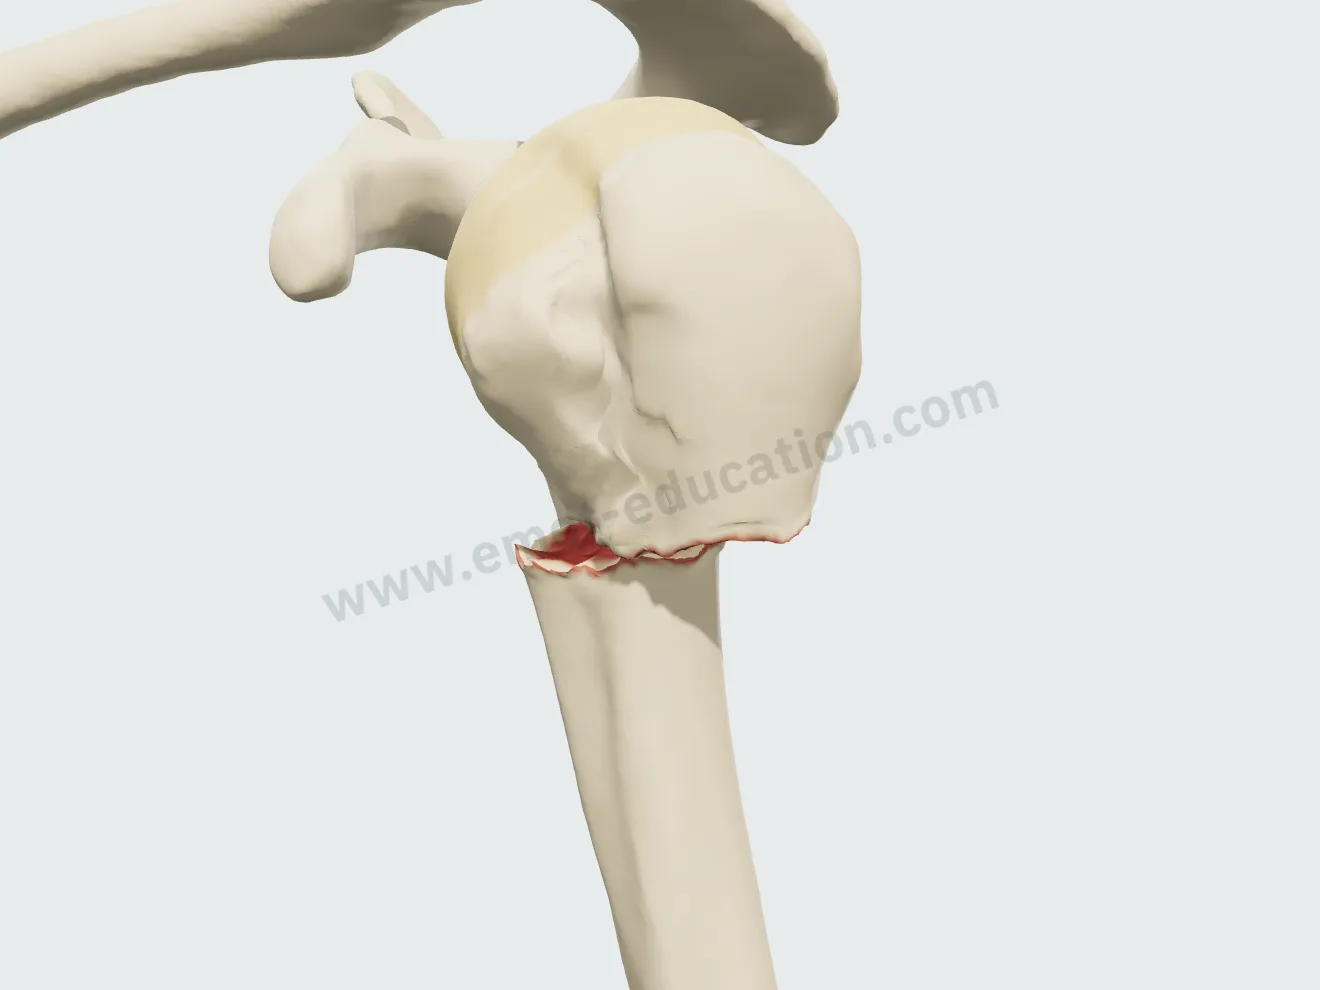
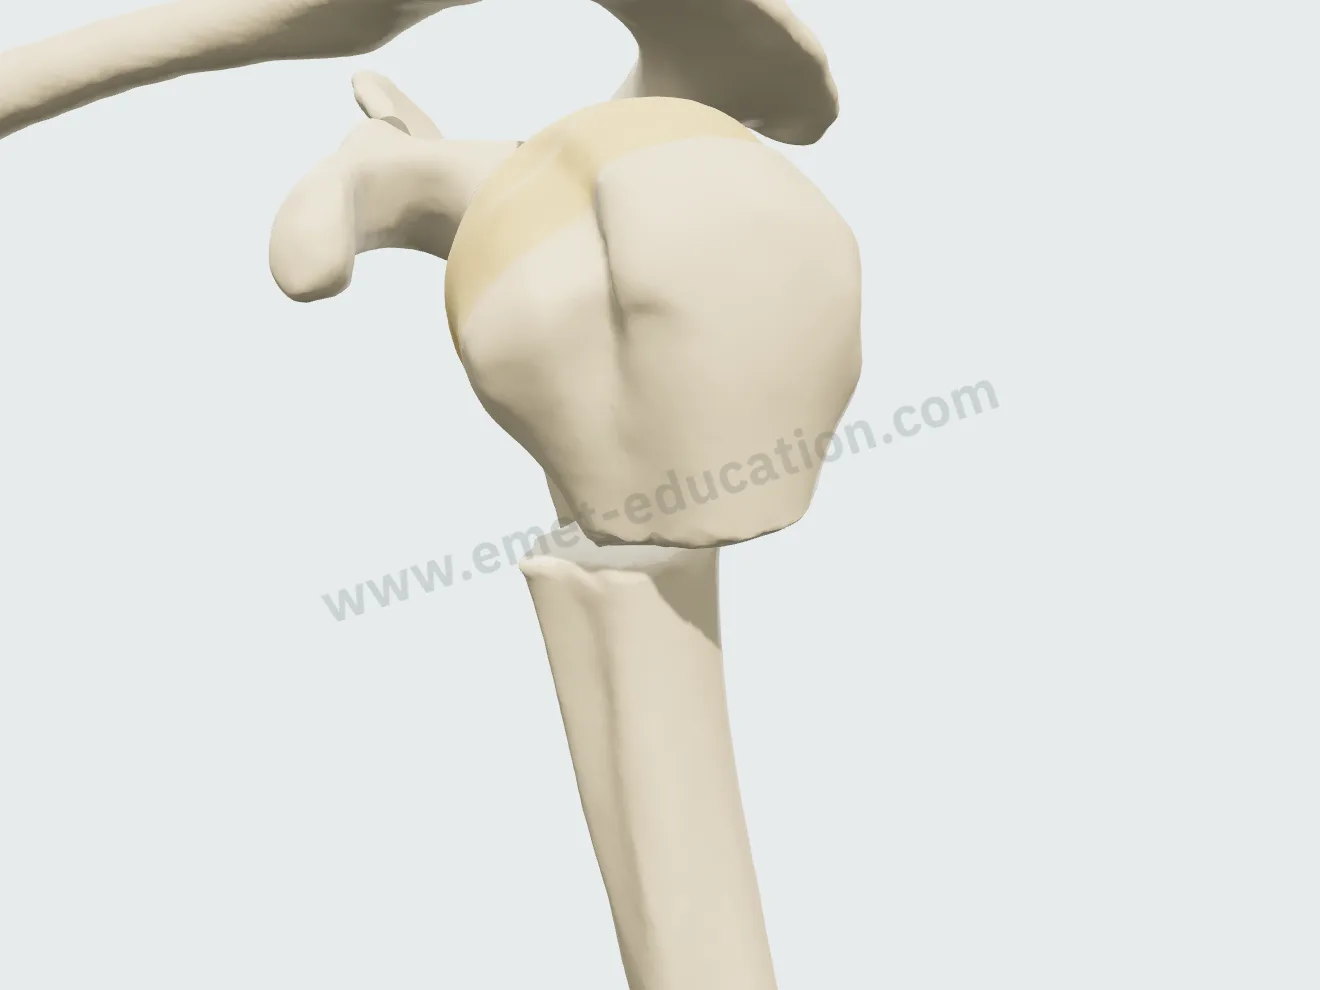
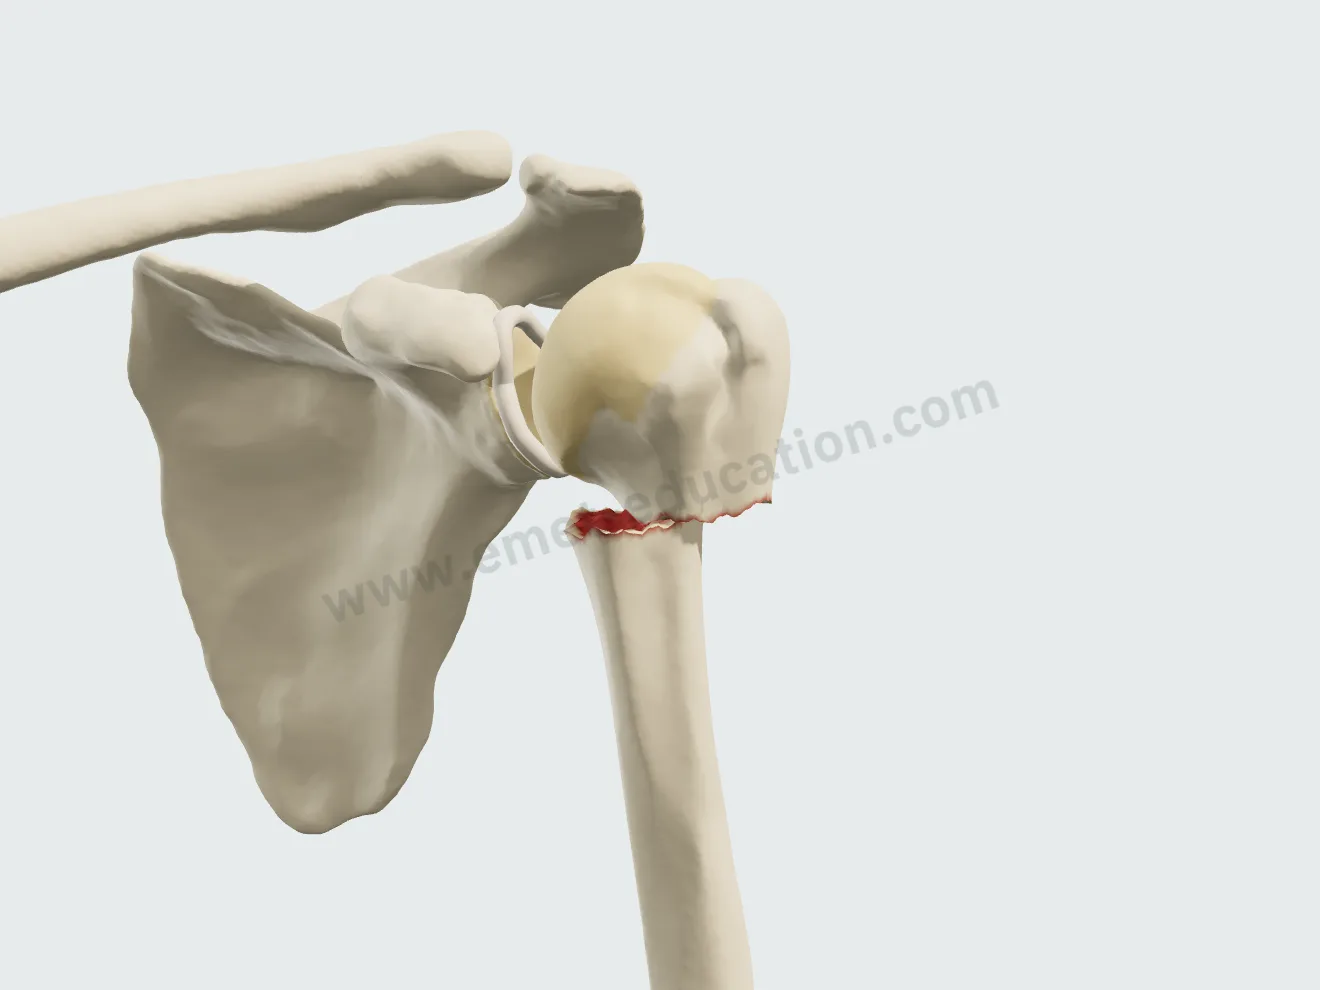
2-part surgical neck fracture of the proximal humerus: the shaft translated medially under the head.
2-part · surgical neck
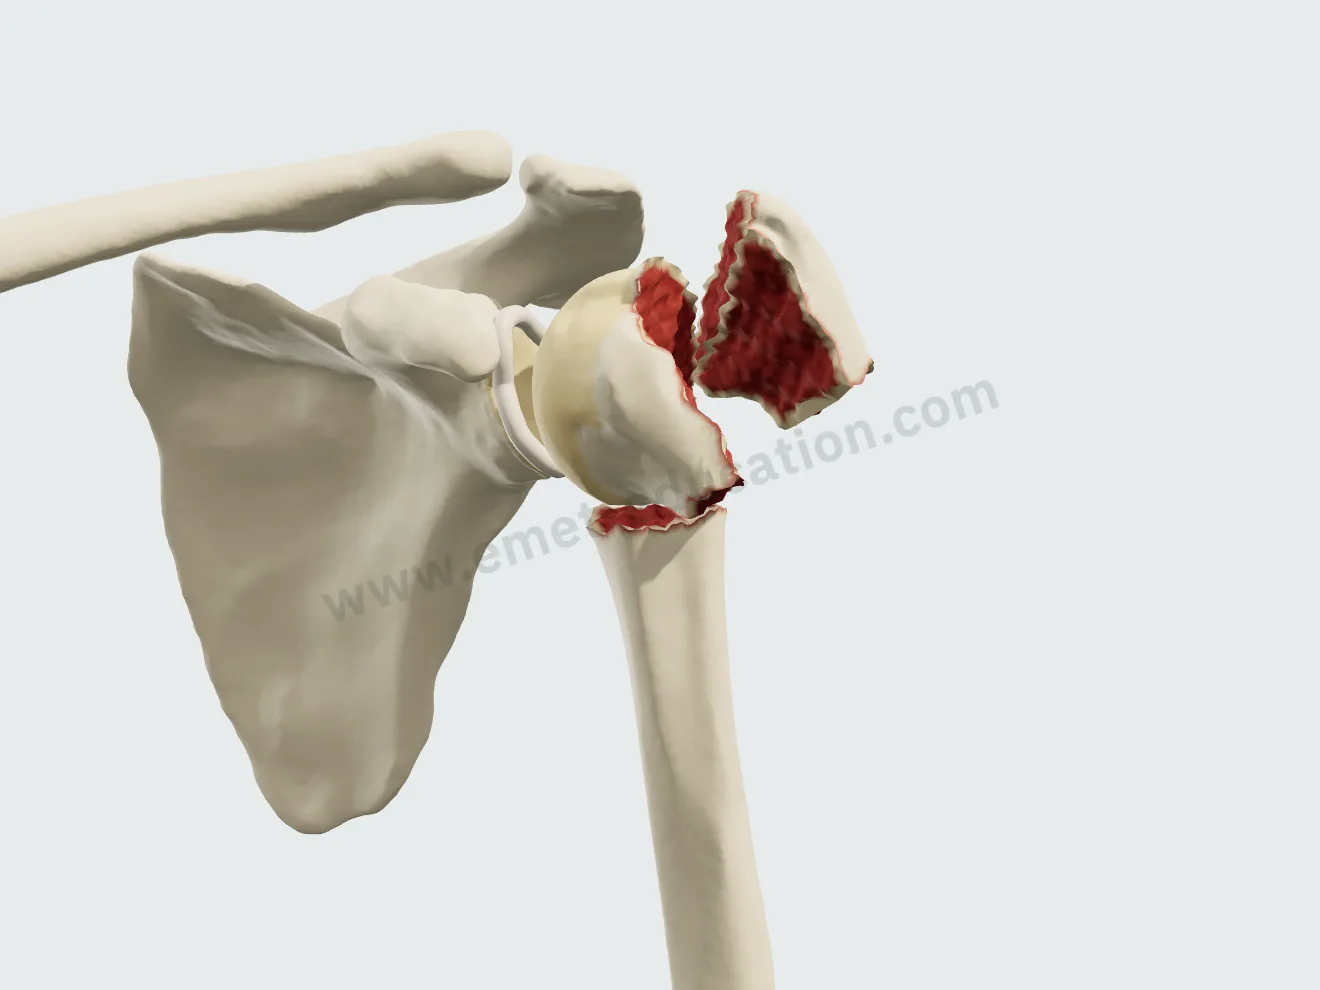
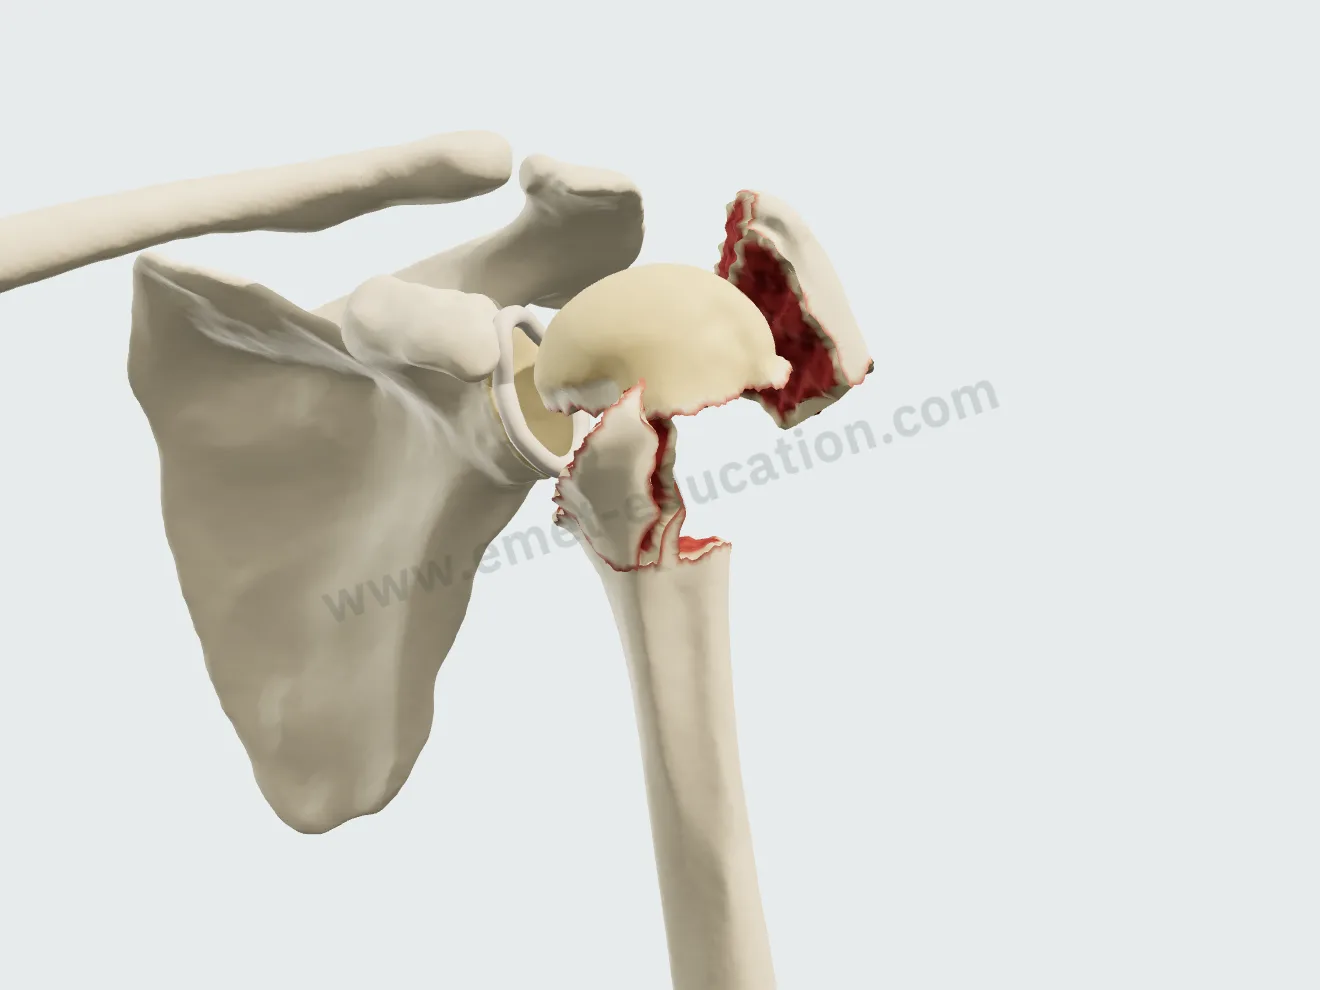
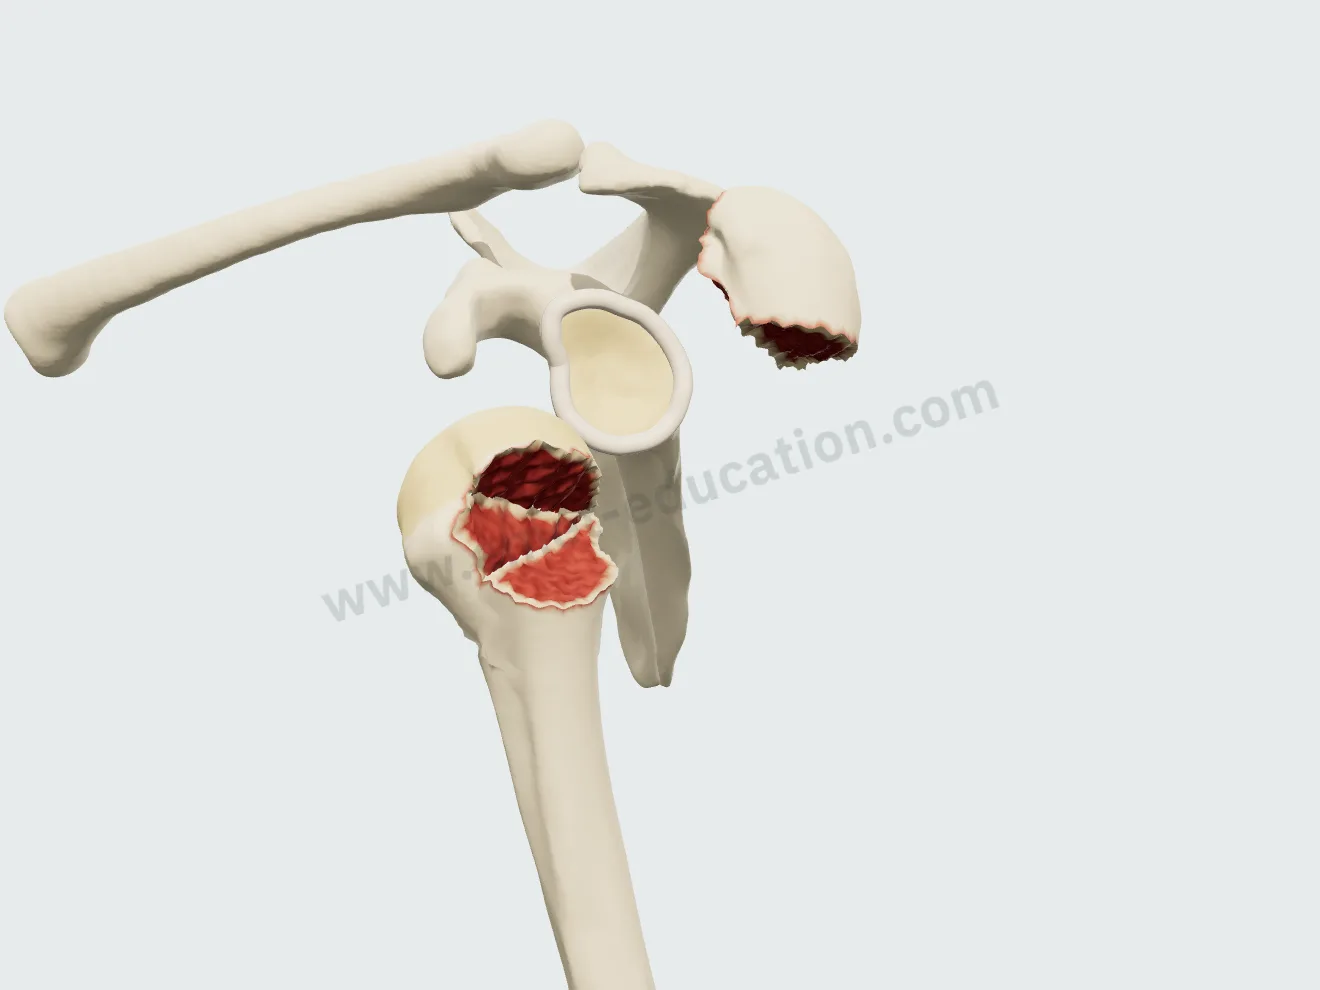
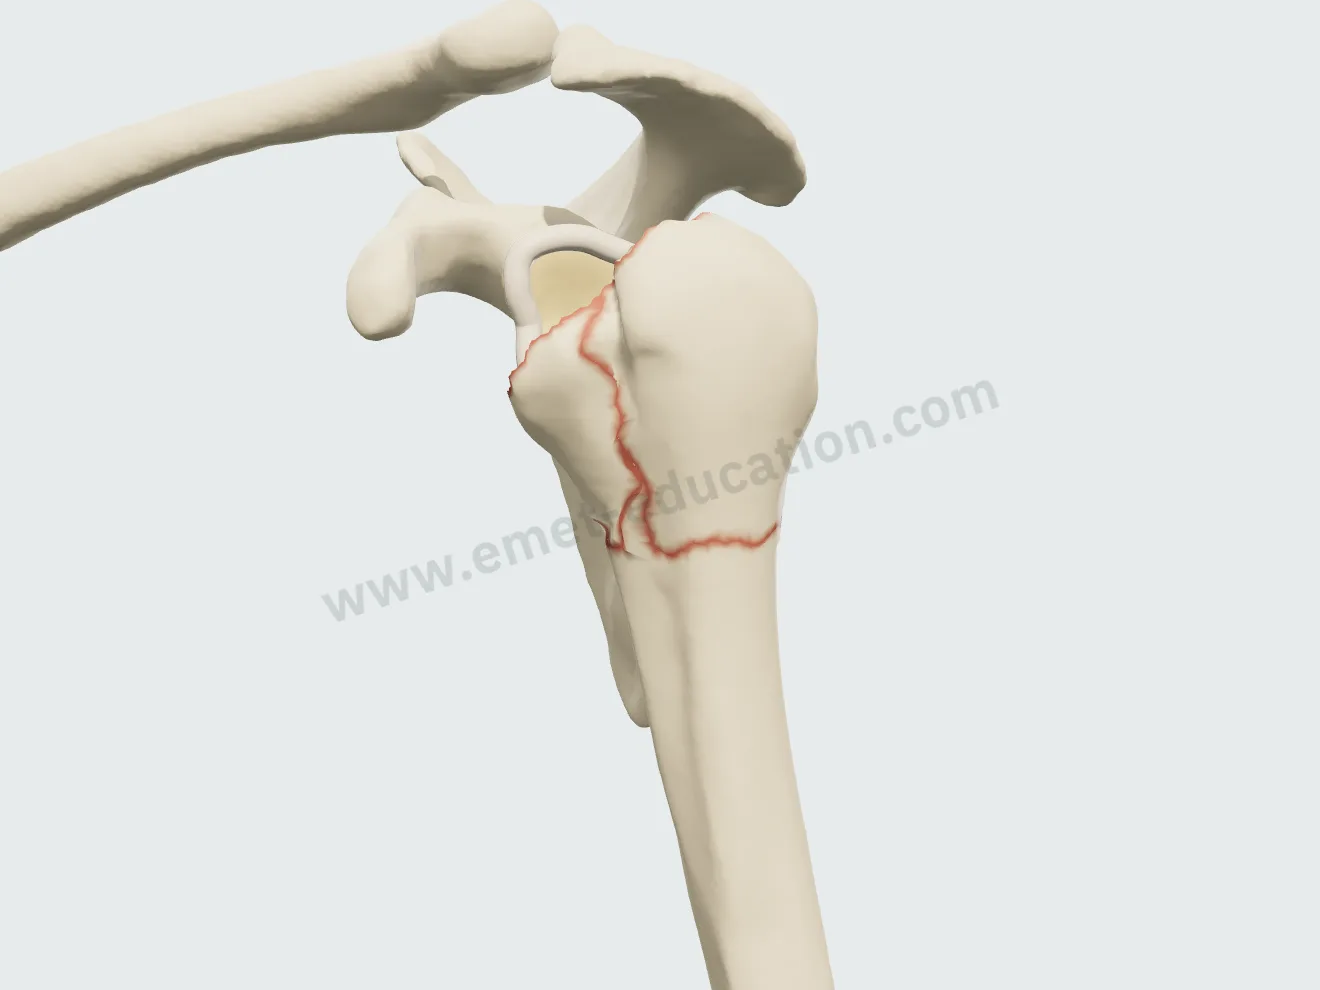
3-part fracture: surgical neck and greater tuberosity, pulled superiorly and posteriorly, head in varus.
3-part · greater tuberosity
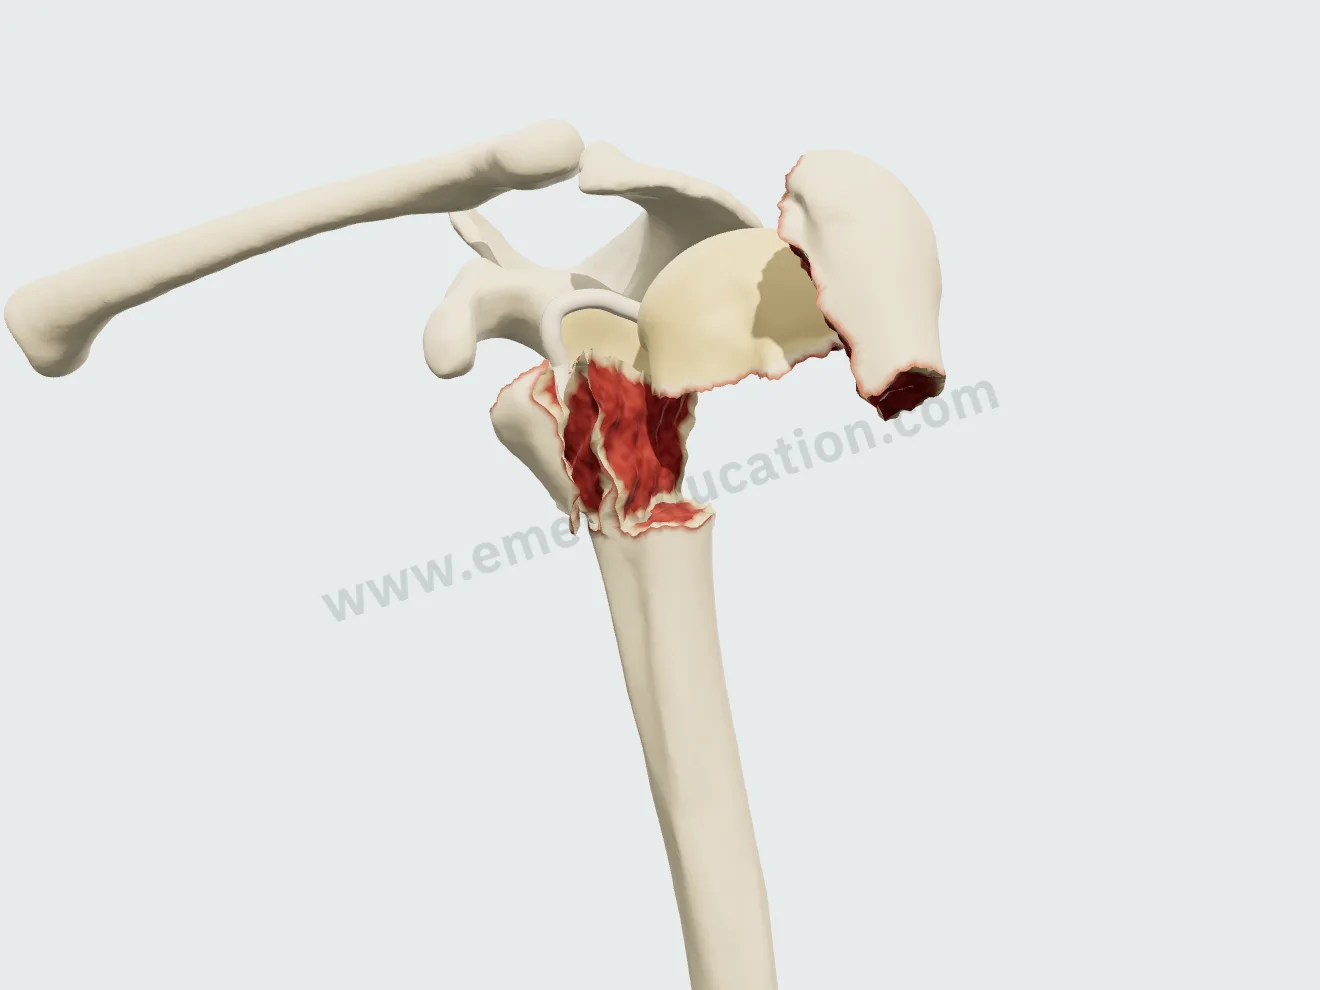
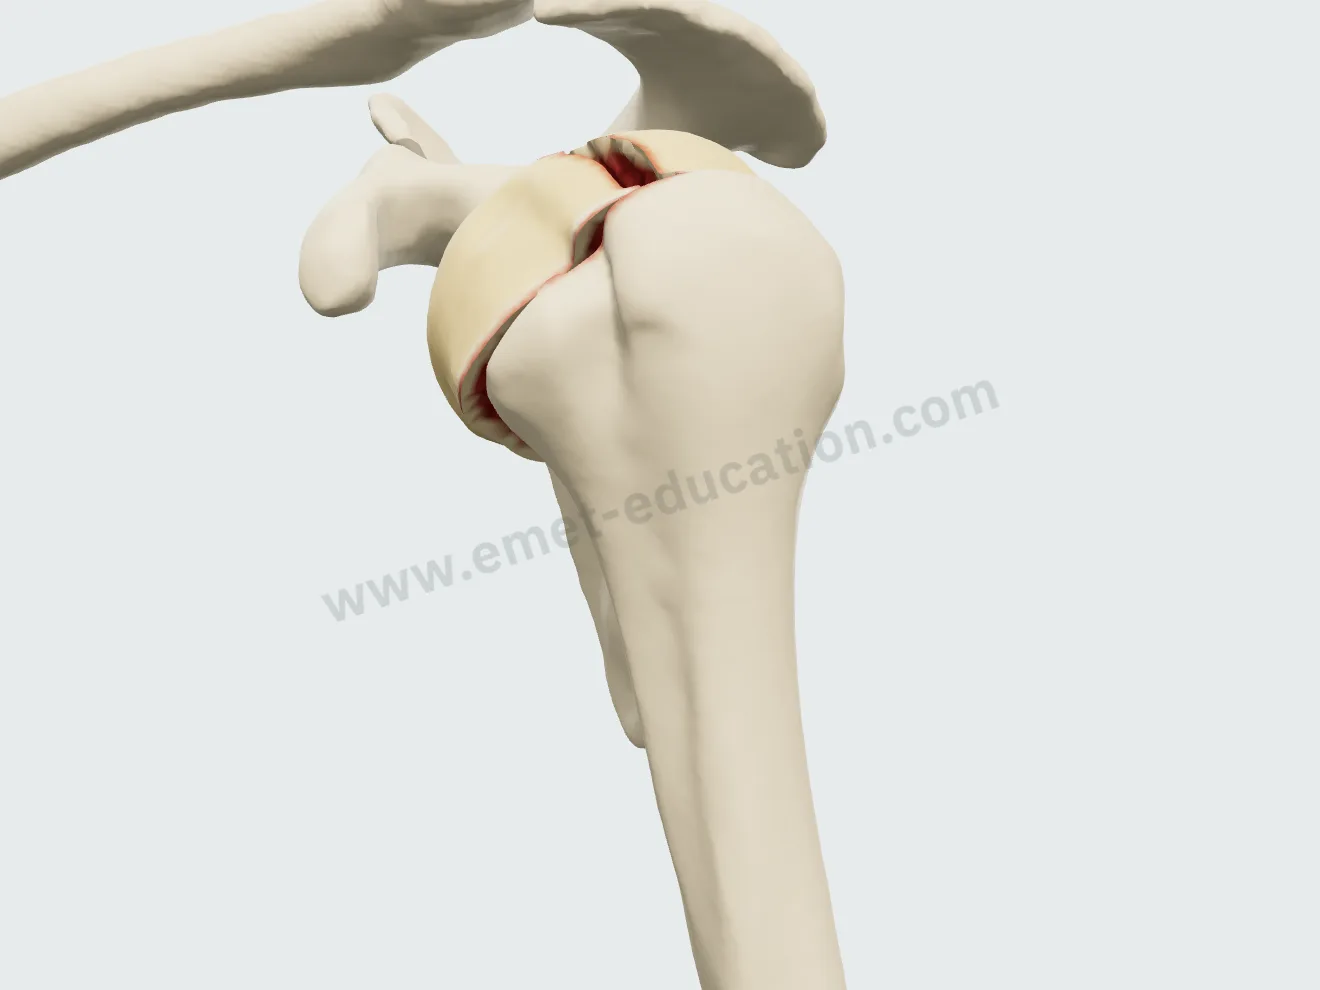
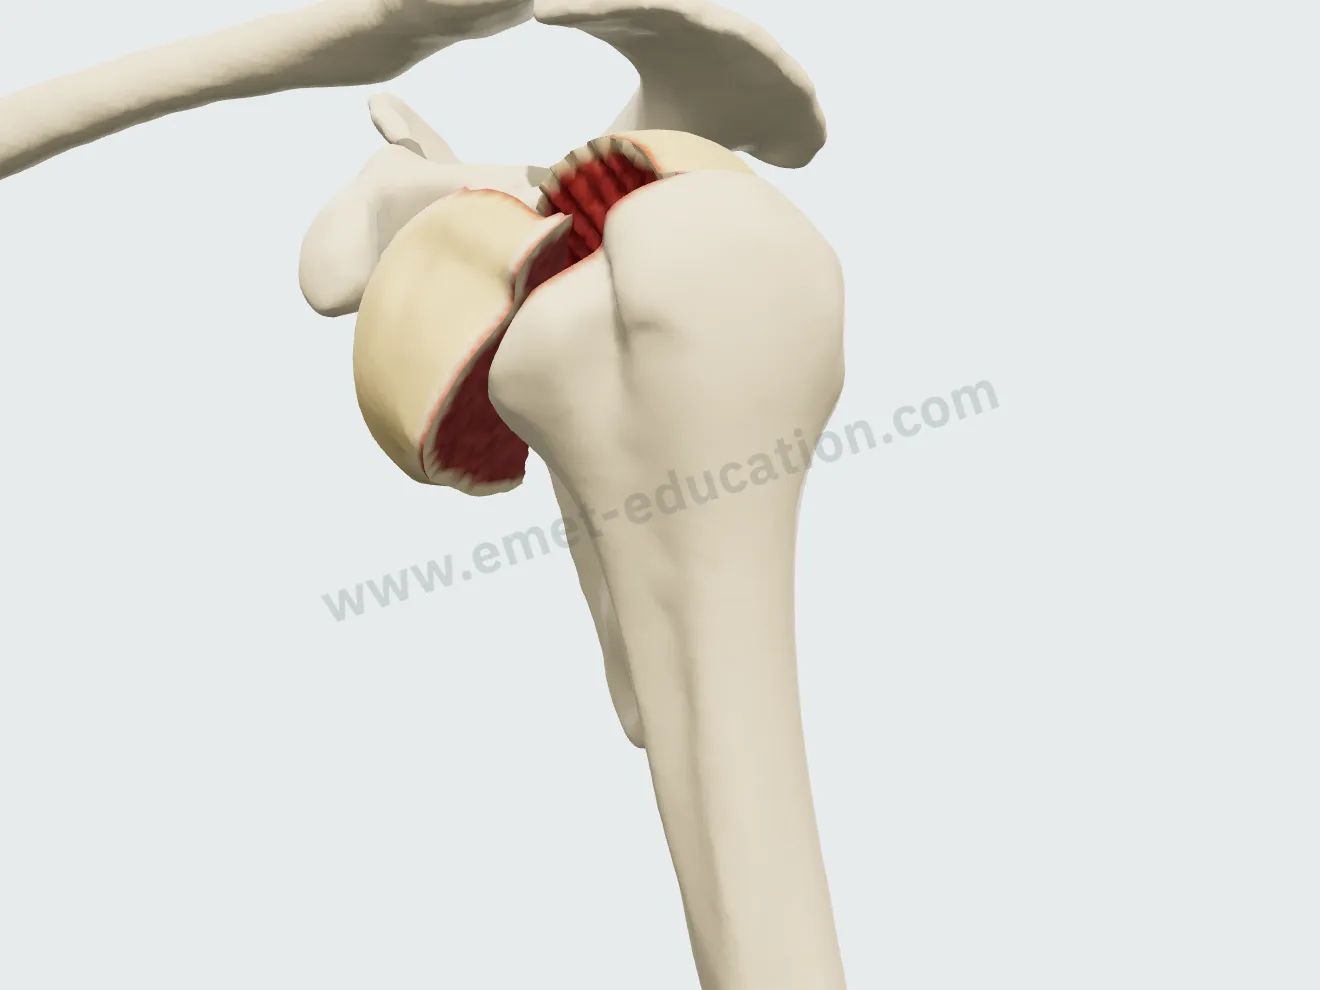
4-part fracture: head in valgus, greater and lesser tuberosities separated, shaft translated.
4-part · head in valgus

The treatment, step by step

Nonoperative treatment, nailing, plating and reverse arthroplasty, played step by step, continuously or one step at a time, then hardware removal. Each procedure builds on the fracture you set; an unusual indication is flagged (⚠), never blocked.

Nonoperative treatment

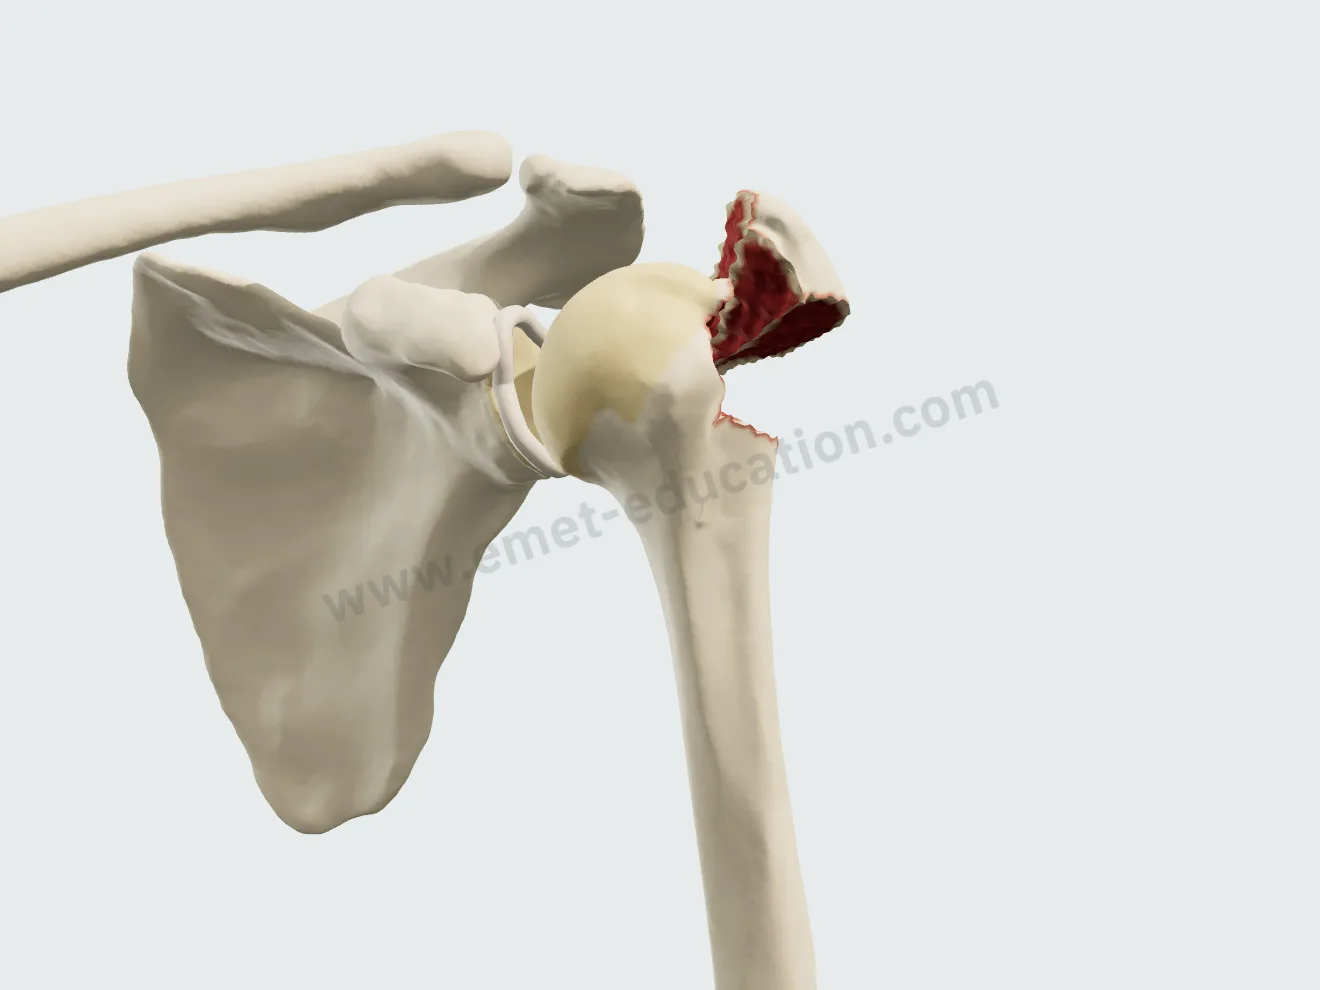
No reduction: the callus fills the gaps between the fragments and heals the fracture as displacement left it.

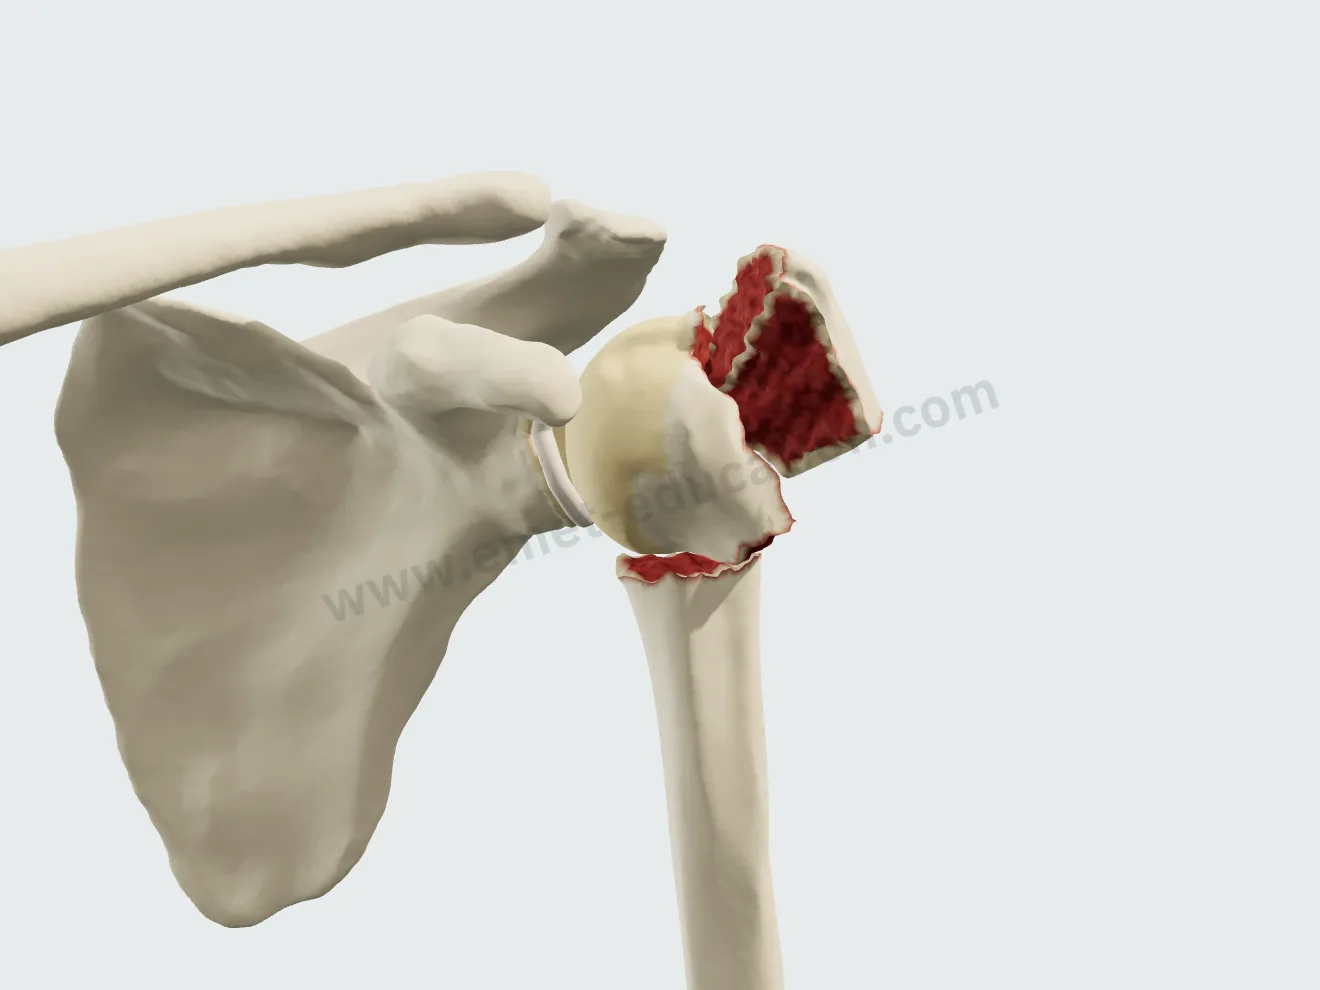
Nonoperative treatment, starting point: 3-part fracture, greater tuberosity displaced, head in varus.
1Fracture
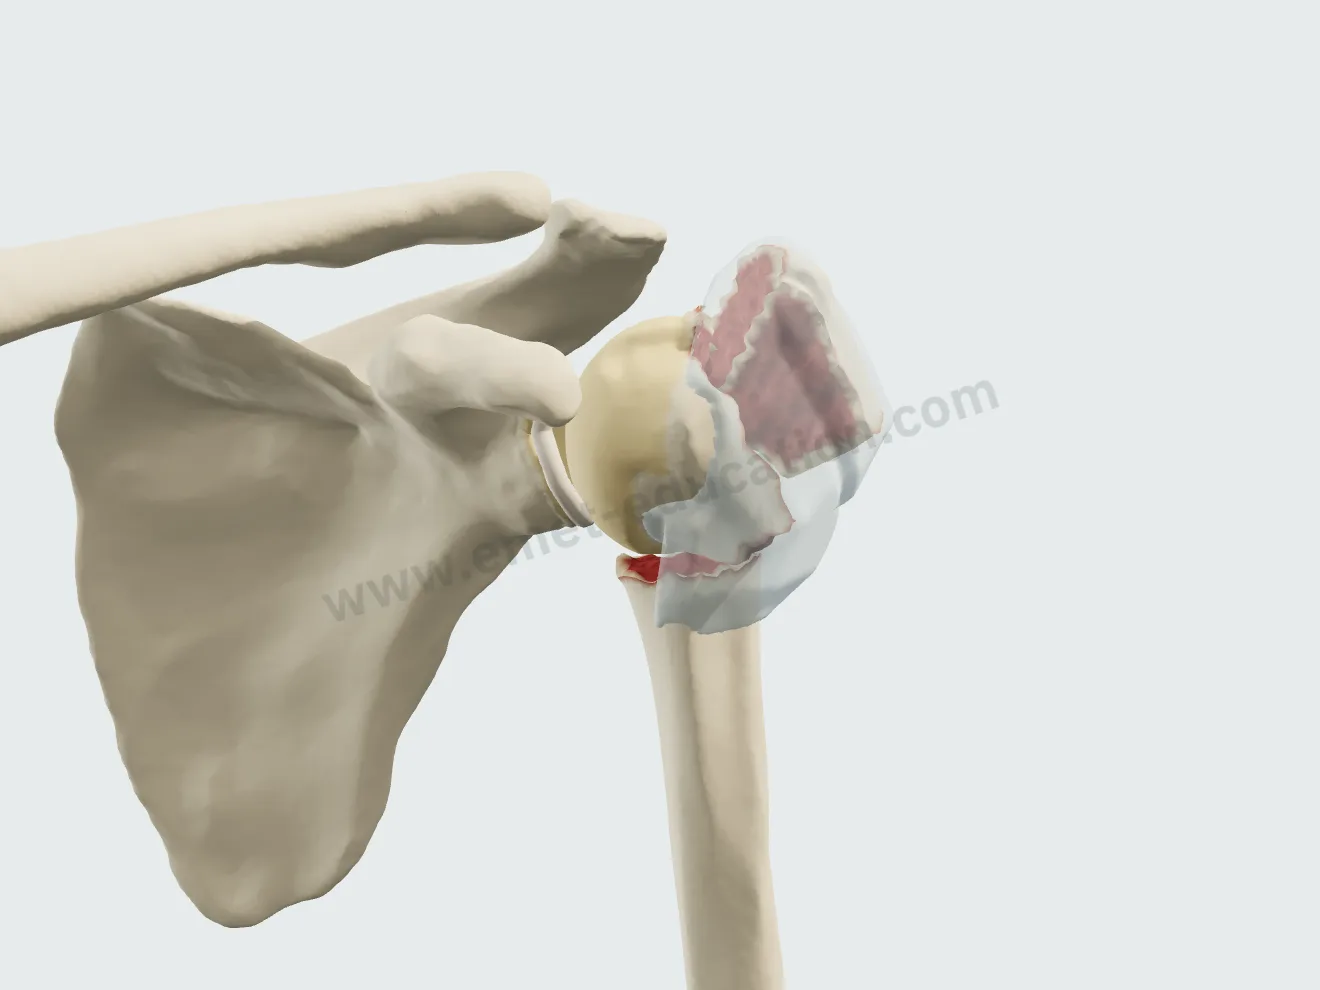
Nonoperative treatment, step 2: the soft callus, translucent tissue between the fragments.
2Soft callus
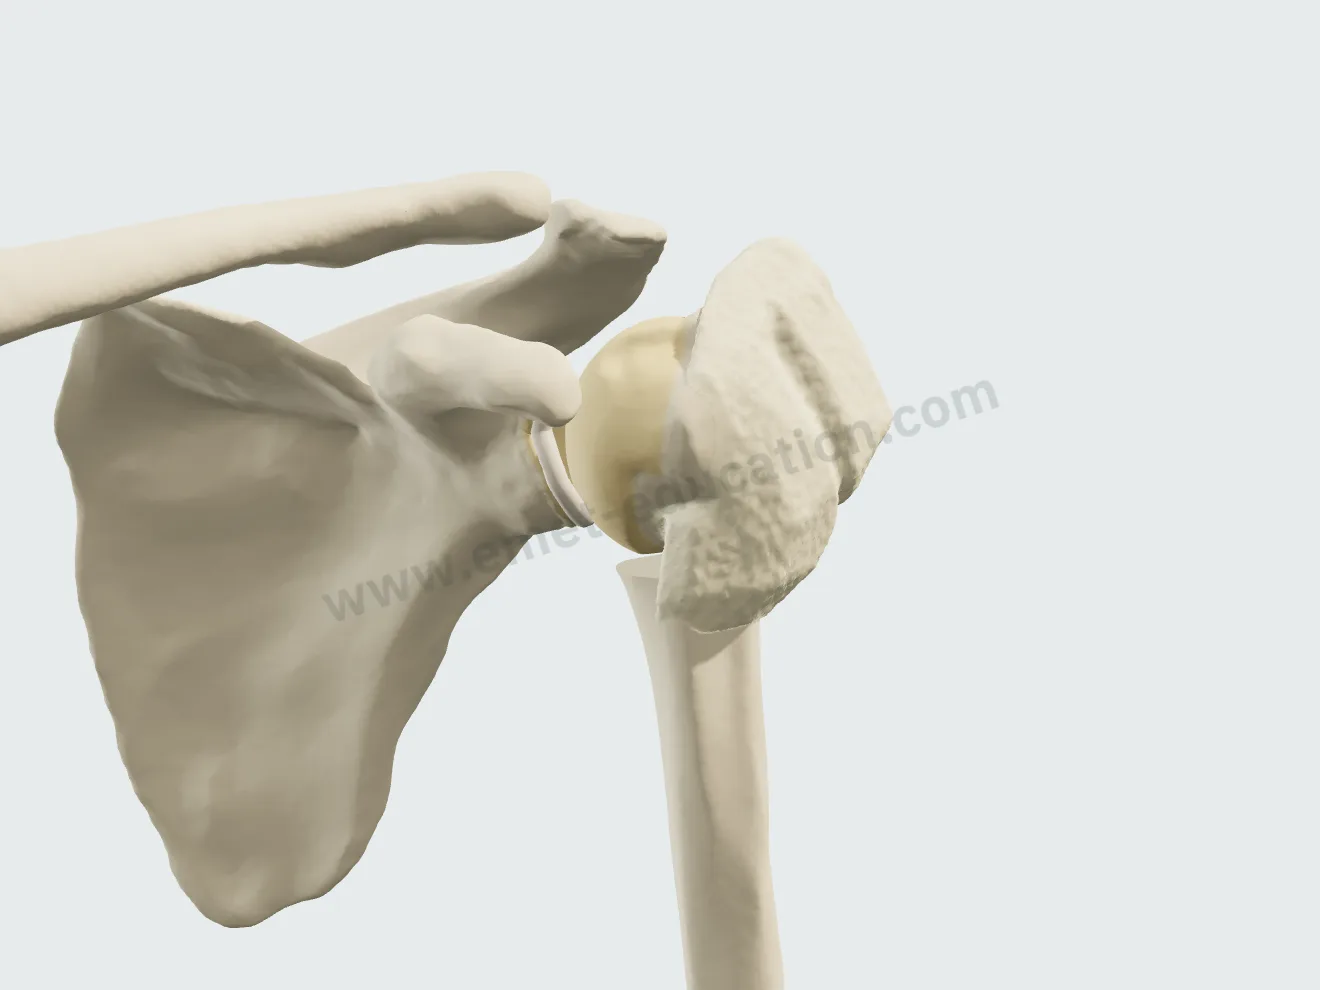
Nonoperative treatment, step 3: the hard callus, mineralized, unites the fragments.
3Hard callus
Nonoperative treatment, step 4: remodeling; the healed humerus keeps the displacement.
4Remodeling

Intramedullary nail

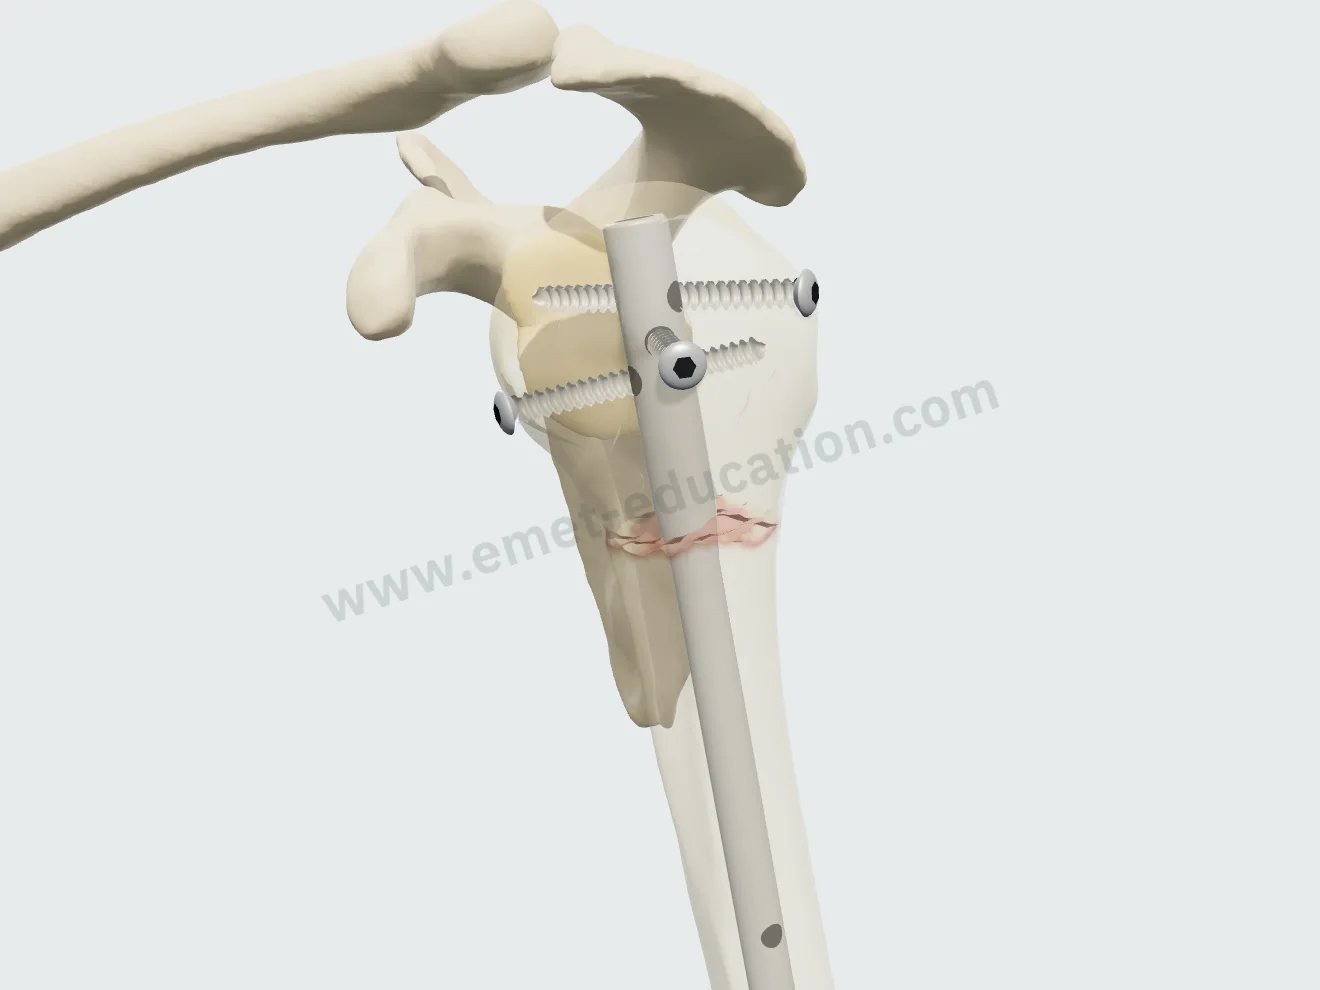
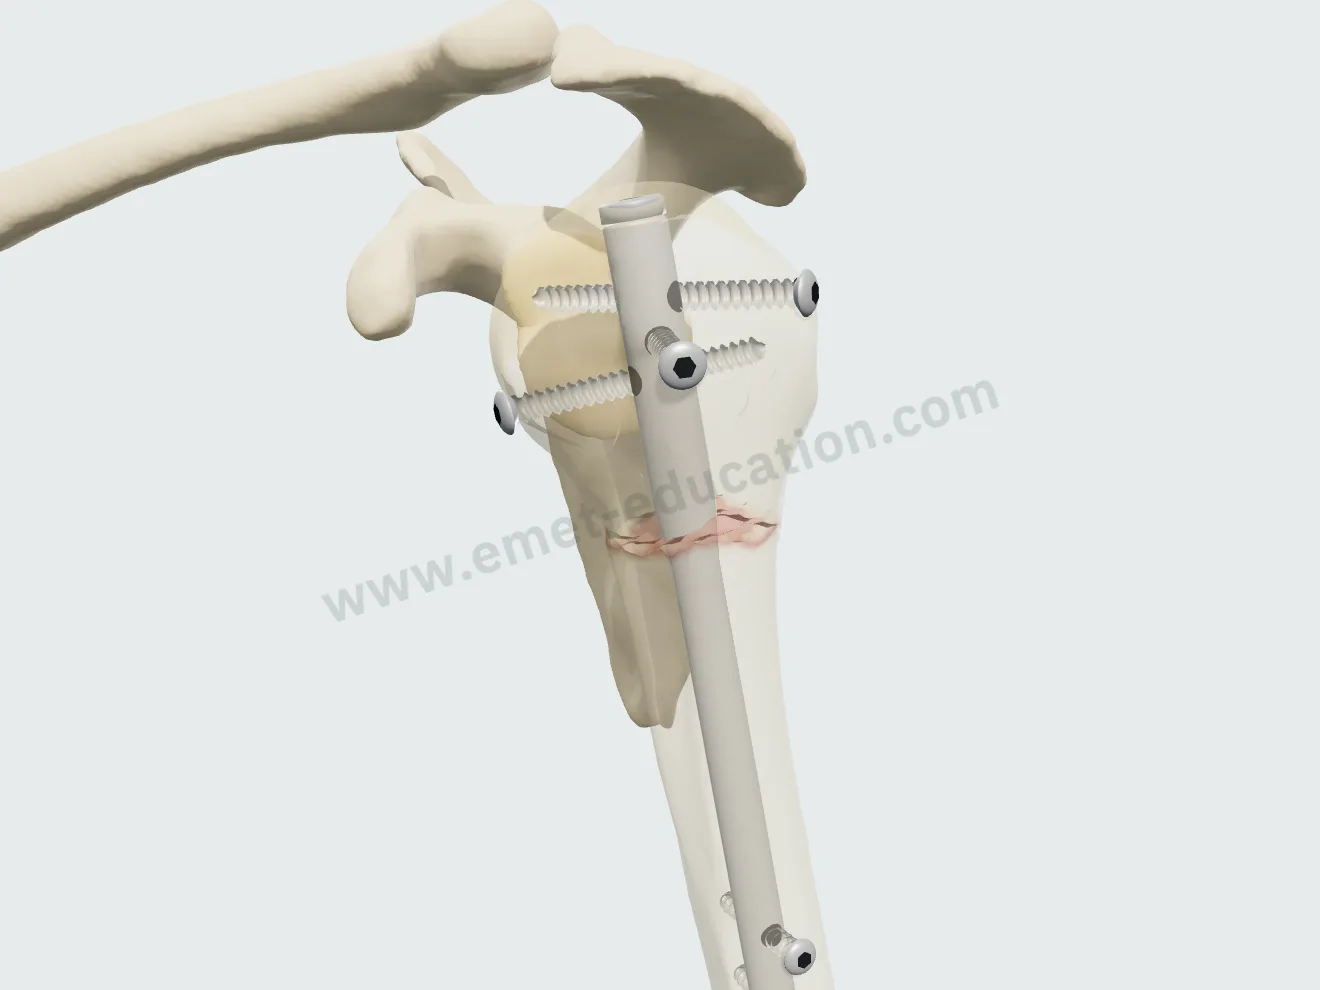
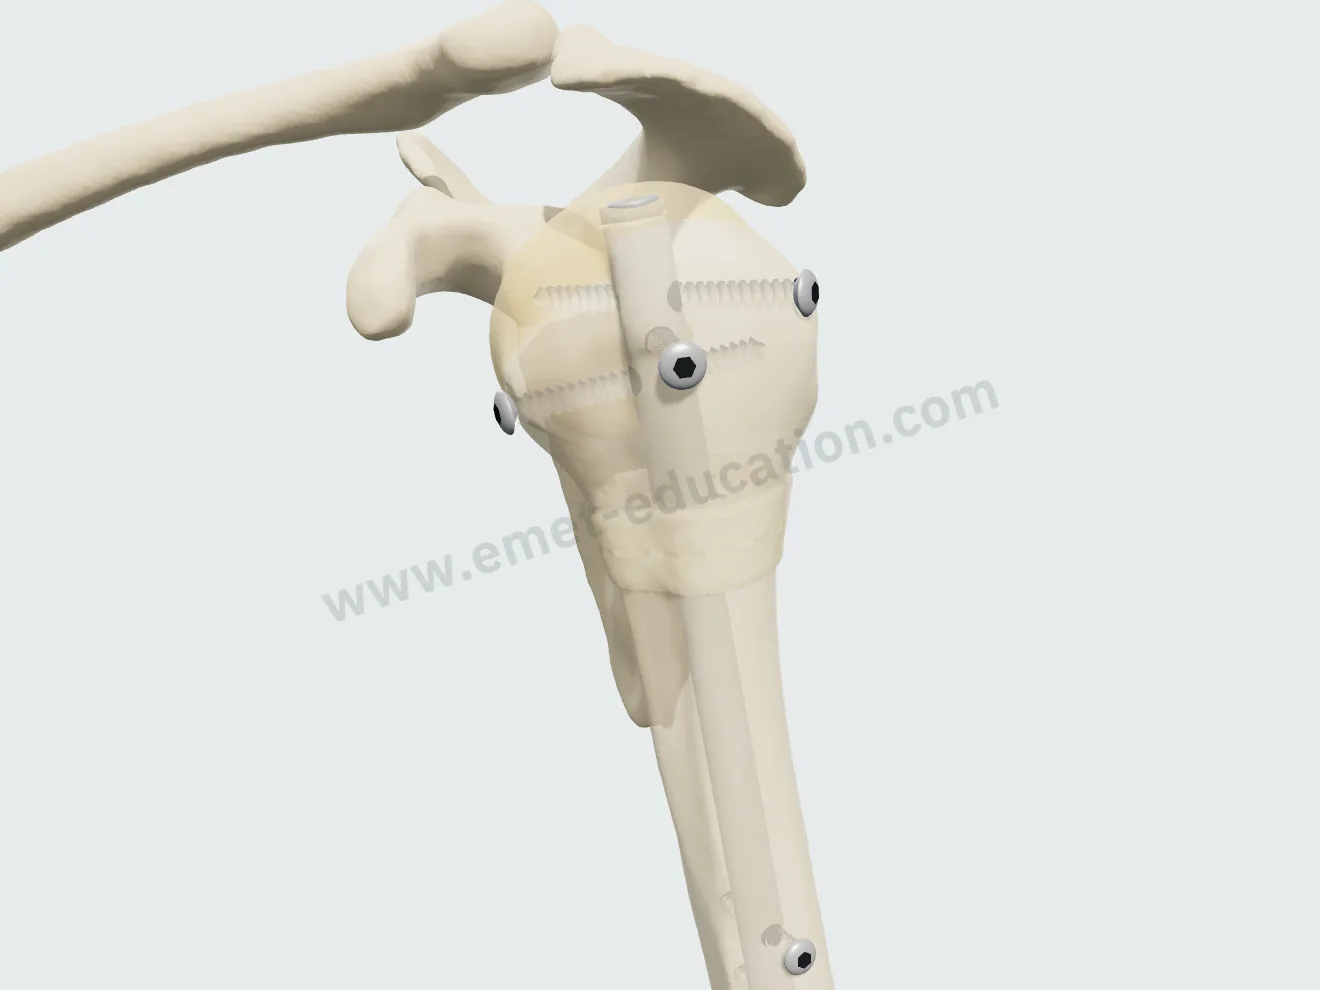
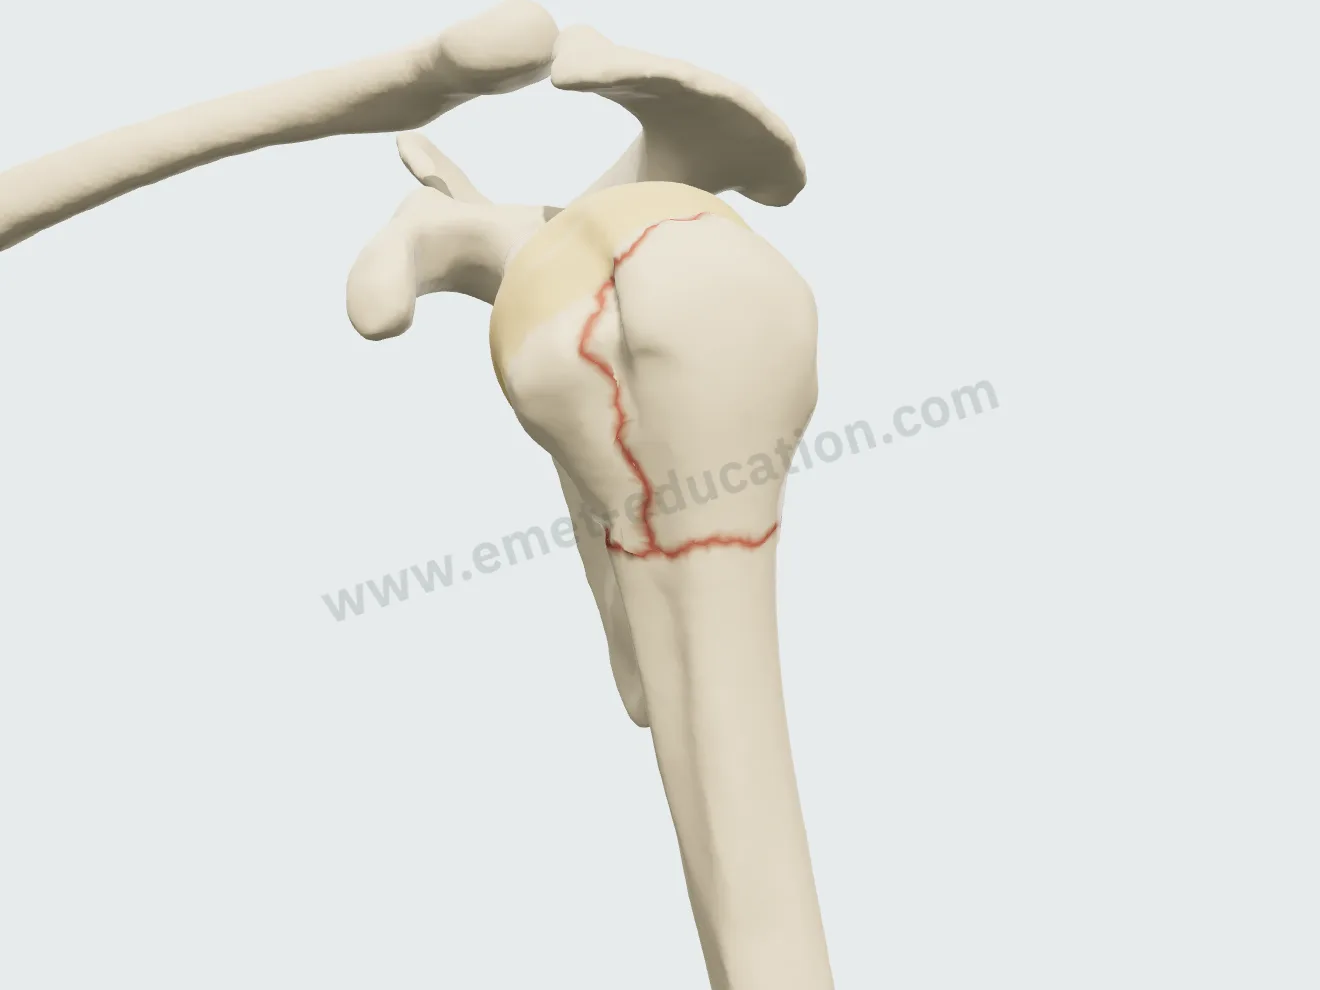
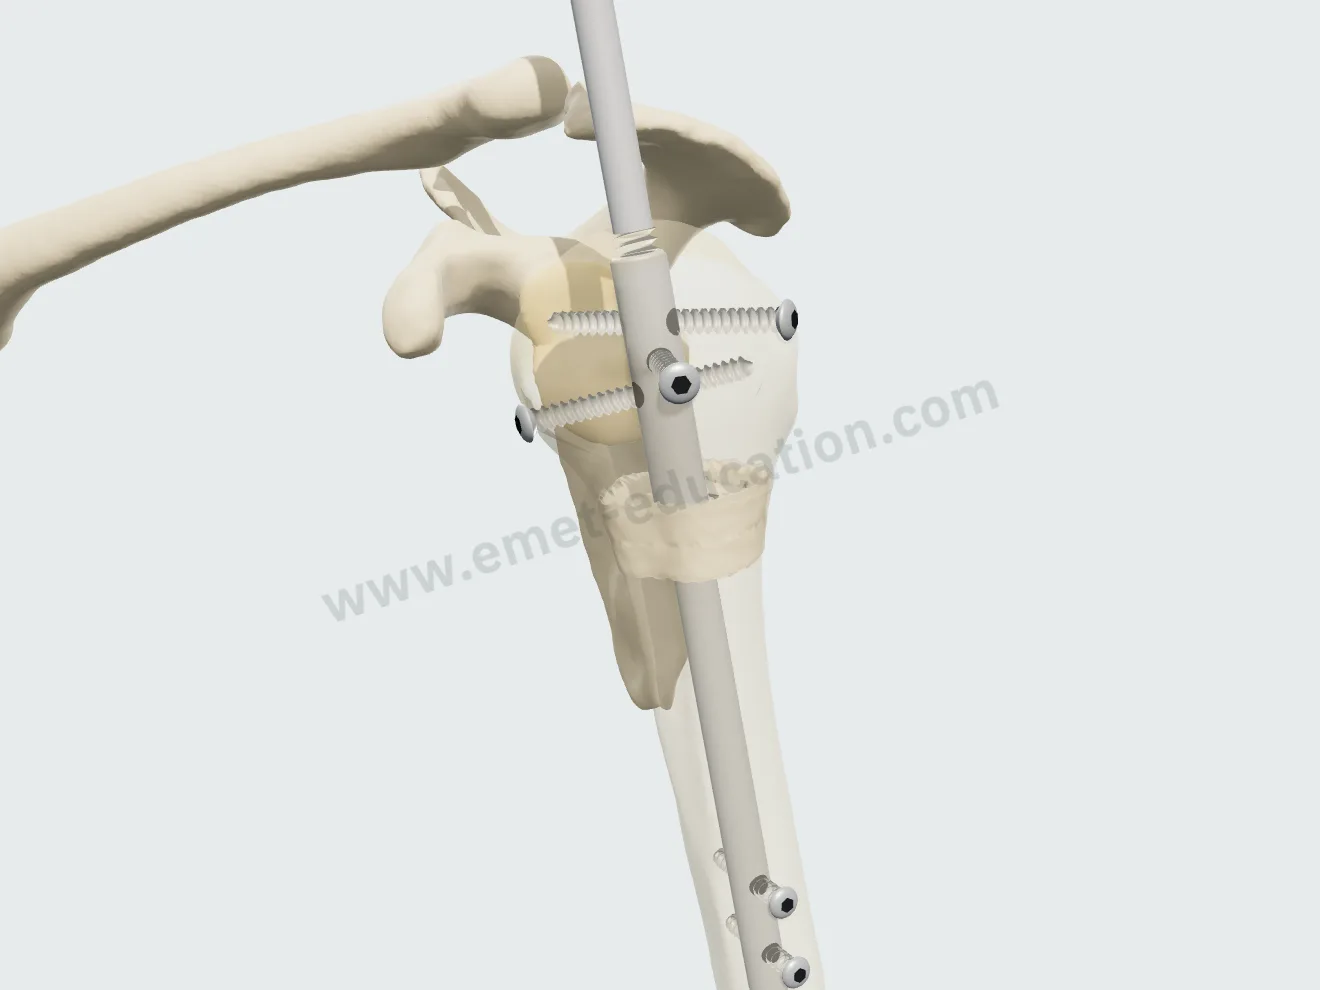
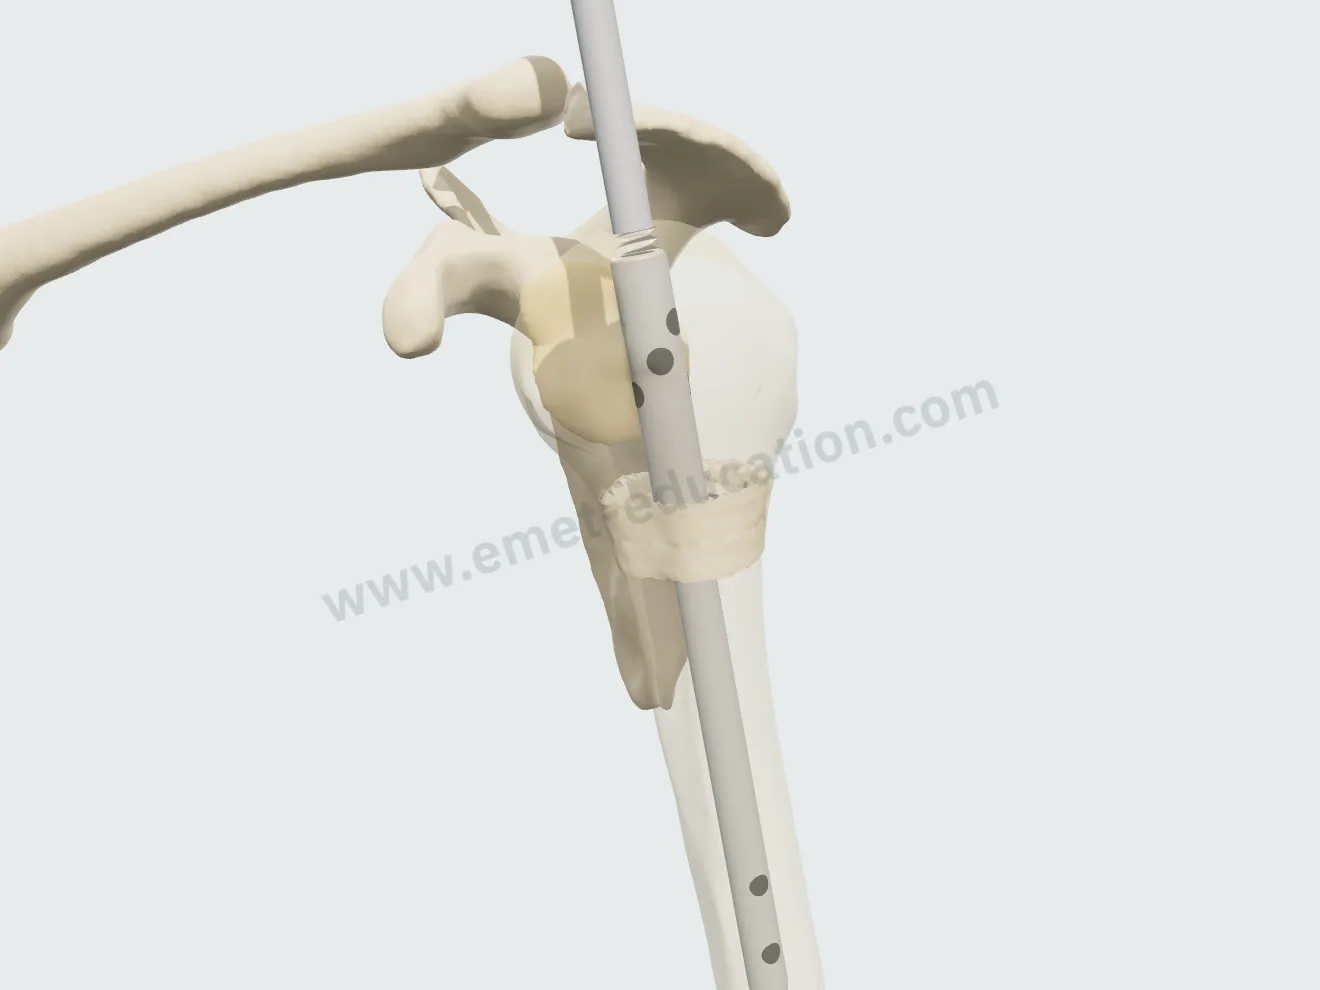
Straight third-generation locked nail (Boileau), inserted at the apex of the head, medial to the supraspinatus insertion; three screws in the head, two distal screws, an end cap.

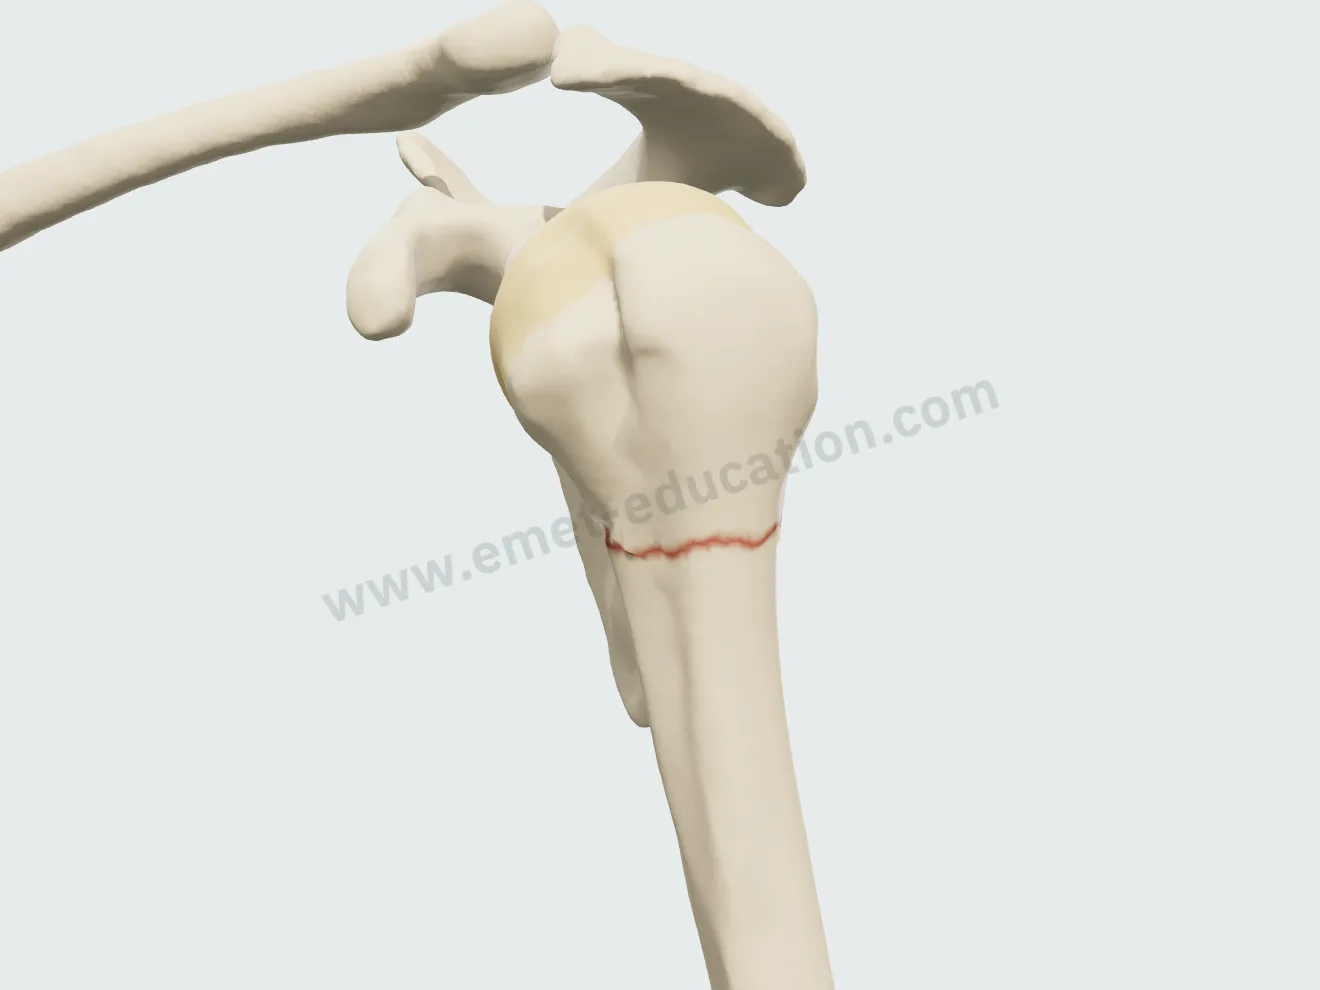
Intramedullary nail, step 1: the surgical neck fracture reduced.
1Reduction
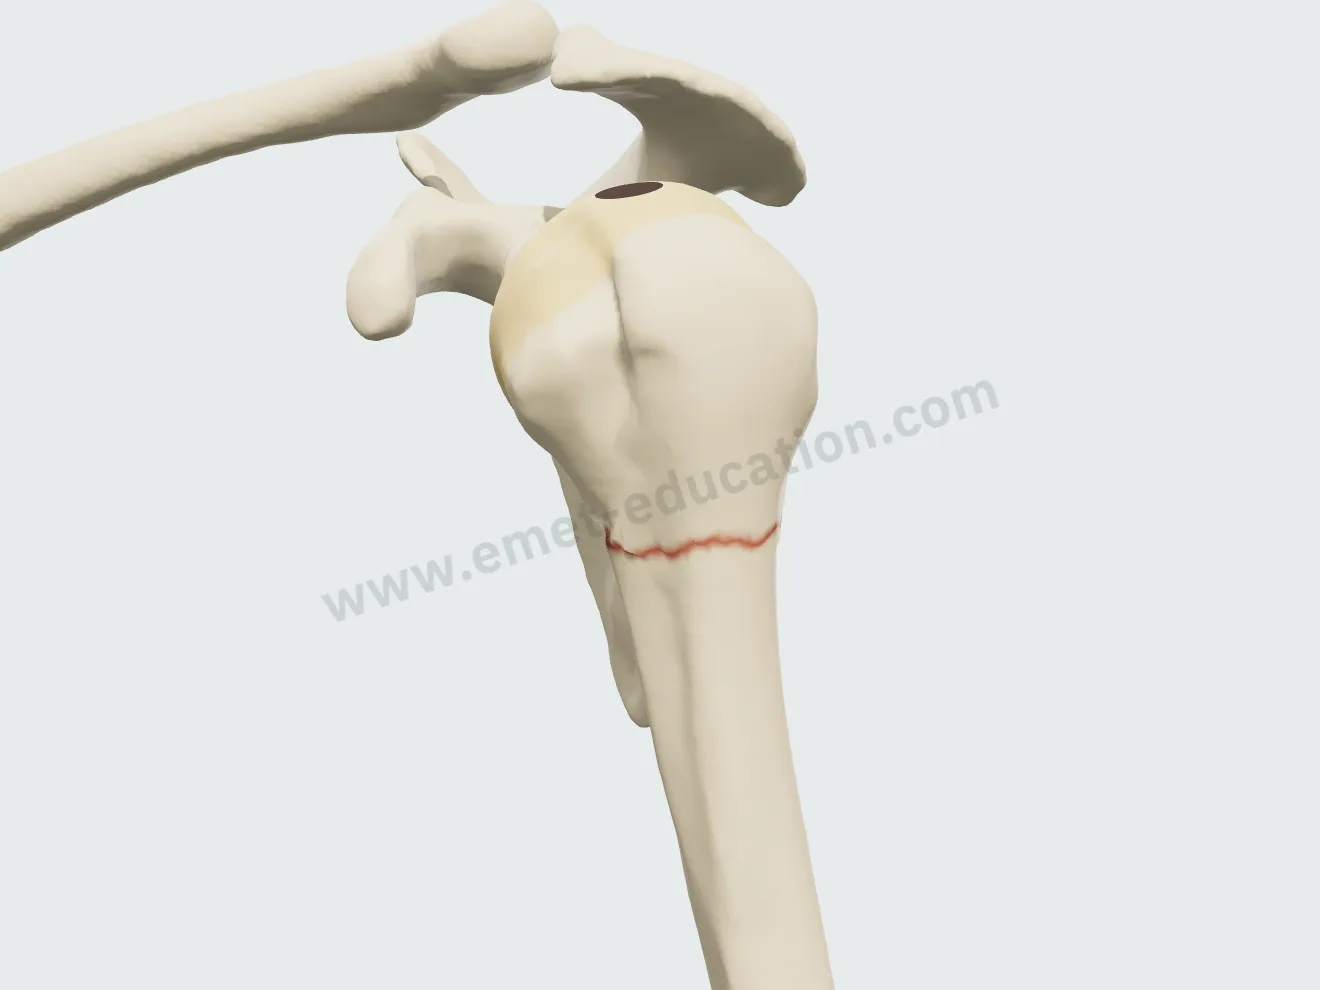
Intramedullary nail, step 2: the entry point opened at the apex of the head, in line with the medullary canal.
2Entry point
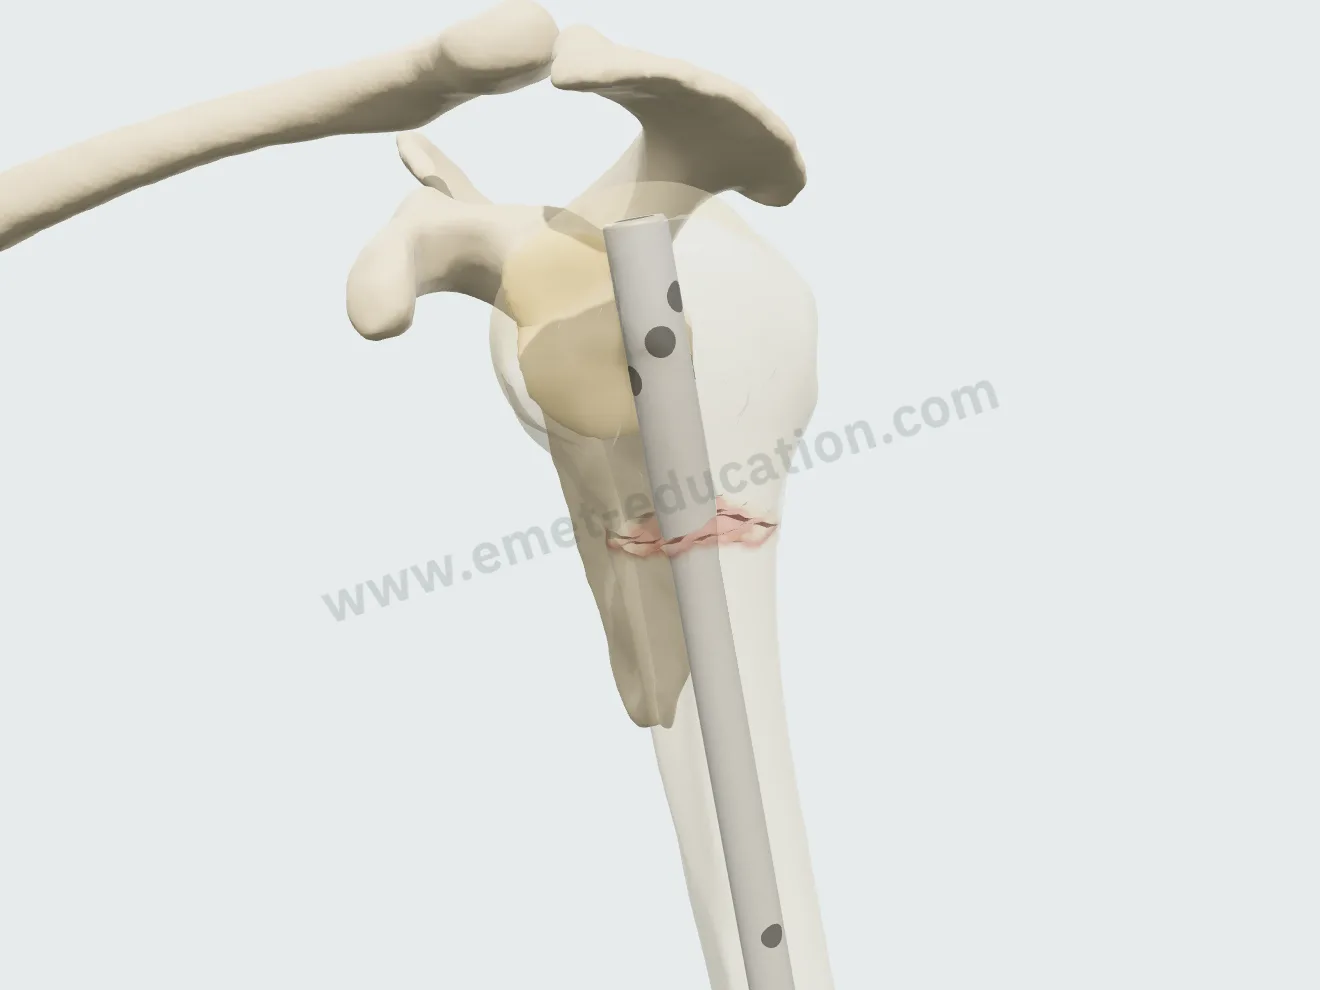
Intramedullary nail, step 3: the nail in the canal, the bone faded.
3Nail
Intramedullary nail, step 4: three locked screws in the head and tuberosities.
4Proximal screws
Intramedullary nail, step 5: two bicortical distal screws and the end cap.
5Distal screws, end cap
Intramedullary nail, step 6: the fracture healed over the nail.
6Healing

Locking plate

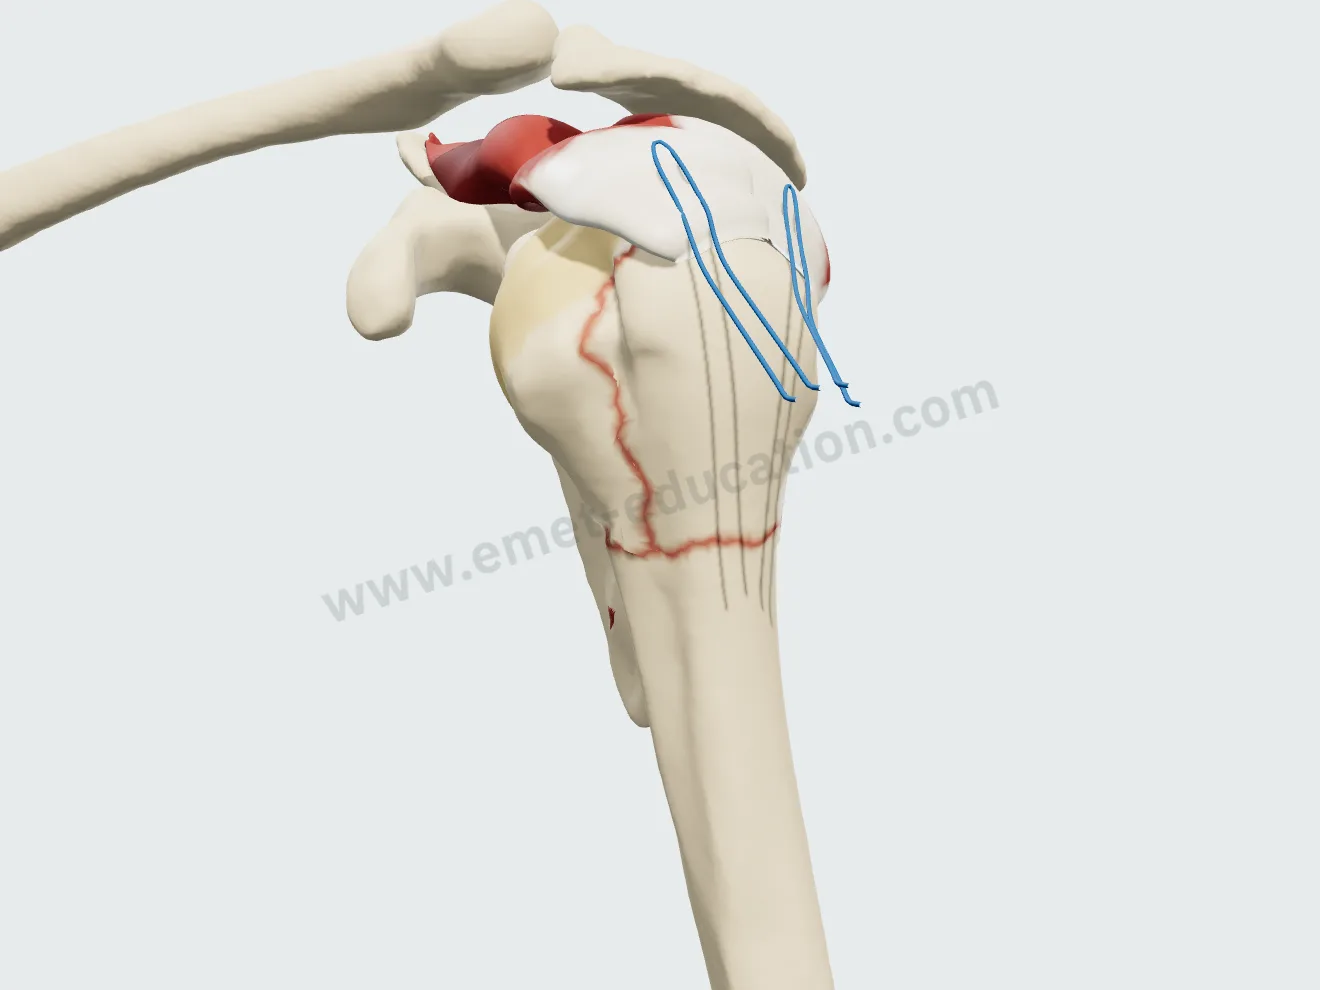
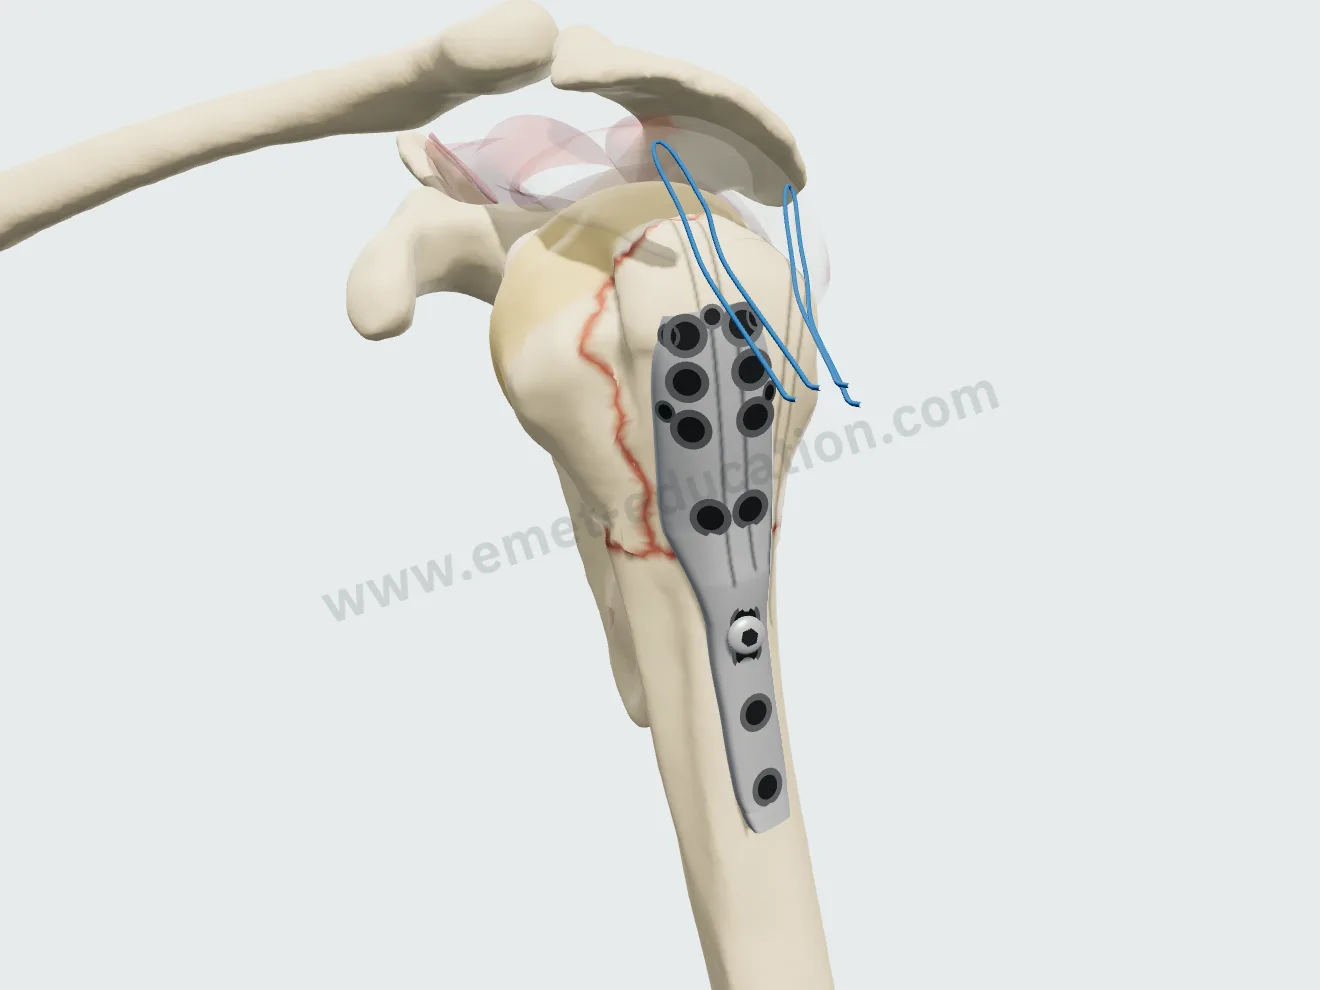
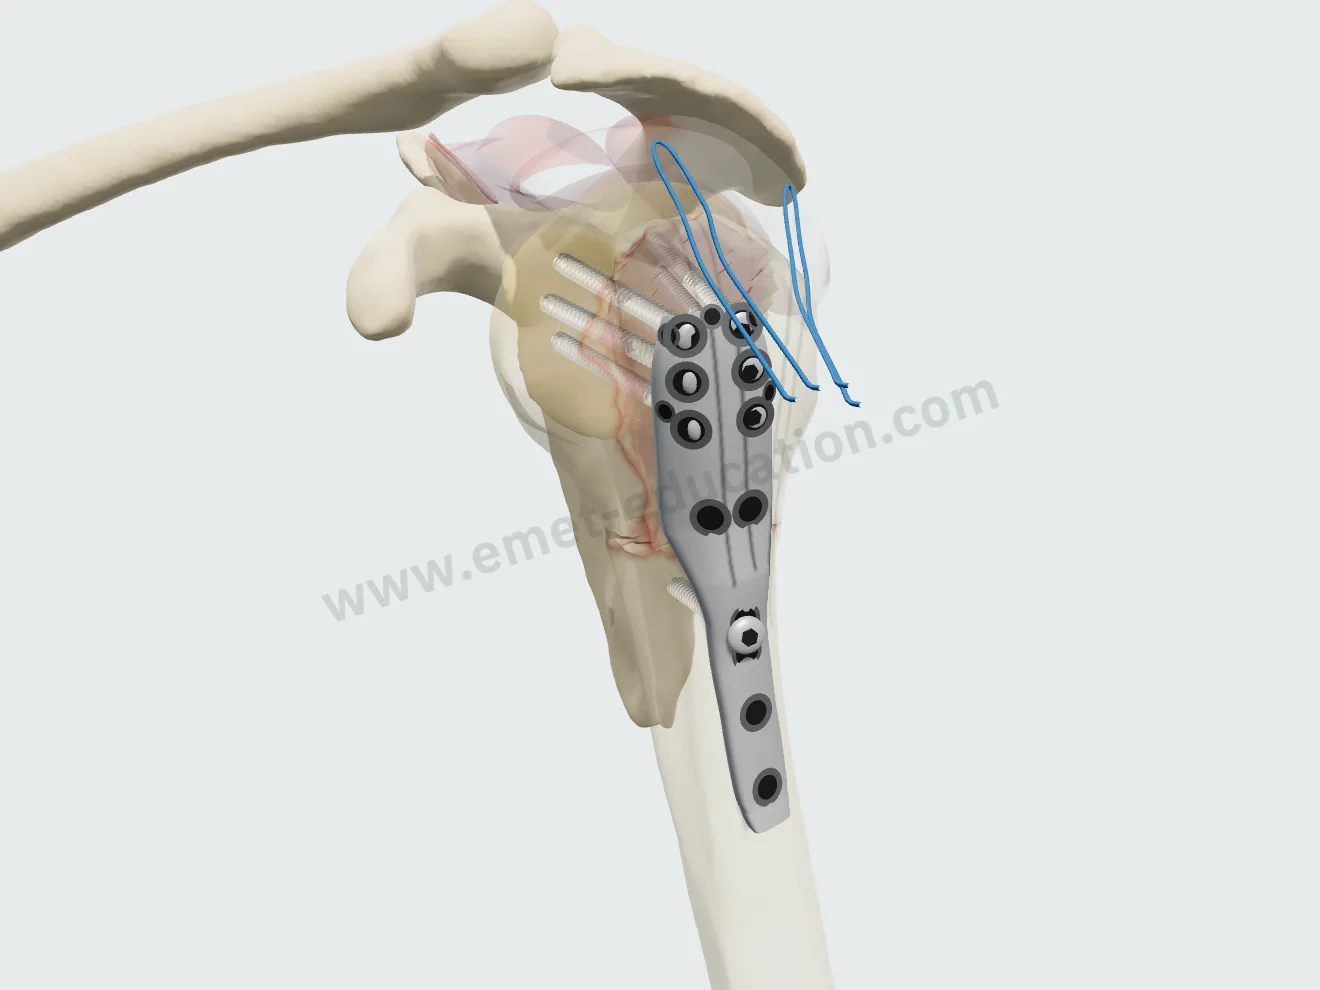
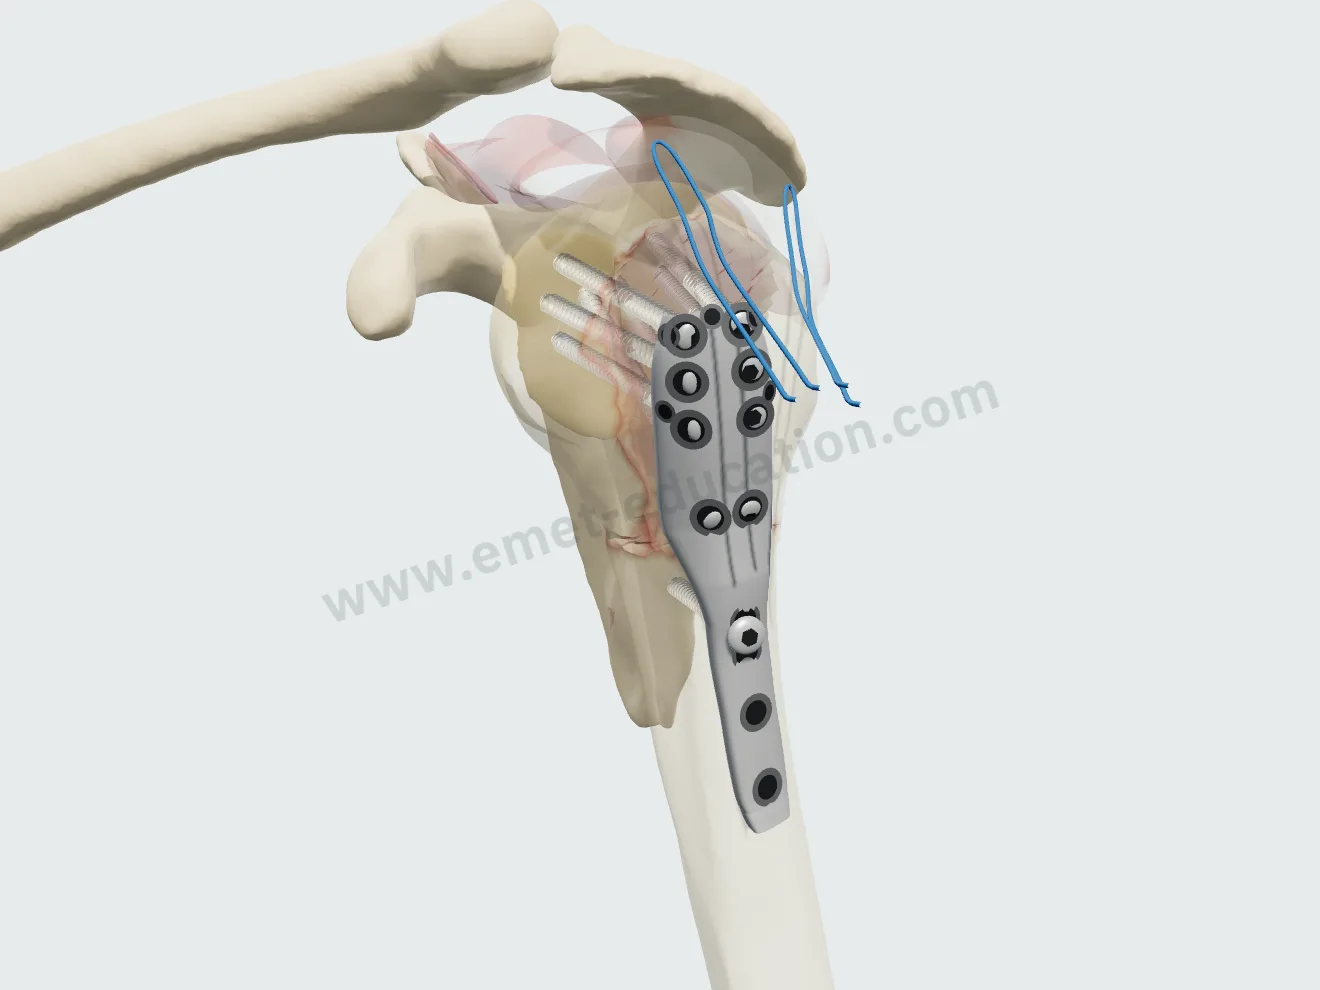
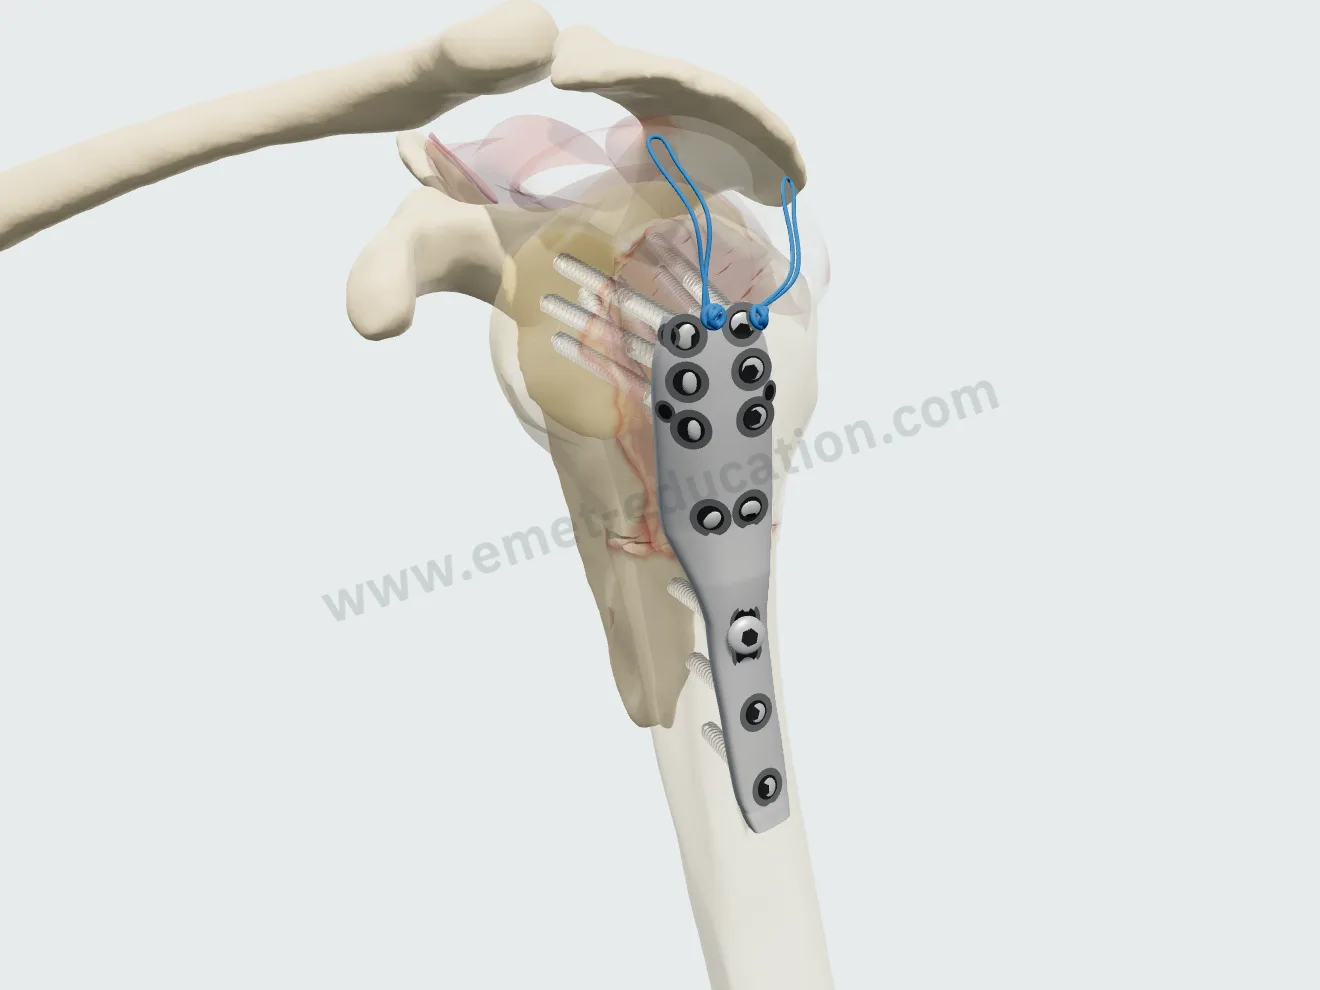
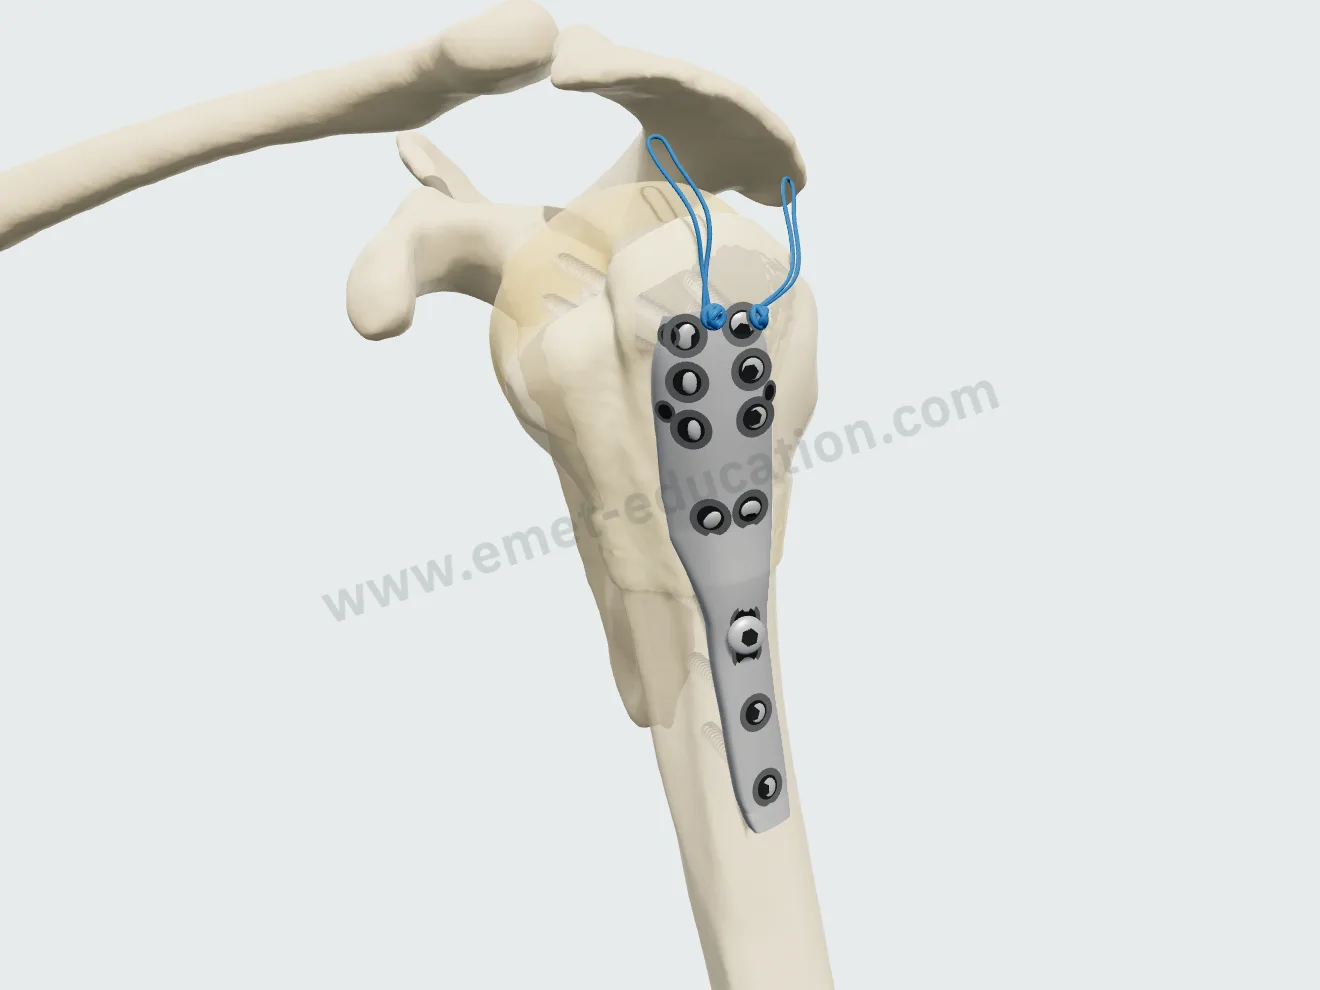
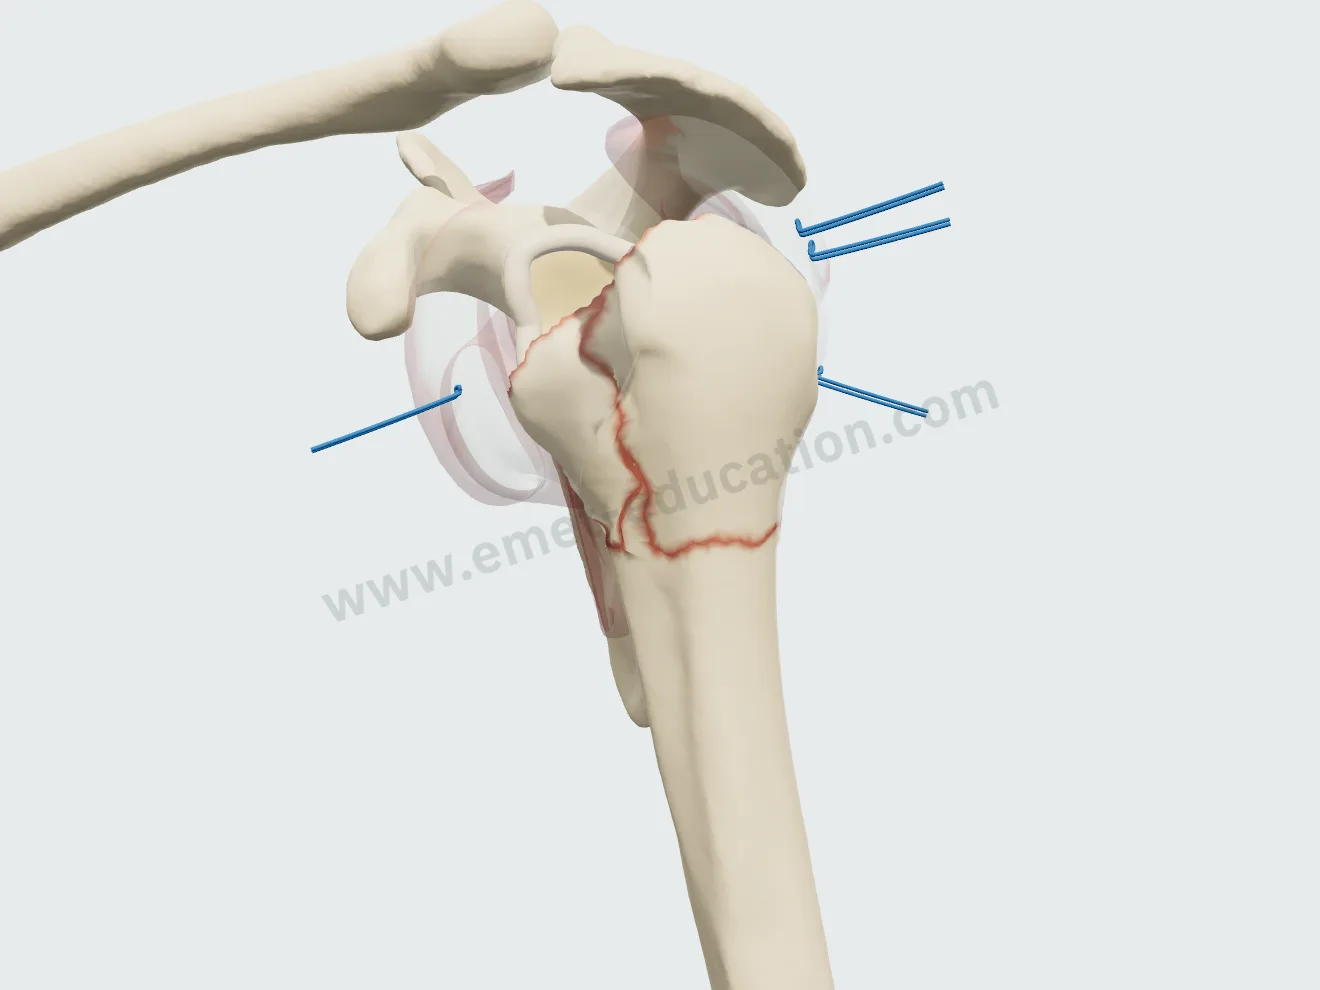
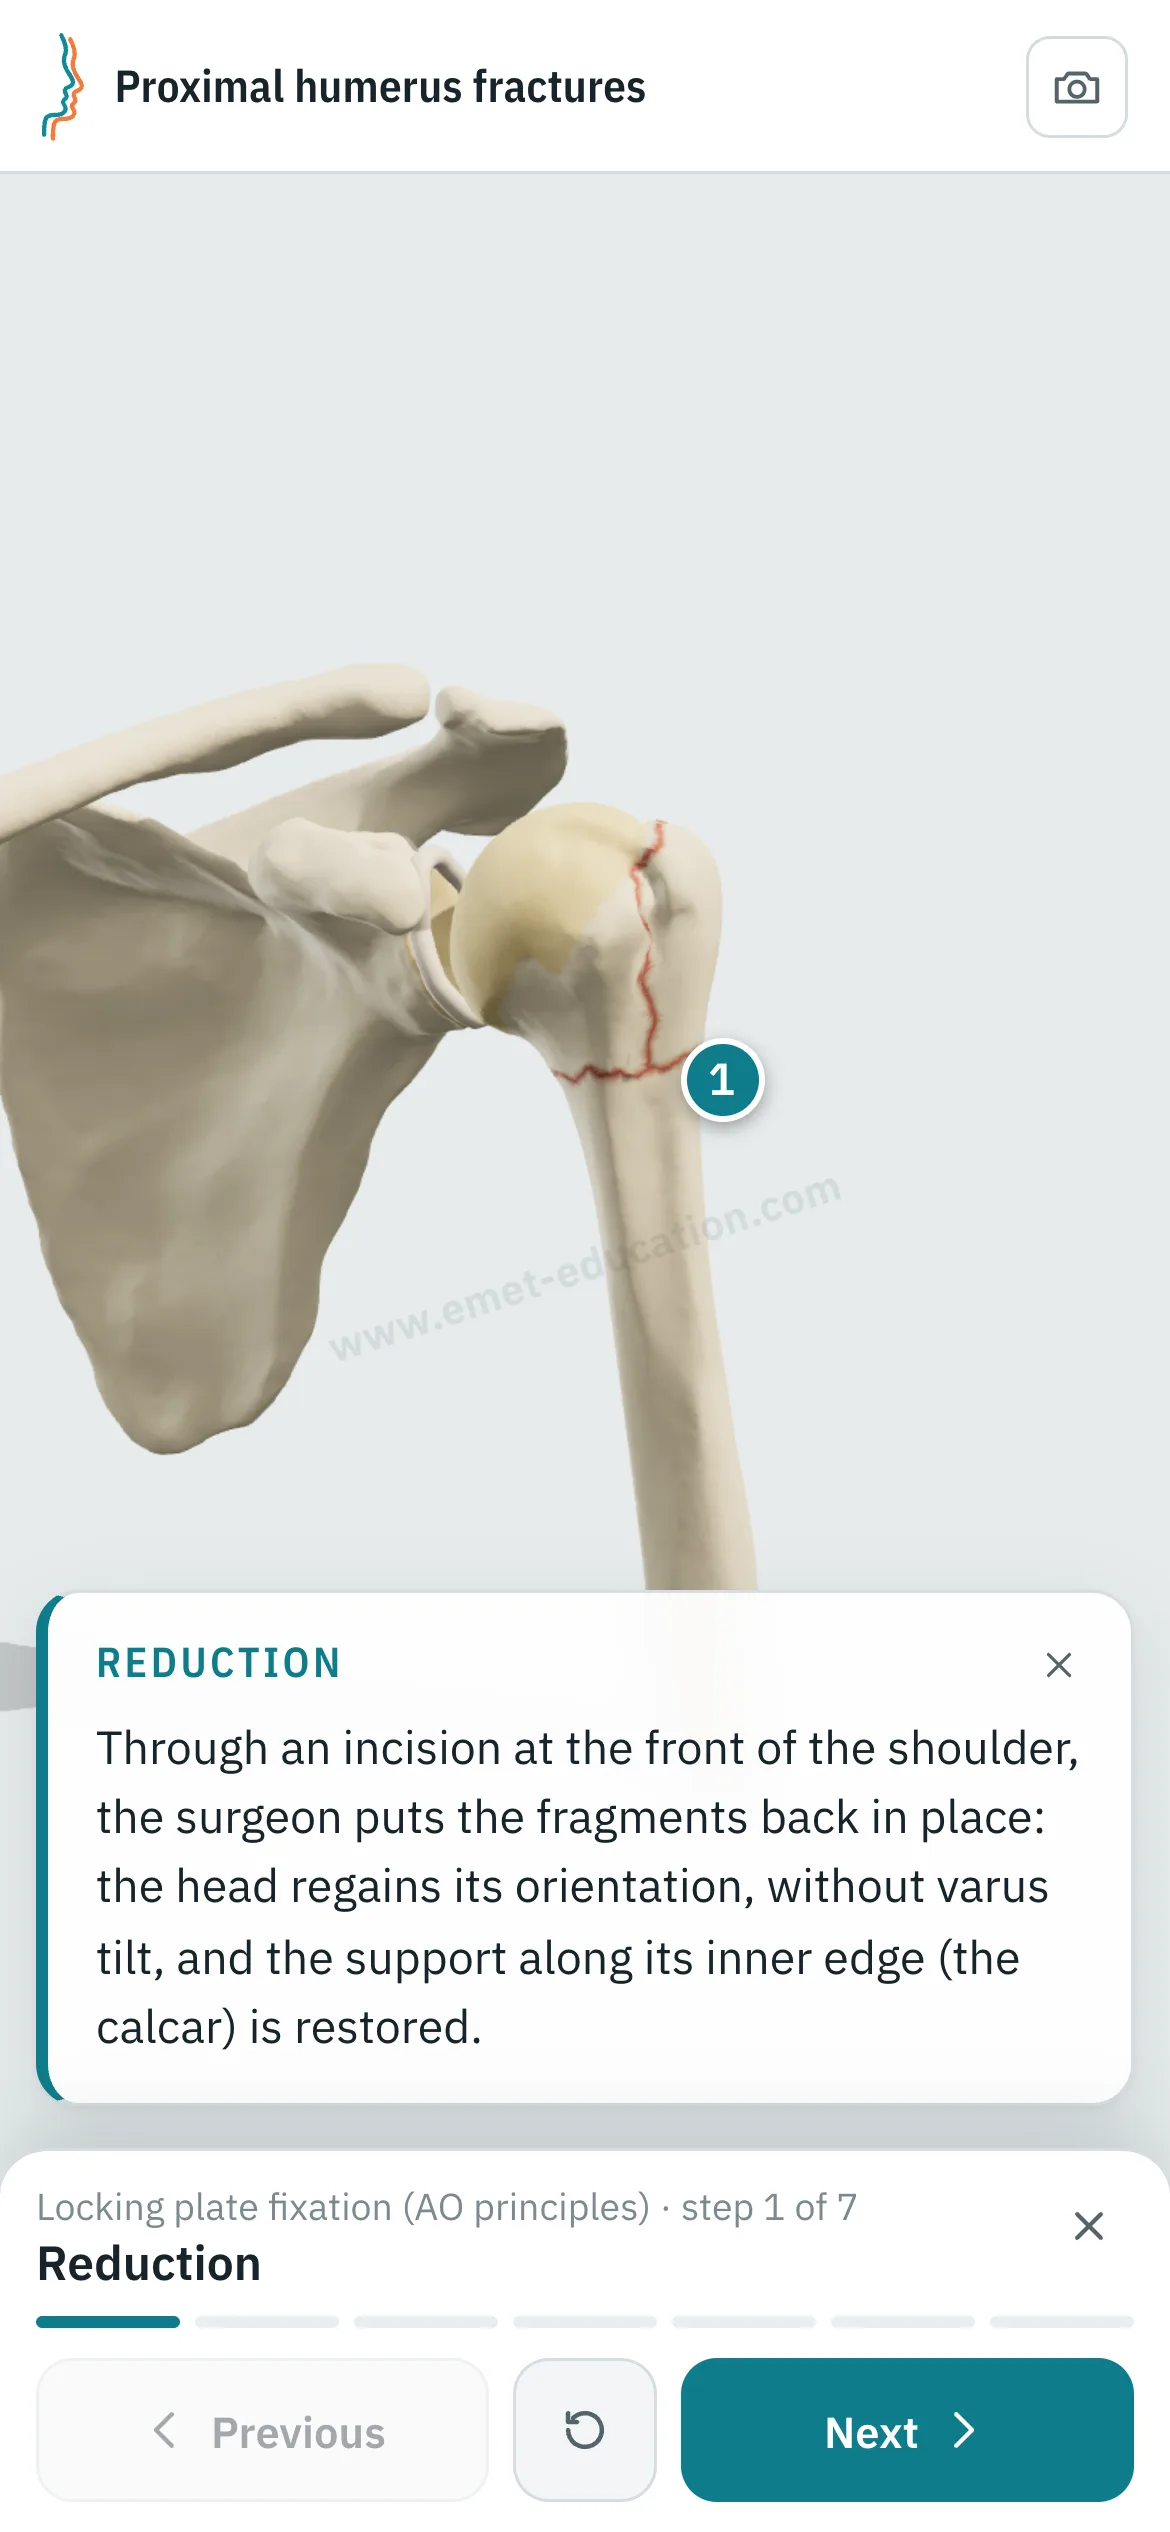
Following AO principles (Laux): reduction, sutures through the rotator cuff tendons tied to the plate, divergent head screws, two calcar screws, shaft screws.

Locking plate, step 1: 3-part fracture reduced, greater tuberosity in place.
1Reduction
Locking plate, step 2: sutures passed through the supraspinatus and infraspinatus tendons.
2Cuff sutures
Locking plate, step 3: the plate placed posterior to the bicipital groove, below the top of the greater tuberosity.
3Plate
Locking plate, step 4: six divergent head screws, the bone faded.
4Head screws
Locking plate, step 5: two calcar screws along the medial cortex of the neck.
5Calcar screws
Locking plate, step 6: bicortical shaft screws, sutures tied to the plate.
6Shaft screws, knots
Locking plate, step 7: the fracture healed.
7Healing

Reverse shoulder arthroplasty

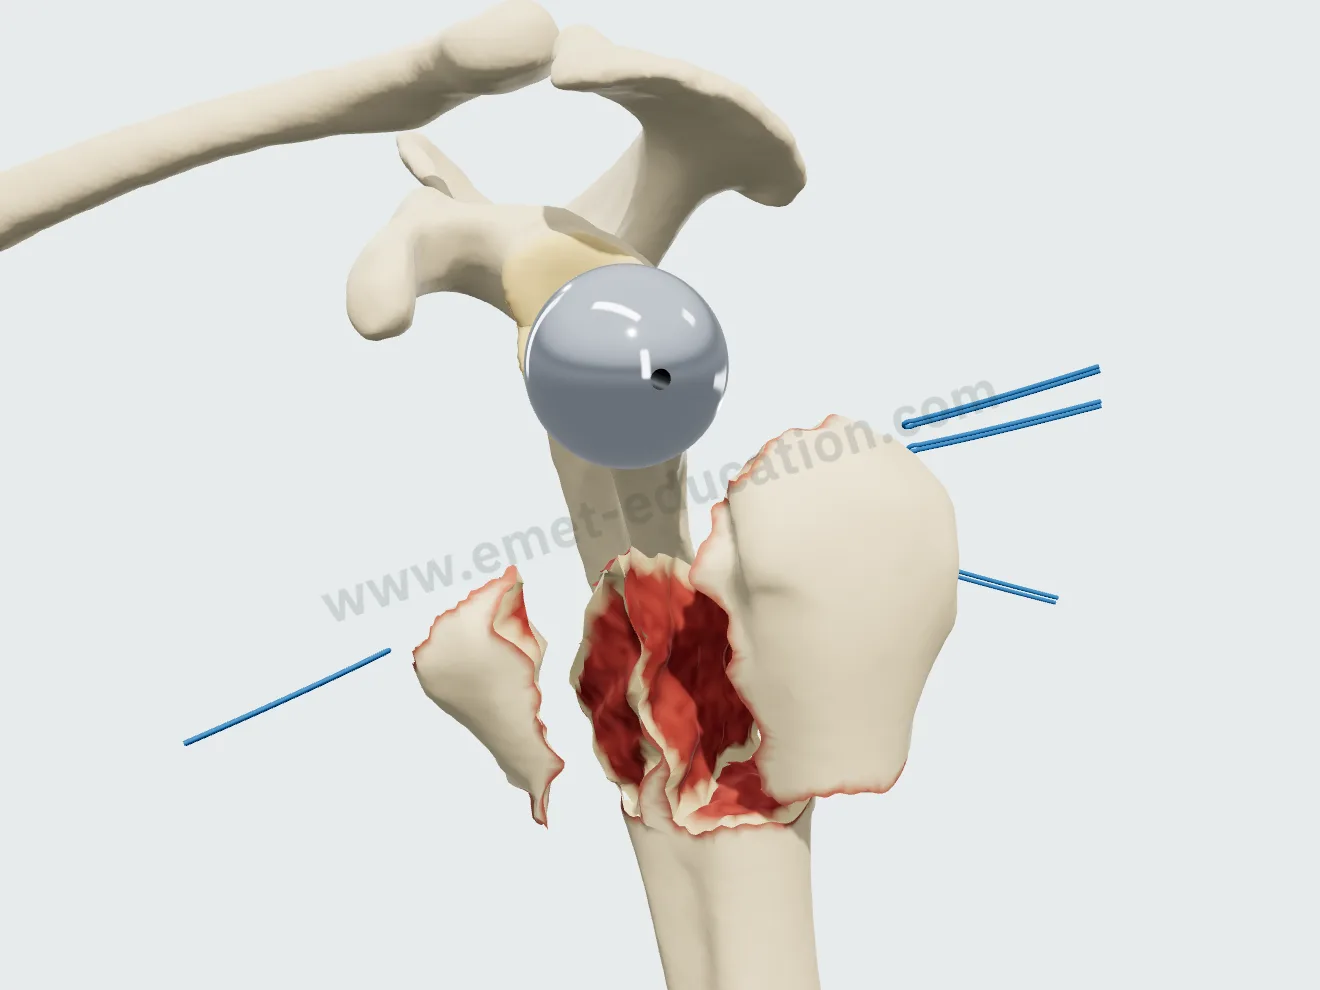
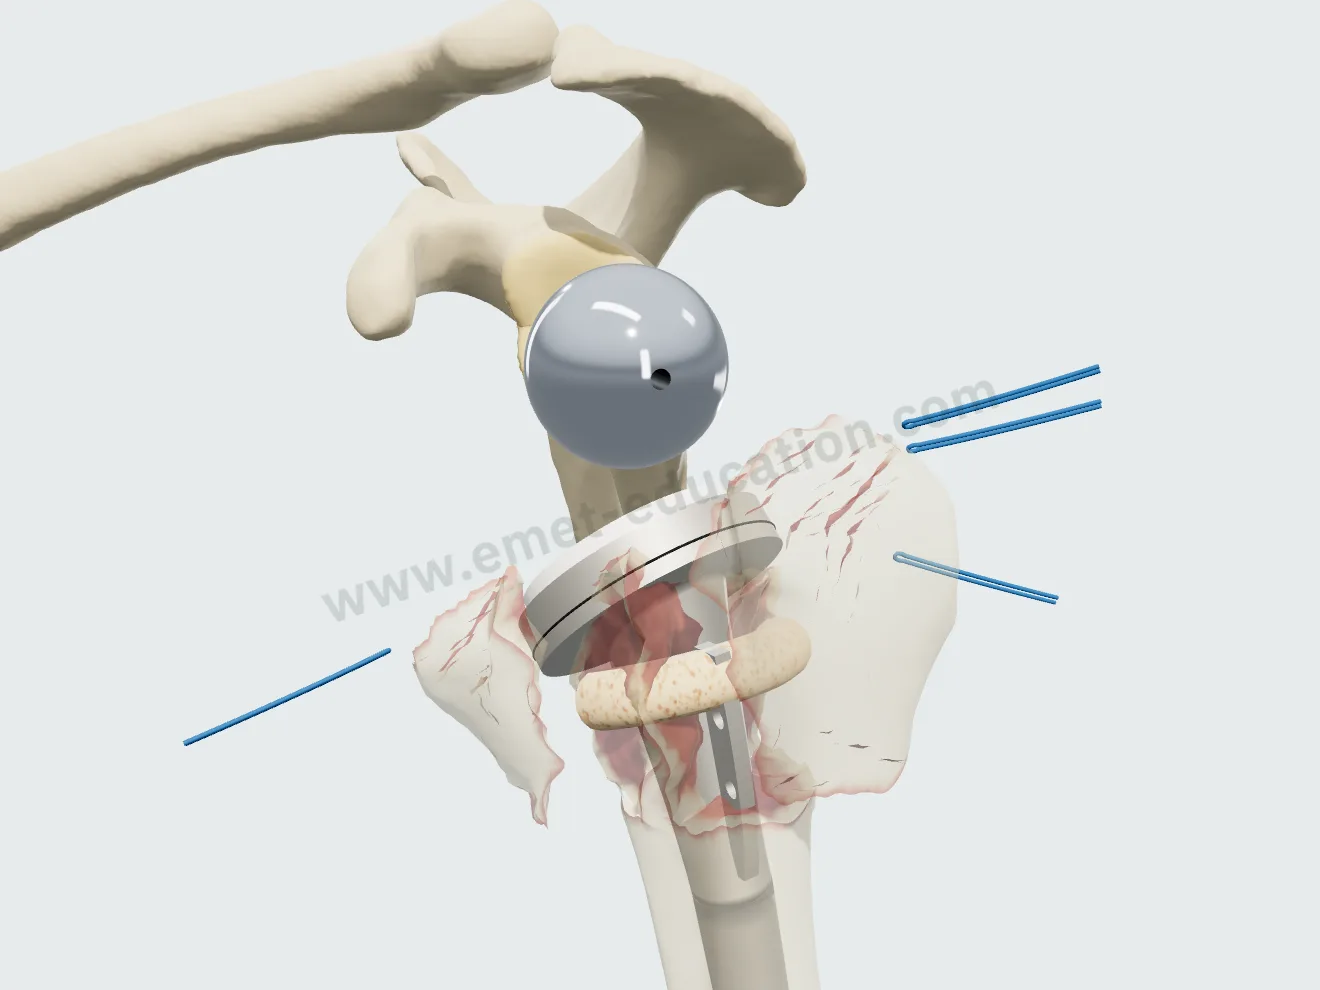
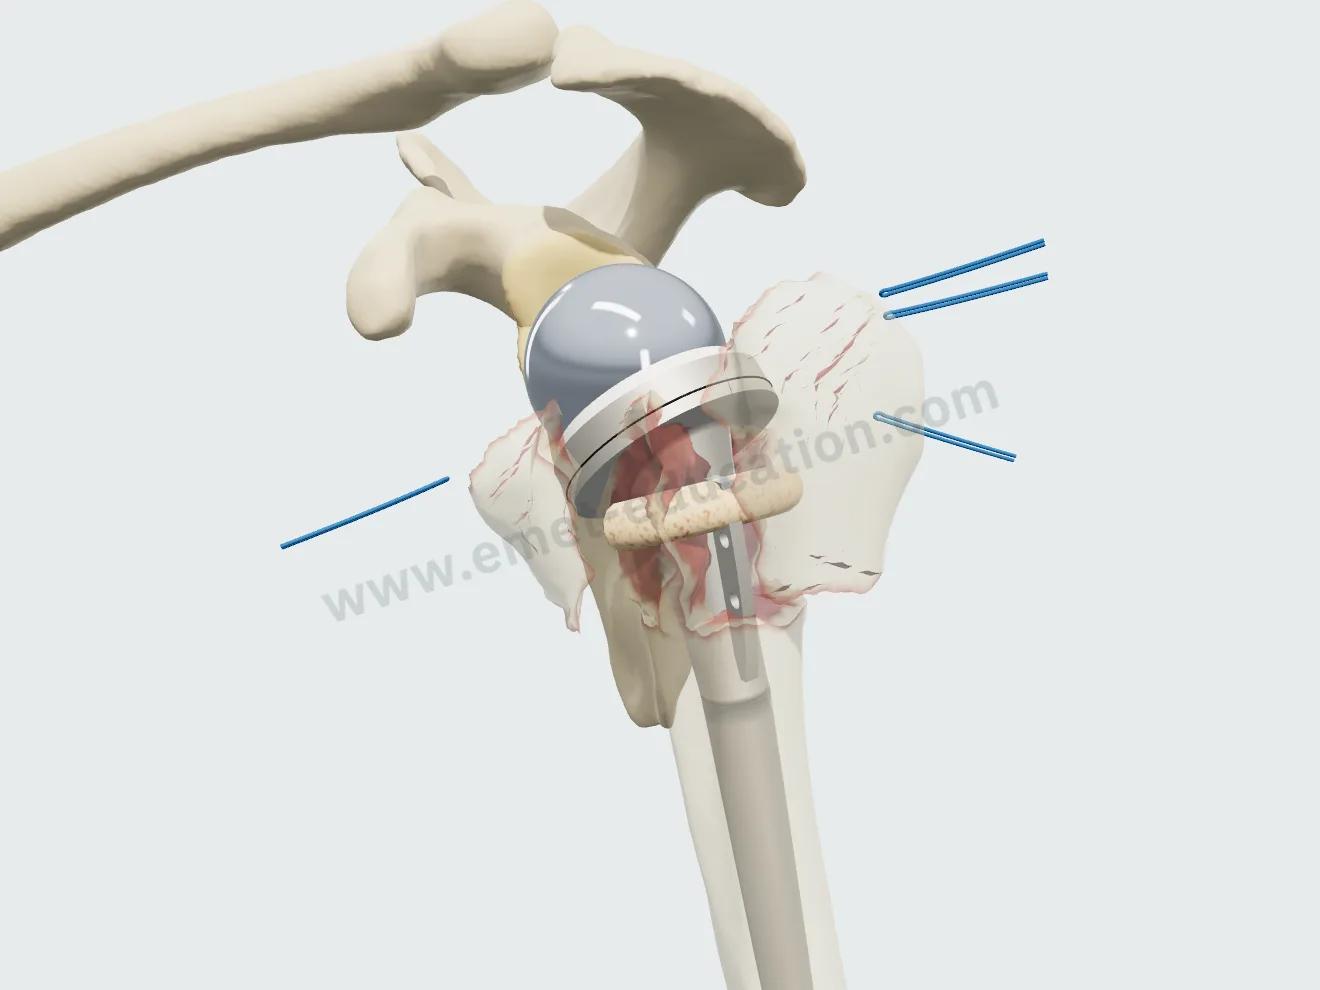
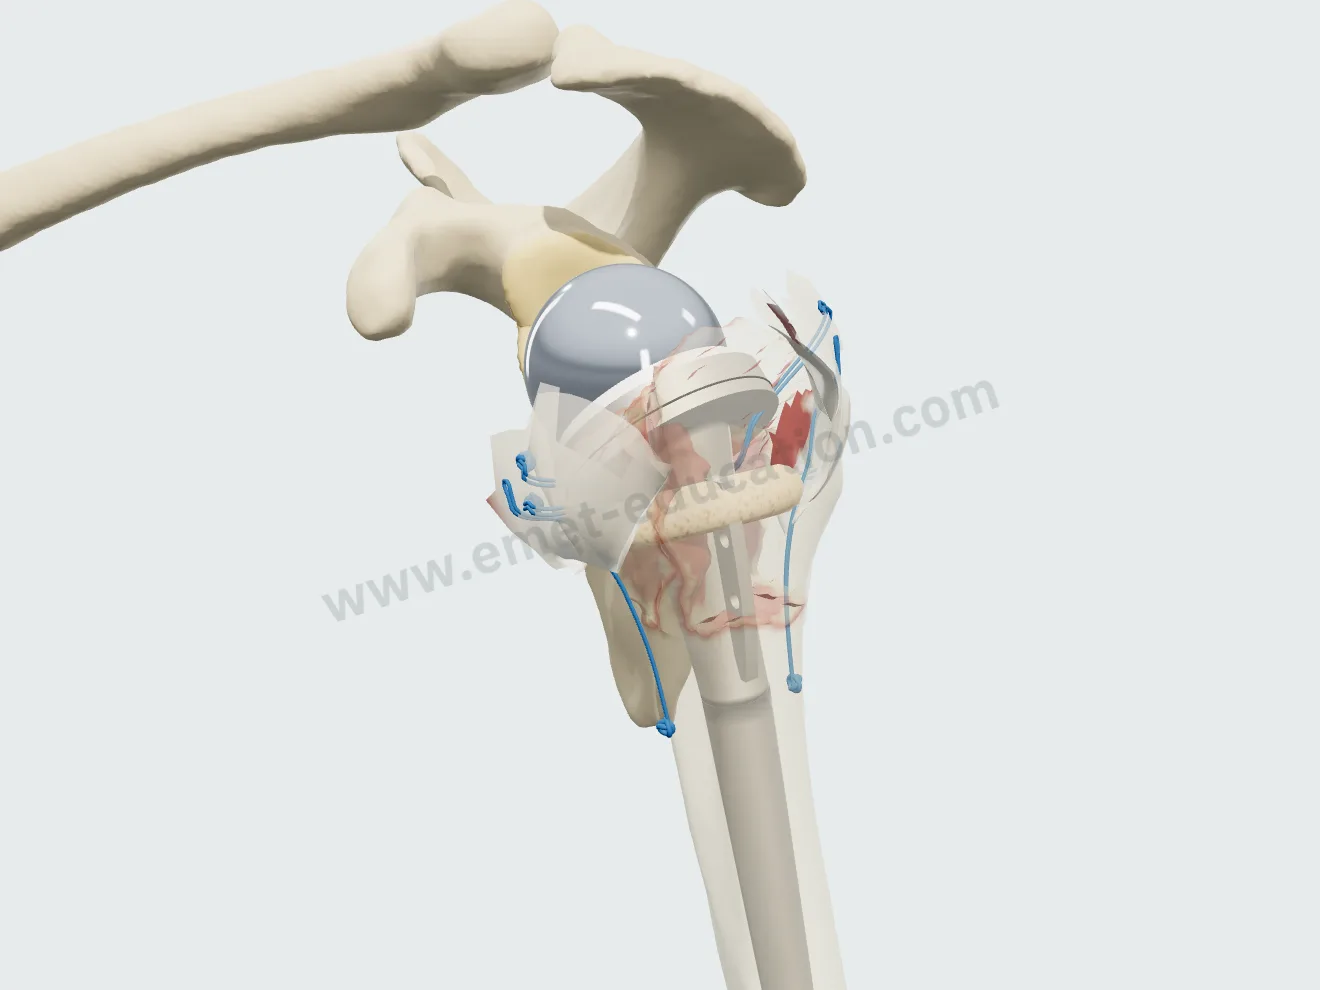
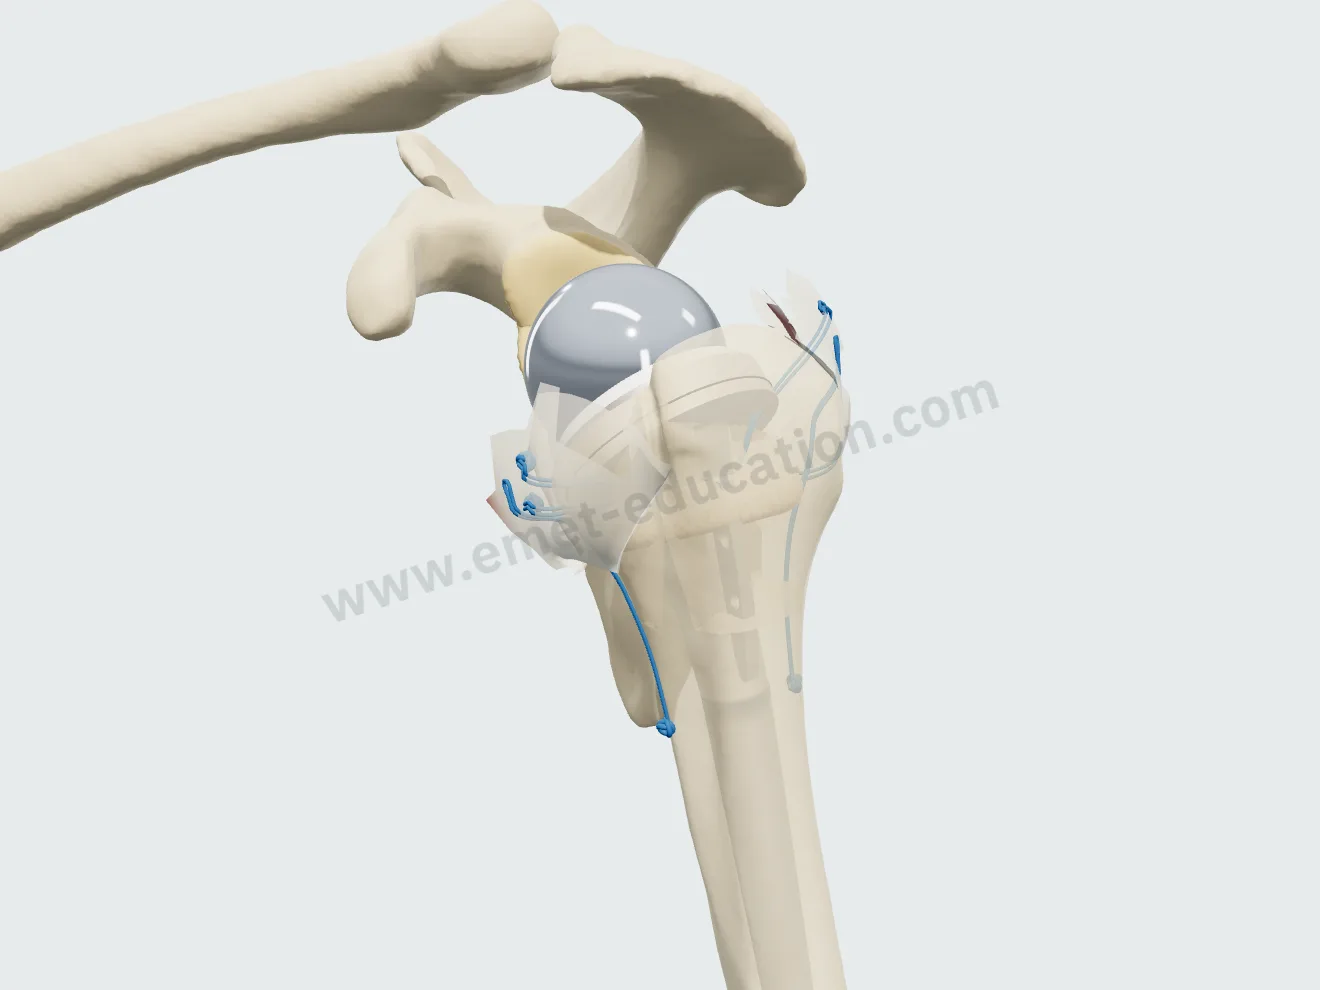
For fracture: head removed, sutures through the tendons, baseplate and glenosphere, fracture stem and graft from the head, then tuberosity repair around the stem (Boileau).

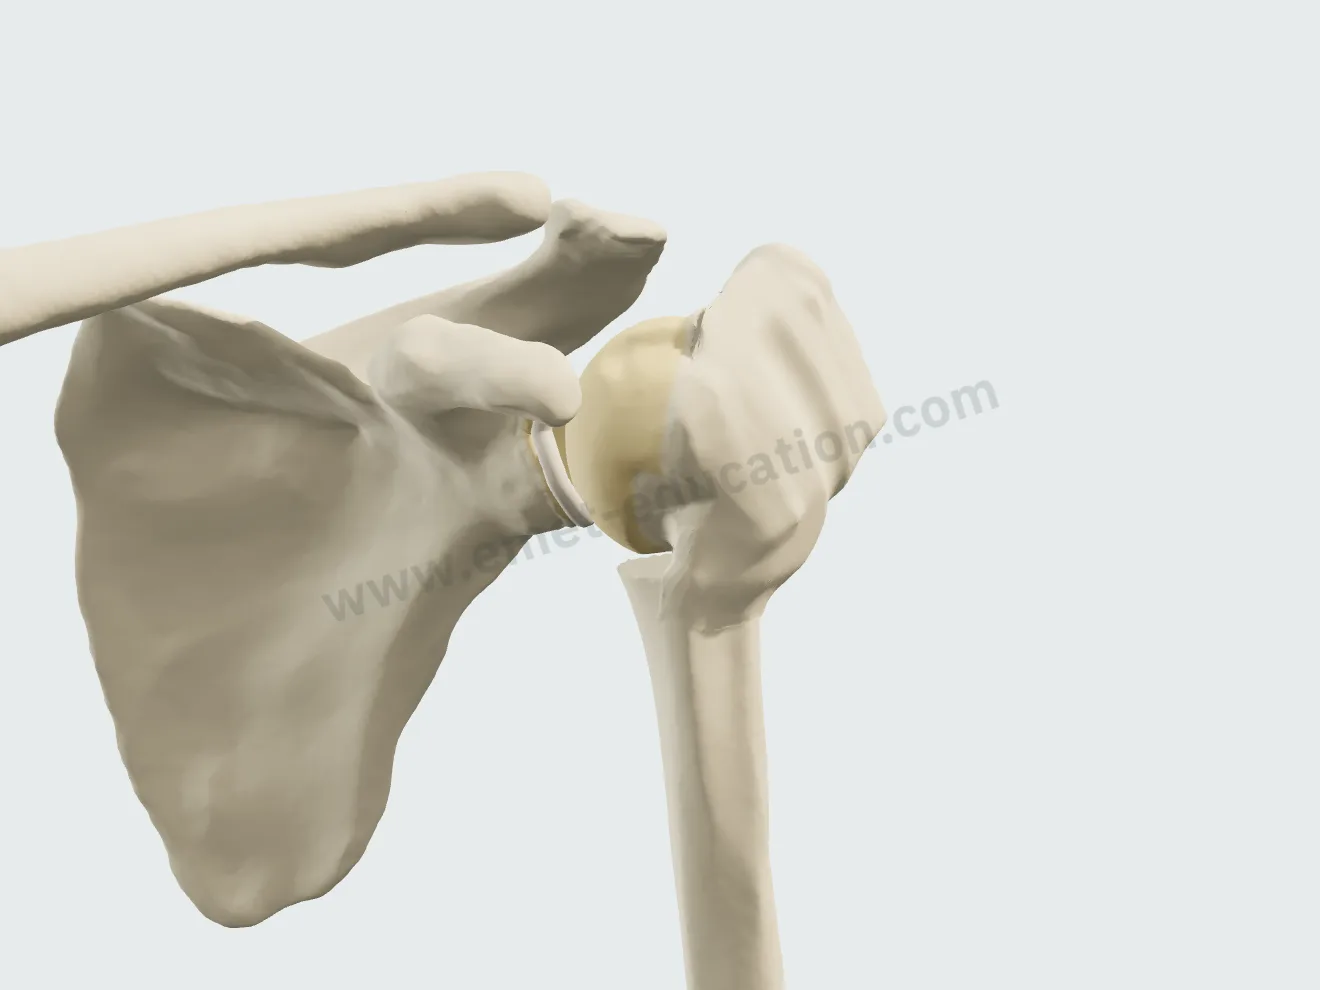
Reverse arthroplasty, step 1: humeral head removal; the tuberosities, reduced, and the calcar are preserved.
1Head removal
Reverse arthroplasty, step 2: sutures passed at the tendon-bone junction of the tuberosities.
2Tendon sutures
Reverse arthroplasty, step 3: baseplate screwed in and glenosphere on the glenoid.
3Glenoid
Reverse arthroplasty, step 4: fracture stem, cancellous graft around the metaphysis, liner.
4Stem and graft
Reverse arthroplasty, step 5: the prosthesis reduced, humerus lowered.
5Reduction
Reverse arthroplasty, step 6: the tuberosities reduced and fixed around the stem with the sutures.
6Tuberosities fixed
Reverse arthroplasty, step 7: the tuberosities healed around the prosthesis.
7Healing

Hardware removal

Once the fracture has healed, after a nail as after a plate. Here the nail: end cap and extractor, screws, nail, then healing of the entry point.

Nail removal, step 1: the end cap unscrewed, the extractor threaded into the top of the nail.
1End cap, extractor
Nail removal, step 2: the screws removed, the locking holes visible.
2Screws
Nail removal, step 3: the nail, pulled by the extractor, comes out through the head.
3Nail
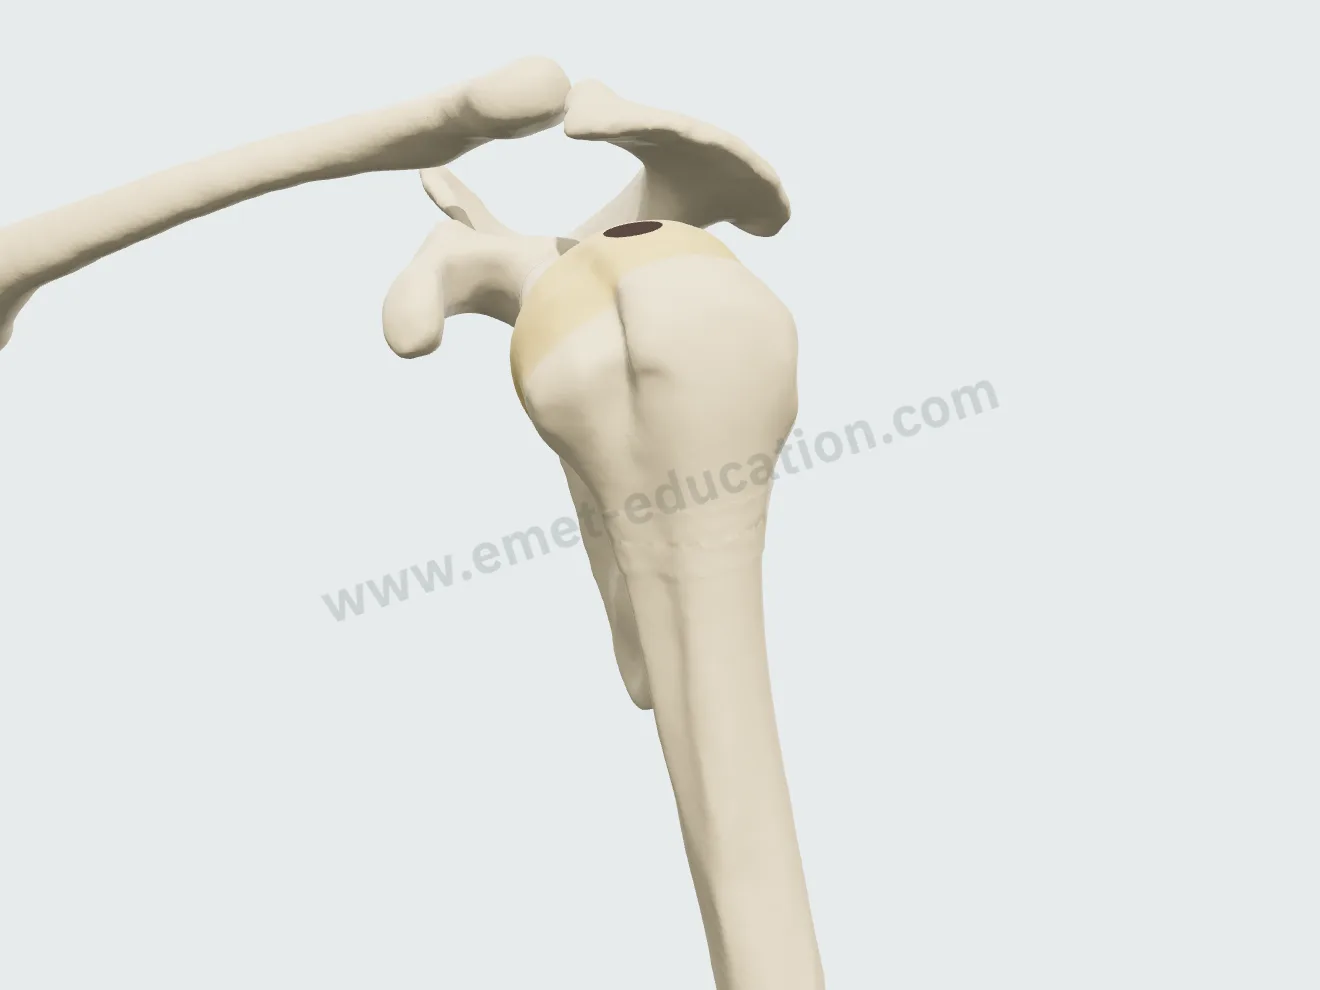
Nail removal, step 4: the entry point filled with fibrous scar tissue.
4Healing

After the visit

The patient leaves with their 3D model

They scan the QR code: the model, their findings and the proposed treatment follow them on their phone, in their language.

The model, exactly as you set it

At the end of the visit, the Consultation panel shows the anatomical findings, the proposed treatment and a QR code. The patient scans it and finds the model on their phone exactly as you set it, in their language.

  • Their fracture, and the proposed treatment to replay step by step.
  • Their anatomical findings and the explanatory card.
  • No identifying data in the link.
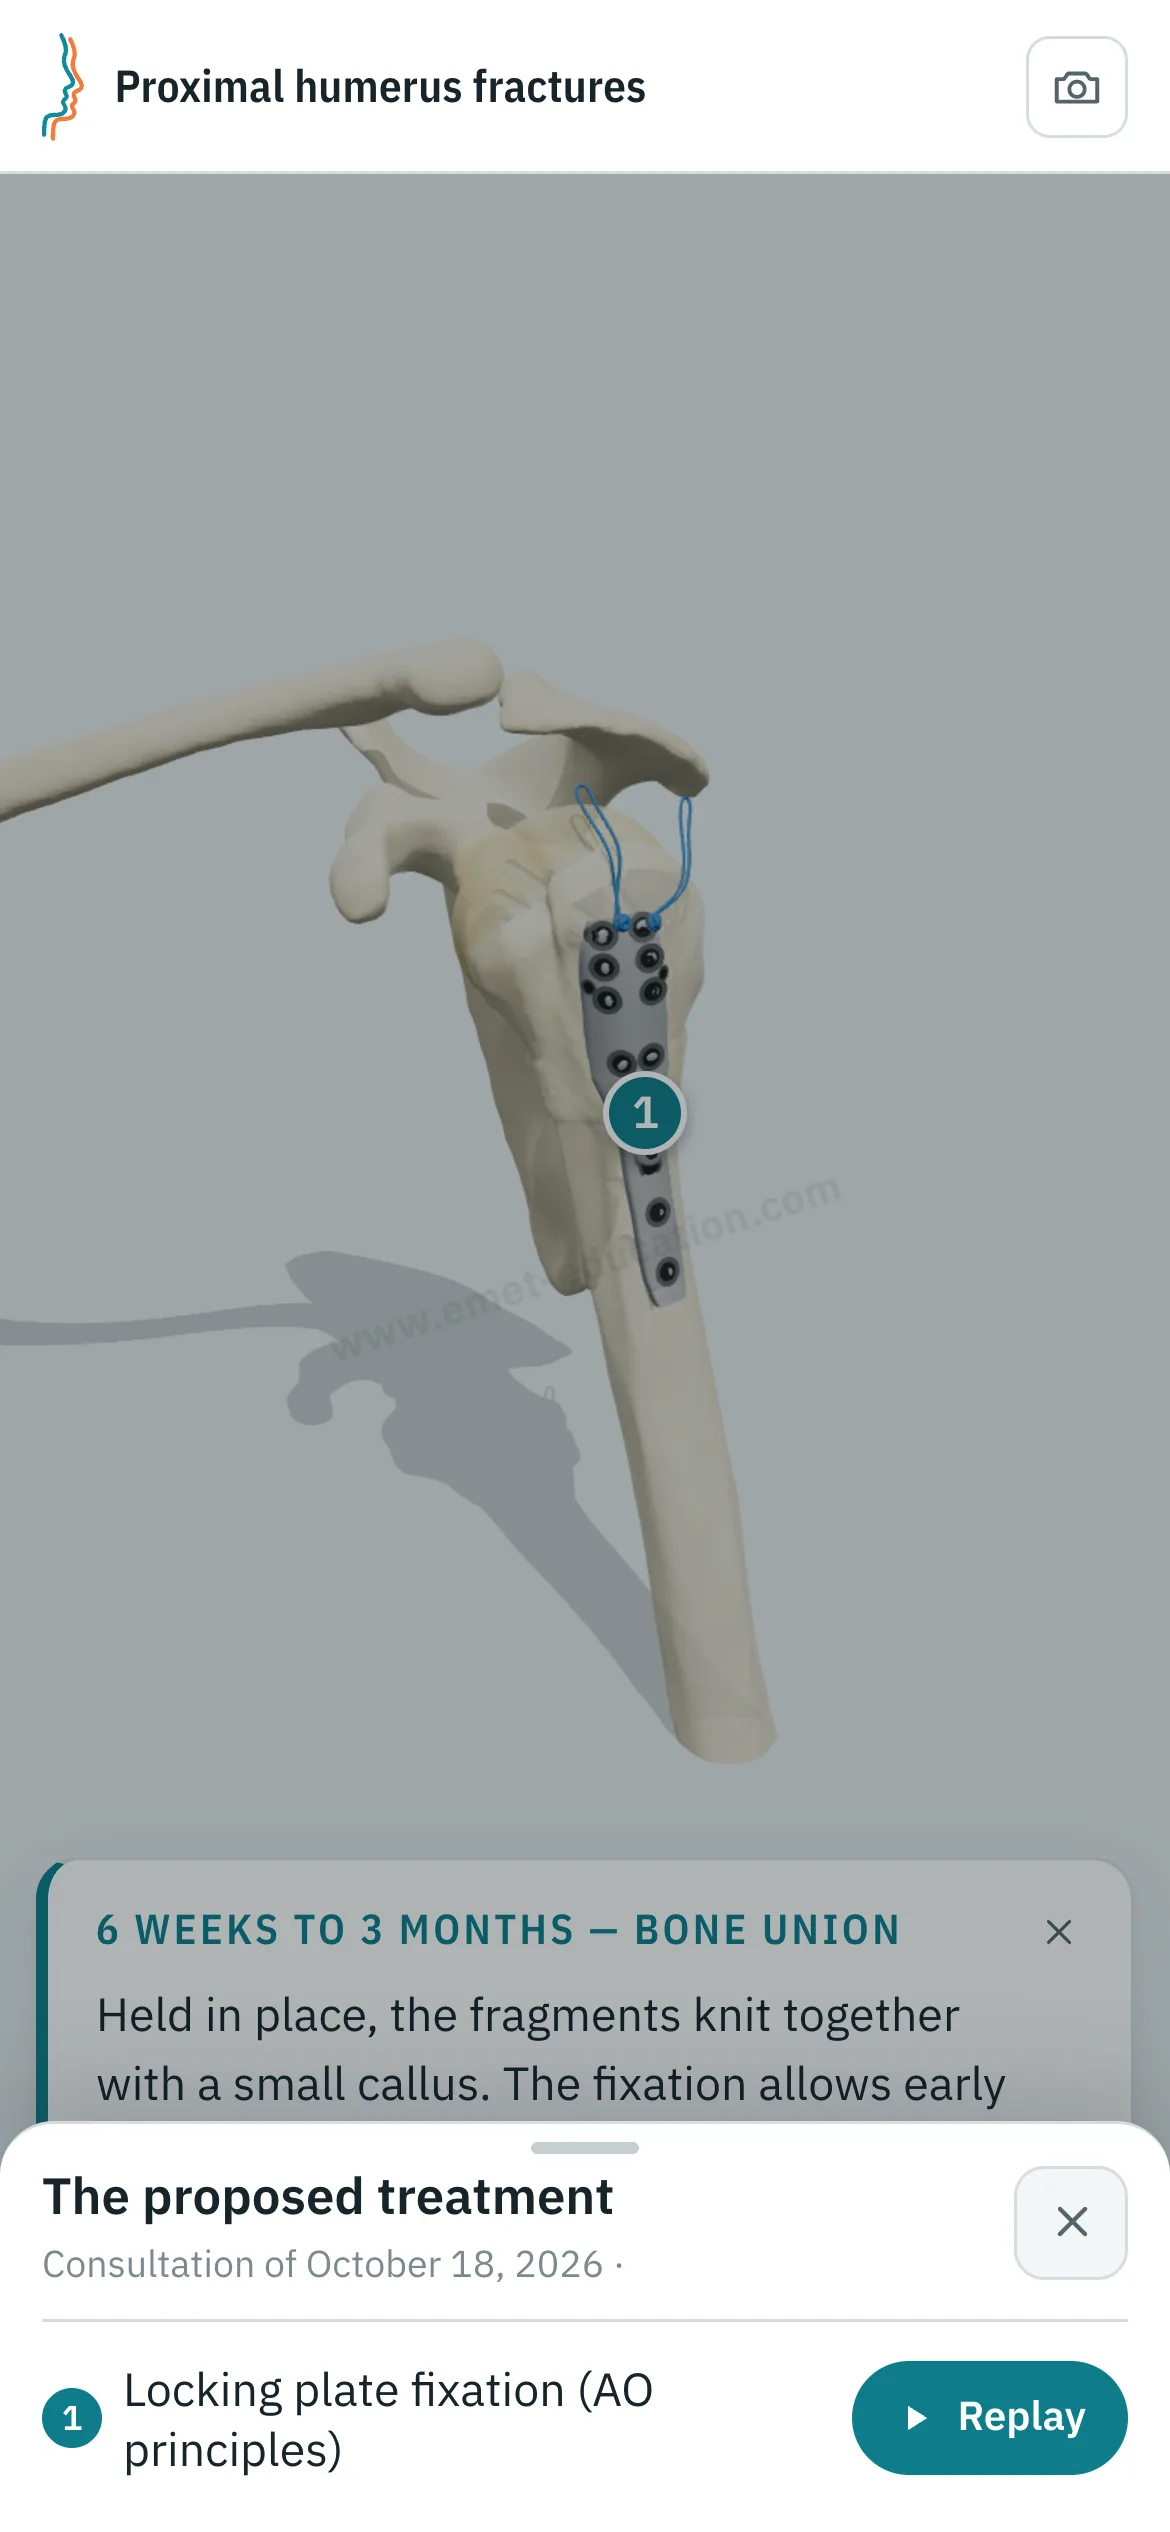
Patient view on a phone: the humerus after locking plate fixation, and the “The proposed treatment” panel open, with the “Replay” button.
What the patient sees after scanning the QR code

Every structure explains itself on tap

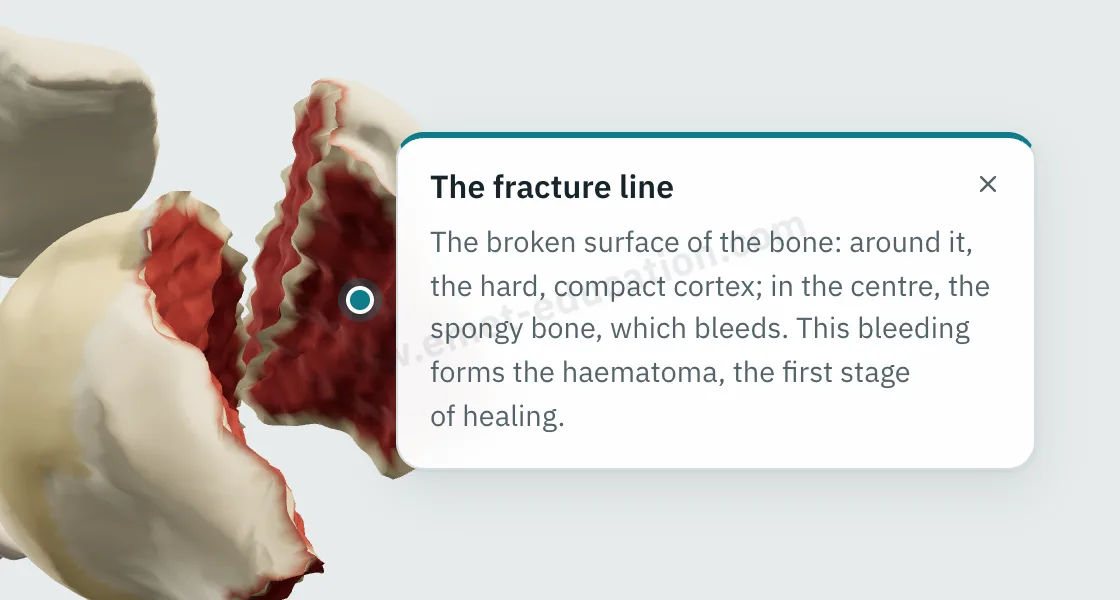
Tap a fragment, the fracture line, the callus, the nail, a screw or the plate: its name and an explanation appear.

  • One explanation per fragment — what it carries changes with the type — and for the fracture line, the callus and the hardware.
  • Written for the patient, in their language.
  • They can reread it on their own, on the tablet or at home.
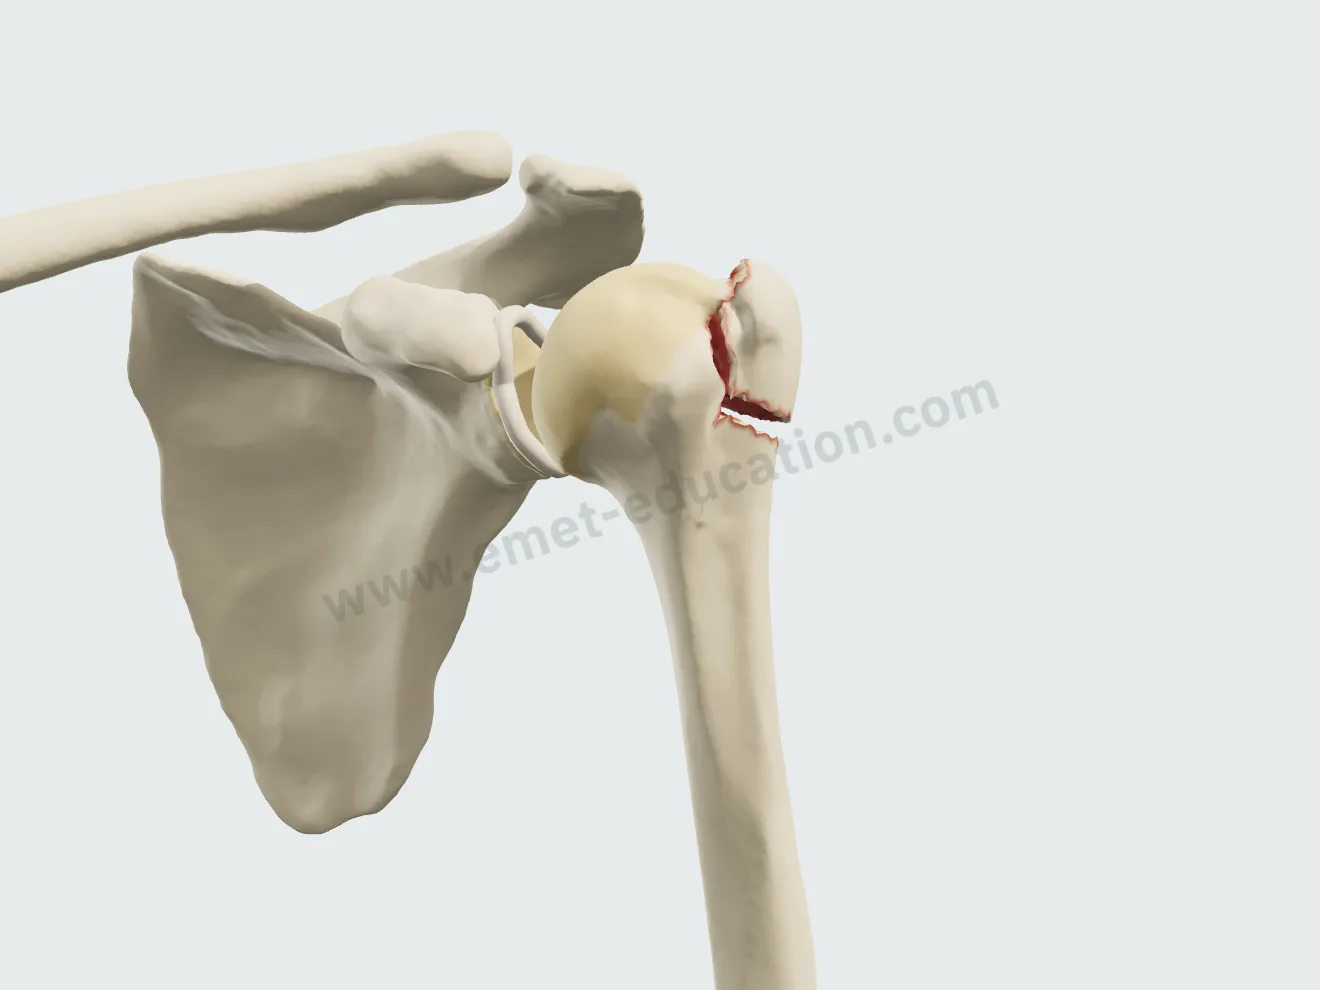
Explanation bubble “The fracture line” shown after tapping the cut surface of the greater tuberosity: the cortex, the bleeding cancellous bone, the hematoma.
“What is this?” on tap

They can replay the treatment step by step

From “The proposed treatment,” the patient replays the procedure: each step plays at their own pace, with its explanation, as often as they like.

Patient view on a phone: the locking plate fixation replayed step by step.
“Replay”: the procedure, step by step

Try it with your next case: the model opens in your browser, nothing to install.

Customize the fracture

Patient information

Quality information, documented

Only 12% of U.S. adults have proficient health literacy (National Assessment of Adult Literacy). A patient who sees their own lesions and the proposed procedure understands them, gives truly informed consent, and approaches treatment with confidence.

For the patient

They see their own lesions, reproduced from their imaging, and how the proposed treatment unfolds. They leave with the same material and can review it at home, with their family, as often as they like, before giving consent.

For the physician

Each visit created with an account keeps a record of the information provided: what was shown, when, and whether the patient reviewed it. The model image, with the anatomical findings, the proposed treatment and the QR code, downloads for the patient's chart and prints. Informed consent, as the Joint Commission puts it, is more than getting a signature.

  • Saved and datedThe exact state of the model: injuries shown, treatment proposed.
  • Identical, archivableThe patient receives what you showed; the image goes in the chart and prints.
  • TrackedEach time the patient opens the link is recorded.
  • AnonymousThe link given to the patient carries no identifying data.

“Document the informed consent conversation and the patient’s (or surrogate’s) decision in the medical record in some manner.”

AMA Code of Medical Ethics, Opinion 2.1.1, Informed Consent

The model supports the consent conversation and the written consent form; it does not replace them. Data and privacy: legal information (in French).

Questions

Questions from colleagues

Is the model free?

Yes: the fracture models are free. Treatments (fixation) and other features are paid options.

Do I need an account?

Not to open the model, set the fracture and walk through the treatment. After about fifteen adjustments, you will be asked to create a free account: it saves your visits, picks them up from one time to the next, and records when the patient opens the link.

What equipment do I need?

Just a web browser, nothing to install: computer, tablet or TV screen in the exam room; the patient opens it on their phone. One click saves an image, without the interface, for the chart.

What happens to patient data?

No patient names are stored. The link given to the patient carries only the state of the model: fracture, treatment, language and visit date. A name written on the image you hand out stays on that image.

Is it a medical device?

No: it is an educational tool. It does not diagnose, does not plan surgery, and does not replace the consent conversation or the written consent form. Among software functions that are not medical devices, the FDA lists those intended for general patient education and interactive anatomy diagrams used for training.

How long does it take in clinic?

Three adjustments and one procedure played: a few minutes, during the visit. The patient reviews it at home, as often as they like.

Which classifications?

Neer: four segments, a part counts beyond 1 cm of displacement or 45° of angulation; fracture-dislocations and head split included, and the Jakob valgus-impacted 4-part fracture. AO/OTA 2018 (bone 11): A1.1, A1.2, A2.1, B1.1, B1.2, C1.1, C1.3, C3.1. Neer is recalculated from the sliders.

Does the model choose the treatment?

No: you choose. The model only flags (⚠) an unusual indication — a nail for a head split, a reverse arthroplasty for a 2-part fracture — and never blocks a choice.

Can I embed it on my website?

It is planned for upcoming plans: the model displayed on a practice or hospital website, credited to EMET Education.

Which languages?

English, Spanish, French and Russian. The patient receives the model in the language chosen during the visit, which helps with the roughly 28 million people in the U.S. with limited English proficiency, alongside a qualified interpreter, not instead of one.

Design

Who designed this model

Model designed by Dr. Mikaël Chelli, orthopedic surgeon, based on the reference classifications. Updated October 25, 2026.

  • Neer C.S. II. Displaced proximal humeral fractures. I. Classification and evaluation. J Bone Joint Surg Am, 1970. PMID 5455339
  • AO/OTA 2018 classification of proximal humerus fractures (bone 11); AO Surgery Reference. PMID 29256945
  • Jakob R.P. et al. Four-part valgus impacted fractures of the proximal humerus. J Bone Joint Surg Br, 1991. PMID 2005159
  • Boileau P. et al. Displaced humeral surgical neck fractures: classification and results of third-generation percutaneous intramedullary nailing. J Shoulder Elbow Surg, 2019. PMID 30429058
  • Laux C.J. et al. Current concepts in locking plate fixation of proximal humerus fractures. J Orthop Surg Res, 2017. PMID 28946902
  • Boileau P. et al. Reverse shoulder arthroplasty for acute fractures in the elderly: is it worth reattaching the tuberosities? J Shoulder Elbow Surg, 2019. PMID 30573429

Try it with your next patient

The model opens in your browser, nothing to install, no sign-up.

Know a colleague who could use it? Email this page ·